Related Experiment Video
Updated: Dec 31, 2025
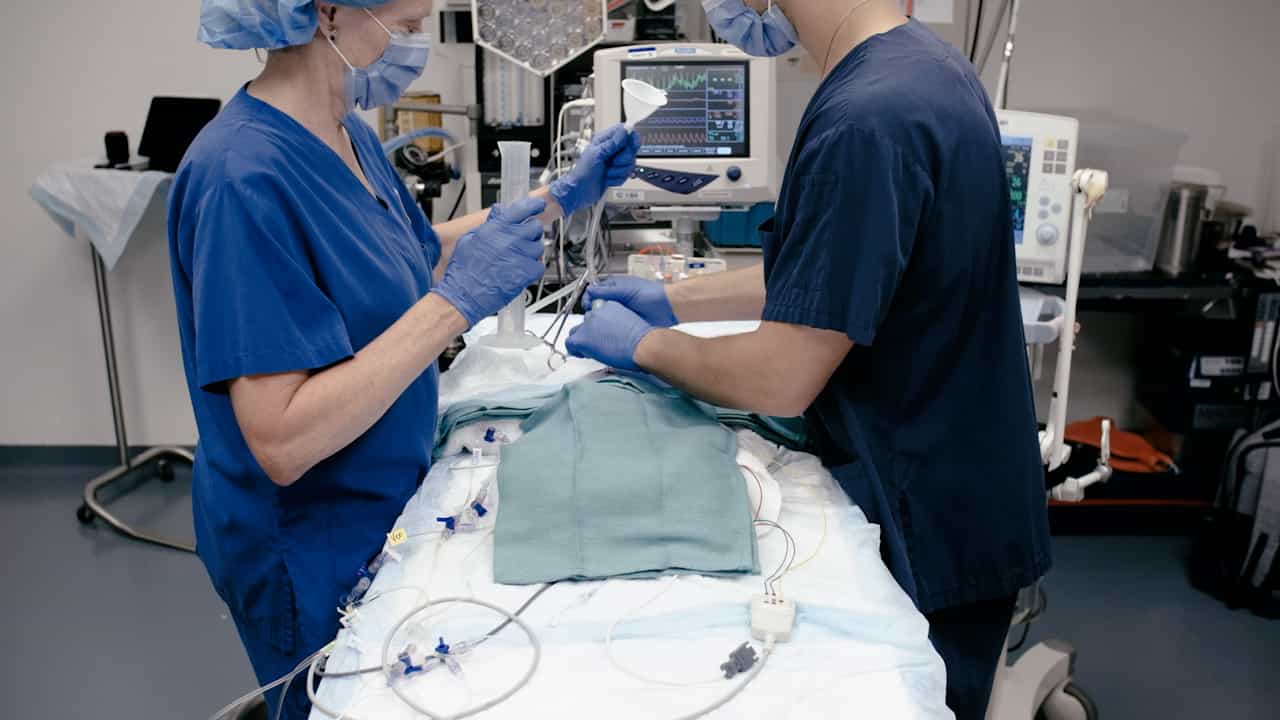
Development of a Neonatal Piglet Acute Lung Injury Model Recreating the Early Environment of Preterm Infant Lungs
Published on: October 31, 2025
Health Care Burden of Bronchopulmonary Dysplasia Among Extremely Preterm Infants
Meredith E Mowitz1, Rajeev Ayyagari2, Wei Gao2
1Division of Neonatology, College of Medicine, University of Florida, Gainesville, FL, United States.

Insights
Bronchopulmonary dysplasia (BPD) significantly increases healthcare costs and hospitalizations for extremely preterm infants. However, gestational age at birth is a more significant factor influencing these healthcare burdens than BPD itself.
Area of Science:
- Neonatal Medicine
- Pediatric Pulmonology
- Health Services Research
Background:
- Infants born extremely preterm face a high risk of developing bronchopulmonary dysplasia (BPD).
- BPD significantly contributes to the healthcare burden in this vulnerable population.
- Understanding the incremental costs associated with BPD is crucial for resource allocation.
Purpose of the Study:
- To assess the incremental healthcare burden of bronchopulmonary dysplasia (BPD) in extremely preterm infants.
- To evaluate the impact of BPD and associated comorbidities on healthcare utilization and costs.
- To compare the influence of BPD versus gestational age on healthcare outcomes.
Main Methods:
- Retrospective analysis of health service claims data (Premier Perspective database).
- Inclusion of infants born at ≤28 weeks gestation, requiring neonatal intensive care, and surviving to ≥36 weeks postmenstrual age.
- Determination of BPD status and gestational age using ICD-9-CM codes.
Main Results:
- 40.8% of 12,017 extremely preterm infants had BPD, with prevalence increasing as gestational age decreased.
- Infants with BPD experienced longer hospital stays (102 vs. 83 days) and higher total charges ($799,499 vs. $588,949) compared to those without.
- Gestational age at birth had a greater impact on total charges than the presence or absence of BPD.
- BPD was associated with higher late in-hospital mortality (1.9% vs. 0.6%) and increased healthcare encounters in the first year.
Conclusions:
- Bronchopulmonary dysplasia (BPD) is a major driver of the substantial healthcare burden in extremely preterm infants.
- Gestational age at birth is a more significant determinant of healthcare costs for extremely preterm infants than BPD.
- Further research into mitigating BPD and addressing the impact of prematurity is warranted.
Abstract:
Background: Infants born extremely preterm are at high risk of developing bronchopulmonary dysplasia (BPD). This study aimed to assess the incremental health care burden of BPD and associated comorbidities among extremely preterm infants in the United States. Methods: Health service claims in the Premier Perspective database were retrospectively analyzed for infants born at ≤28 weeks gestation who were admitted to neonatal intensive care during birth hospitalization and survived to a postmenstrual age of ≥36 weeks. Gestational age (GA) at birth and BPD status of infants was determined based on International Classification of Diseases, Ninth Revision, Clinical Modification (ICD-9-CM) codes recorded in the database. Results: Of the 12,017 infants included, 4,904 (40.8%) had BPD. BPD increased with decreasing GA: 67.4% of infants born at <24 weeks GA had BPD vs. 28.7% of those born at 27-28 weeks. Infants with BPD had significantly longer hospital stays following birth than those without (mean [standard deviation (SD)] 102 [34] vs. 83 [24] days, respectively, P < 0.001), and incurred higher total charges (mean [SD] $799,499 [$535,528] vs. $588,949 [$377,137], respectively, P < 0.001). Mean total charges incurred during index hospitalization decreased as GA at birth increased, with GA having a bigger effect than presence or absence of BPD. During their first year, infants with BPD had a higher in-hospital late mortality rate than those without (1.9 vs. 0.6%), and were more likely to have two or more hospital encounters following birth hospitalization (58.0 vs. 48.2%). Among infants who had two or more encounters after discharge, those with BPD experienced a higher percentage of pulmonary symptoms than those without (46.3 vs. 38.9%). Comparison with infants who did not have BPD, retinopathy of prematurity, or intraventricular hemorrhage showed that BPD is the main complication contributing to increased length of stay, costs, in-hospital mortality, and additional health care encounters. Conclusion: BPD is a key contributor to the large health care burden associated with extremely preterm birth. However, GA at birth has a bigger effect on health care costs for extremely preterm infants than the presence of BPD.
More Related Videos


Related Concept Videos
 01:22
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:17
Pulmonary Cycle: Exhalation
 01:30
Chronic Obstructive Pulmonary Disease-V: Nursing Management
Assessment
 01:05
Breathing
 01:26
COPD: Management Using Bronchodilators and Corticosteroids
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction