Related Experiment Video
Updated: Jul 21, 2026
Quantitative Magnetic Resonance Imaging of Skeletal Muscle Disease
Published on: December 18, 2016
Considerations for Mean Upper Cervical Cord Area Implementation in a Longitudinal MRI Setting: Methods, Interrater
C Chien1,2, V Juenger1,2,3, M Scheel3
1From the Experimental and Clinical Research Center (C.C., V.J., A.U.B., F.P.), Max Delbrück Center for Molecular Medicine & Charité-Universitätsmedizin Berlin, corporate member of Freie Universität Berlin, Humboldt-Universität zu Berlin, and Berlin Institute of Health, Berlin, Germany.

Background And Purpose:
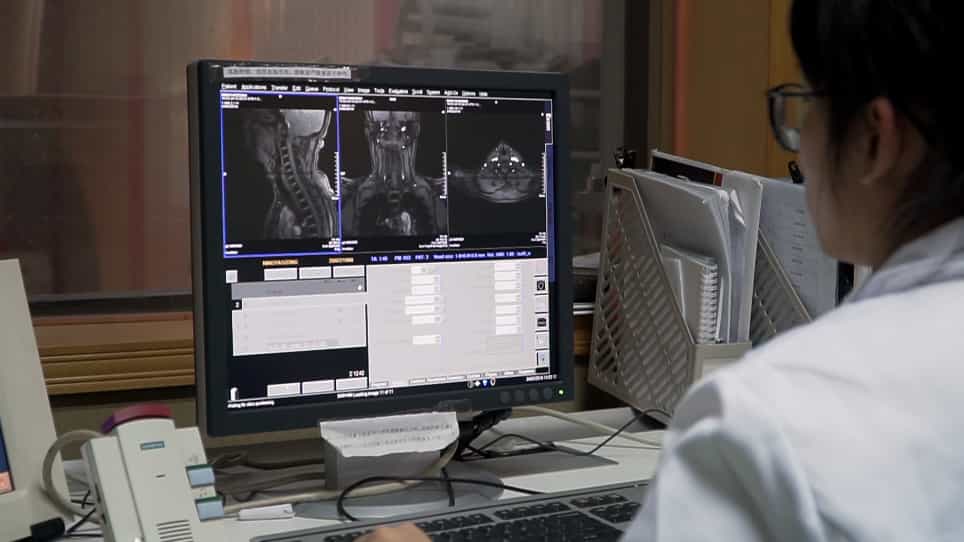
Spinal cord atrophy is commonly measured from cerebral MRIs, including the upper cervical cord. However, rescan intraparticipant measures have not been investigated in healthy cohorts. This study investigated technical and rescan variability in the mean upper cervical cord area calculated from T1-weighted cerebral MRIs.
Materials And Methods:
In this retrospective study, 8 healthy participants were scanned and rescanned with non-distortion- and distortion-corrected MPRAGE sequences (11-50 sessions in 6-8 months), and 50 participants were scanned once with distortion-corrected MPRAGE sequences in the Day2day daily variability study. From another real-world observational cohort, we collected non-distortion-corrected MPRAGE scans from 27 healthy participants (annually for 2-4 years) and cross-sectionally from 77 participants. Statistical analyses included coefficient of variation, smallest real difference, intraclass correlation coefficient, Bland-Altman limits of agreement, and paired t tests.
Results:
Distortion- versus non-distortion-corrected MPRAGE-derived mean upper cervical cord areas were similar; however, a paired t test showed incomparability (t = 11.0, P = <.001). Higher variability was found in the mean upper cervical cord areas calculated from an automatic segmentation method. Interrater analysis yielded incomparable measures in the same participant scans (t = 4.5, P = <.001). Non-distortion-corrected mean upper cervical cord area measures were shown to be robust in real-world data (t = -1.04, P = .31). The main sources of variability were found to be artifacts from movement, head/neck positioning, and/or metal implants.
Conclusions:
Technical variability in cord measures decreased using non-distortion-corrected MRIs, a semiautomatic segmentation approach, and 1 rater. Rescan variability was within ±4.4% for group mean upper cervical cord area when MR imaging quality criteria were met.