Related Experiment Video
Updated: Dec 29, 2025
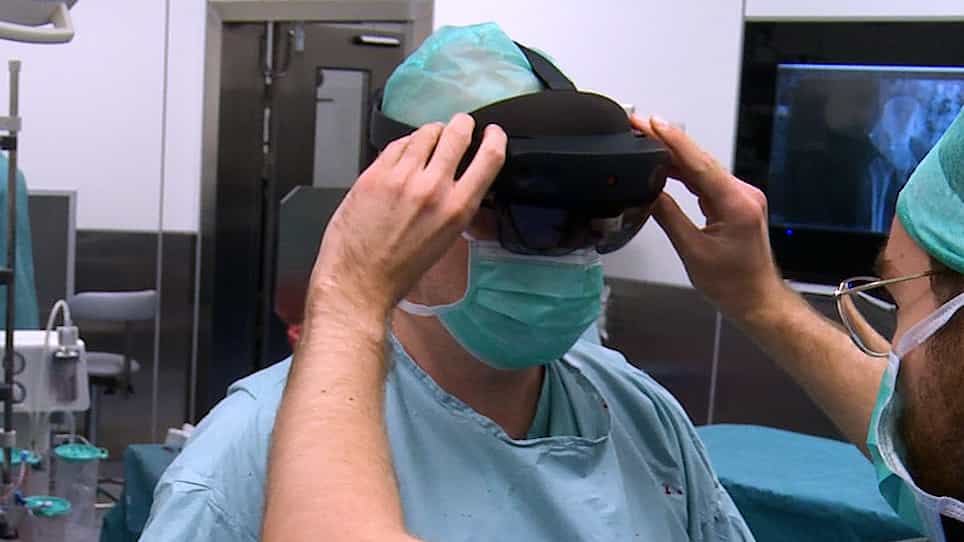

The Use of Mixed Reality in Custom-Made Revision Hip Arthroplasty: A First Case Report
Published on: August 4, 2022
[Complication profile and revision concepts for megaprosthetic reconstruction following tumour resection at the hip]
H Fritzsche1, J Goronzy2, K-D Schaser2
1UniversitätsCentrum für Orthopädie & Unfallchirurgie, Universitätsklinikum Carl Gustav Carus an der Technischen Universität Dresden, Fetscherstraße 74, 01307, Dresden, Deutschland. hagen.fritzsche@uniklinikum-dresden.de.

Background:
Tumourous destruction of the periacetabular region and the proximal femur is a typical consequence of either primary malignant bone tumour manifestation or skeletal metastatic diseases. Pathological fractures of the proximal femur and periacetabular regions due to primary manifestation or metastatic disorders are frequent.
Objectives:
Presentation of the most common complications of tumour endoprostheses at the hip and a description of management strategies, including therapeutic recommendations and concepts for complication avoidance.
Materials And Methods:
The current knowledge and our own experience of complication management with the use of megaprostheses around the hip are presented.
Results:
Compared to elective/primary total hip arthroplasty, megaprosthetic reconstructions following tumour resections have an increased rate of postoperative deep infections, dislocations, incidence of pathological and periprosthetic fractures and of deep vein thrombosis. The postoperative mortality and local tumour recurrence along with deep infections represent the most serious complications.
Conclusions:
In comparison to primary arthroplasty, the risk of failure and complications following tumour-endoprosthetic replacement is increased. Precise surgical planning and careful selection and preoperative preparation of suitable patients should be performed in close interdisciplinary cooperation with final decision-making on an interdisciplinary tumour board. Wide resection and advanced reconstruction, as well as complicated palliative stabilization due to malignant bone tumour growth around the hip joint should be performed in musculoskeletal tumour centres with profound expertise in osteosynthetic and endoprosthetic reconstruction and consecutive complication management of the pelvis and the proximal femur.
More Related Videos
 09:51
The Transition to an Anterior-Based Muscle Sparing Approach Improves Early Postoperative Function but is Associated with a Learning Curve
Published on: September 7, 2022
 09:31
Individualized Stem-positioning in Calcar-guided Short-stem Total Hip Arthroplasty
Published on: February 27, 2018