Related Experiment Video
Updated: Dec 29, 2025
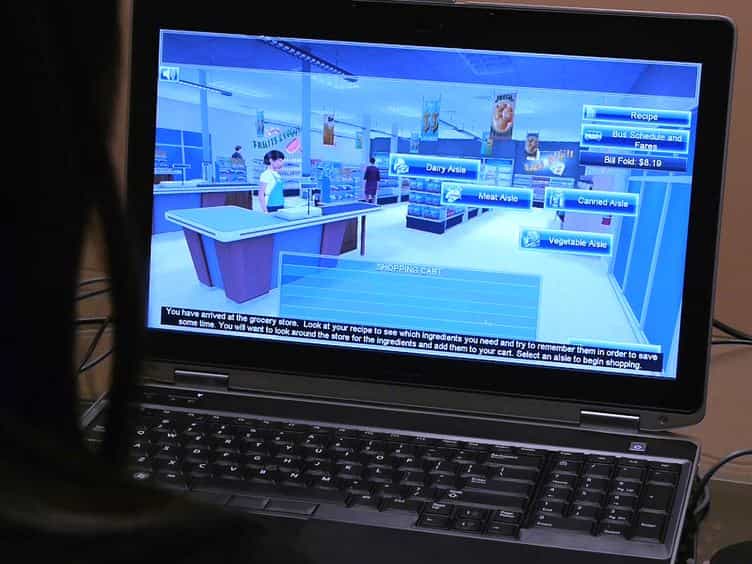

Development of a Virtual Reality Assessment of Everyday Living Skills
Published on: April 23, 2014
Development and validation of the Cambridge Multimorbidity Score
Rupert A Payne1, Silvia C Mendonca2, Marc N Elliott2
1Centre for Academic Primary Care (Payne), Population Health Sciences, University of Bristol, Bristol, UK; Primary Care Unit (Mendonca, Saunders, Edwards, Roland), Department of Public Health and Primary Care, Institute of Public Health, University of Cambridge, Cambridge, UK; RAND Corporation (Elliott), Santa Monica, Calif.; Research Department of Primary Care and Population Health (Marshall), University College London Medical School, Royal Free Campus, London, UK r.payne@bristol.ac.uk.

Background:
Health services have failed to respond to the pressures of multimorbidity. Improved measures of multimorbidity are needed for conducting research, planning services and allocating resources.
Methods:
We modelled the association between 37 morbidities and 3 key outcomes (primary care consultations, unplanned hospital admission, death) at 1 and 5 years. We extracted development (n = 300 000) and validation (n = 150 000) samples from the UK Clinical Practice Research Datalink. We constructed a general-outcome multimorbidity score by averaging the standardized weights of the separate outcome scores. We compared performance with the Charlson Comorbidity Index.
Results:
Models that included all 37 conditions were acceptable predictors of general practitioner consultations (C-index 0.732, 95% confidence interval [CI] 0.731-0.734), unplanned hospital admission (C-index 0.742, 95% CI 0.737-0.747) and death at 1 year (C-index 0.912, 95% CI 0.905-0.918). Models reduced to the 20 conditions with the greatest combined prevalence/weight showed similar predictive ability (C-indices 0.727, 95% CI 0.725-0.728; 0.738, 95% CI 0.732-0.743; and 0.910, 95% CI 0.904-0.917, respectively). They also predicted 5-year outcomes similarly for consultations and death (C-indices 0.735, 95% CI 0.734-0.736, and 0.889, 95% CI 0.885-0.892, respectively) but performed less well for admissions (C-index 0.708, 95% CI 0.705-0.712). The performance of the general-outcome score was similar to that of the outcome-specific models. These models performed significantly better than those based on the Charlson Comorbidity Index for consultations (C-index 0.691, 95% CI 0.690-0.693) and admissions (C-index 0.703, 95% CI 0.697-0.709) and similarly for mortality (C-index 0.907, 95% CI 0.900-0.914).
Interpretation:
The Cambridge Multimorbidity Score is robust and can be either tailored or not tailored to specific health outcomes. It will be valuable to those planning clinical services, policymakers allocating resources and researchers seeking to account for the effect of multimorbidity.
More Related Videos


Related Concept Videos
 01:27
Diagnostic and Statistical Manual of Mental Disorders (DSM)
 01:03
Data Validation
Nursing assessment guides are generally based on holistic models rather than medical...
 01:17
Classification of Illness
An illness is a response to a disease in which the person's level of functioning is changed compared with a previous level. The general classification of illness includes acute and chronic.
Acute illness is severe...
 01:18
Factors Affecting Illness
For instance, risk factors are connected to illness,...
 01:21
Dimensions of Health and Illness