Related Experiment Video
Updated: Dec 29, 2025
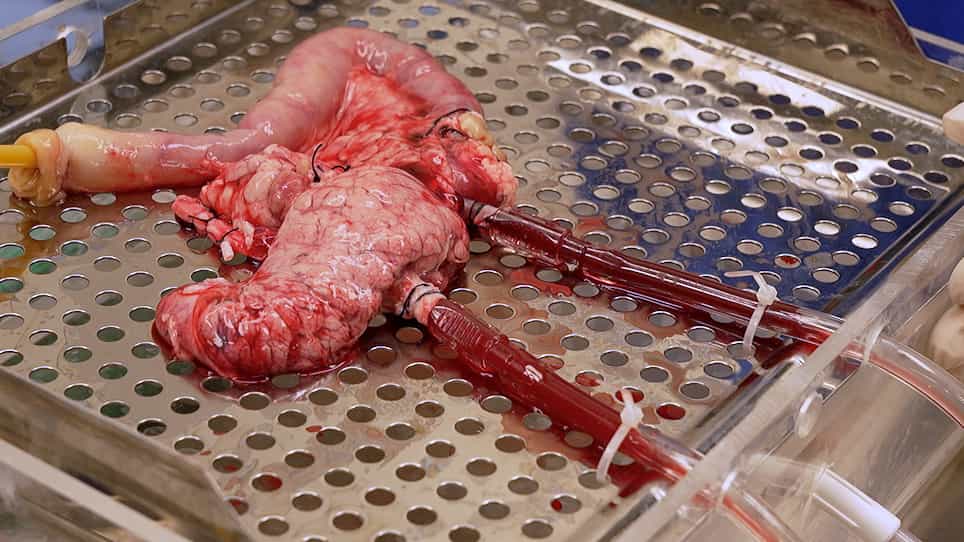
Normothermic Ex Vivo Pancreas Perfusion for the Preservation of Pancreas Allografts before Transplantation
Published on: July 27, 2022
Outcomes of simultaneous pancreas and kidney transplantation based on donor resuscitation
Franka Messner1,2, Joanna W Etra2, Yifan Yu2
1Department of Visceral, Transplant and Thoracic Surgery, Center of Operative Medicine, Medical University of Innsbruck, Innsbruck, Austria.

Abstract:
It has been hypothesized that transplanting simultaneous pancreas kidney (SPK) grafts from donors with a history of cardiac arrest and cardiopulmonary resuscitation (CACPR) leads to inferior posttransplant outcomes due to organ hypoperfusion during cardiac arrest and mechanical trauma during resuscitation. Using Scientific Registry of Transplant Recipients data, we identified 13 095 SPK transplants from 2000-2018, of which 810 (6.2%) were from donors with a history of CACPR. After inverse probability of treatment weighting on donor and recipient characteristics, we found that 1-, 5-, and 10-year patient (CACPR: 96.4%, 89.9%, and 78.9%; non-CACPR: 96.3%, 88.9%, and 76.0%; P = .3), death-censored pancreas graft survival (CACPR: 89.3%, 82.7%, 75.0%; non-CACPR: 89.9%, 82.7%, 76.3%; P = .7), and death-censored kidney graft survival (CACPR: 97.0%, 89.5%, 78.2%; non-CACPR: 96.9.9%, 88.7%, 80.0%; P = .4) were comparable between the two groups. There were no differences in the risk of pancreatitis (CACPR: 2.9%, non-CACPR: 2.4%; weighted OR = 0.74 1.22 2.02 ; P = .4), anastomotic leak (CACPR: 1.6%, non-CACPR: 2.0%; weighted OR = 0.54 1.02 1.93 ; P > .9), or median length of hospital stay (CACPR: 8 days, non-CACPR: 9 days; P = .6) for recipients of CACPR vs non-CACPR donors. Our findings suggest that CACPR donors could be used to expand the SPK donor pool without compromising short- or long-term outcomes.

Related Concept Videos
 01:26
Kidney Transplant II: Surgical Procedure
 01:28
Kidney Transplant I: Introduction
 01:16
Kidney Transplant III: Nursing Management