Related Experiment Video
Updated: Dec 28, 2025

Precision Measurements and Parametric Models of Vertebral Endplates
Published on: September 17, 2019
Selecting the Last Substantially Touching Vertebra as Lowest Instrumented Vertebra in Lenke type 2A-R and 2A-L Curves
Xiaodong Qin1, Zhong He, Rui Yin
1Department of Spine Surgery, the Affiliated Drum Tower Hospital of Nanjing University Medical School, Nanjing, China.

Study Design:
A retrospective study.
Objective:
The aim of this study was to determine whether the last substantially touching vertebra (LSTV) can be selected as the optimal lowest instrumented vertebra (LIV) for Lenke 2A adolescent idiopathic scoliosis (AIS) with different lumbar modifiers (2A-R and 2A-L) and to investigate its relationship with the distal adding-on.
Summary Of Background Data:
Previous studies have documented good outcomes in Lenke 1A curve when LSTV was selected as LIV.
Methods:
A total of 101 female patients were included with a minimum of 2-year follow-up after selective posterior surgery. Patients were classified on the basis of the direction of L4 tilt: 2A-L and 2A-R. Patients with LSTV-1, LSTV, or LSTV+1 selected as LIV were assigned to three groups. Factors associated with adding-on were analyzed through comparison among the three groups.
Results:
The level of LSTV was more distal in the 2A-R group than that in the 2A-L group (P = 0.011). Distal adding-on was observed in 24 patients (23.8%). In the 2A-R curves, 26.1% patients were found to have adding-on. The incidence of adding-on was significantly higher in LSTV-1 than LSTV or LSTV+1 group. Logistic regression analysis showed the distance between LIV and LSTV (LIV-LSTV <0) was the independent factor associated with adding-on (odds ratio [OR] = 8.7, 95% confidence interval [CI] = 3.1-45.5, P = 0.011). In the 2A-L curves, 21.8% patients were found to have adding-on. The incidence of adding-on was significantly lower in LSTV+1 than LSTV-1 or LSTV group. Similarly, logistic regression showed the distance between LIV and LSTV (LIV-LSTV ≤0) had significant association with adding-on (OR = 11.9, 95% CI = 2.5-53.2, P = 0.009).
Conclusion:
The distance between LIV and LSTV was a significant factor associated with adding-on for both 2A-R and 2A-L patients. The rule of selecting LIV should be different between 2A-R and 2A-L curves. We recommend to extend the fusion level to LSTV in 2A-R curve and to LSTV+1 in 2A-L curve to avoid distal adding-on.
Level Of Evidence:
3.


Related Concept Videos
 01:16
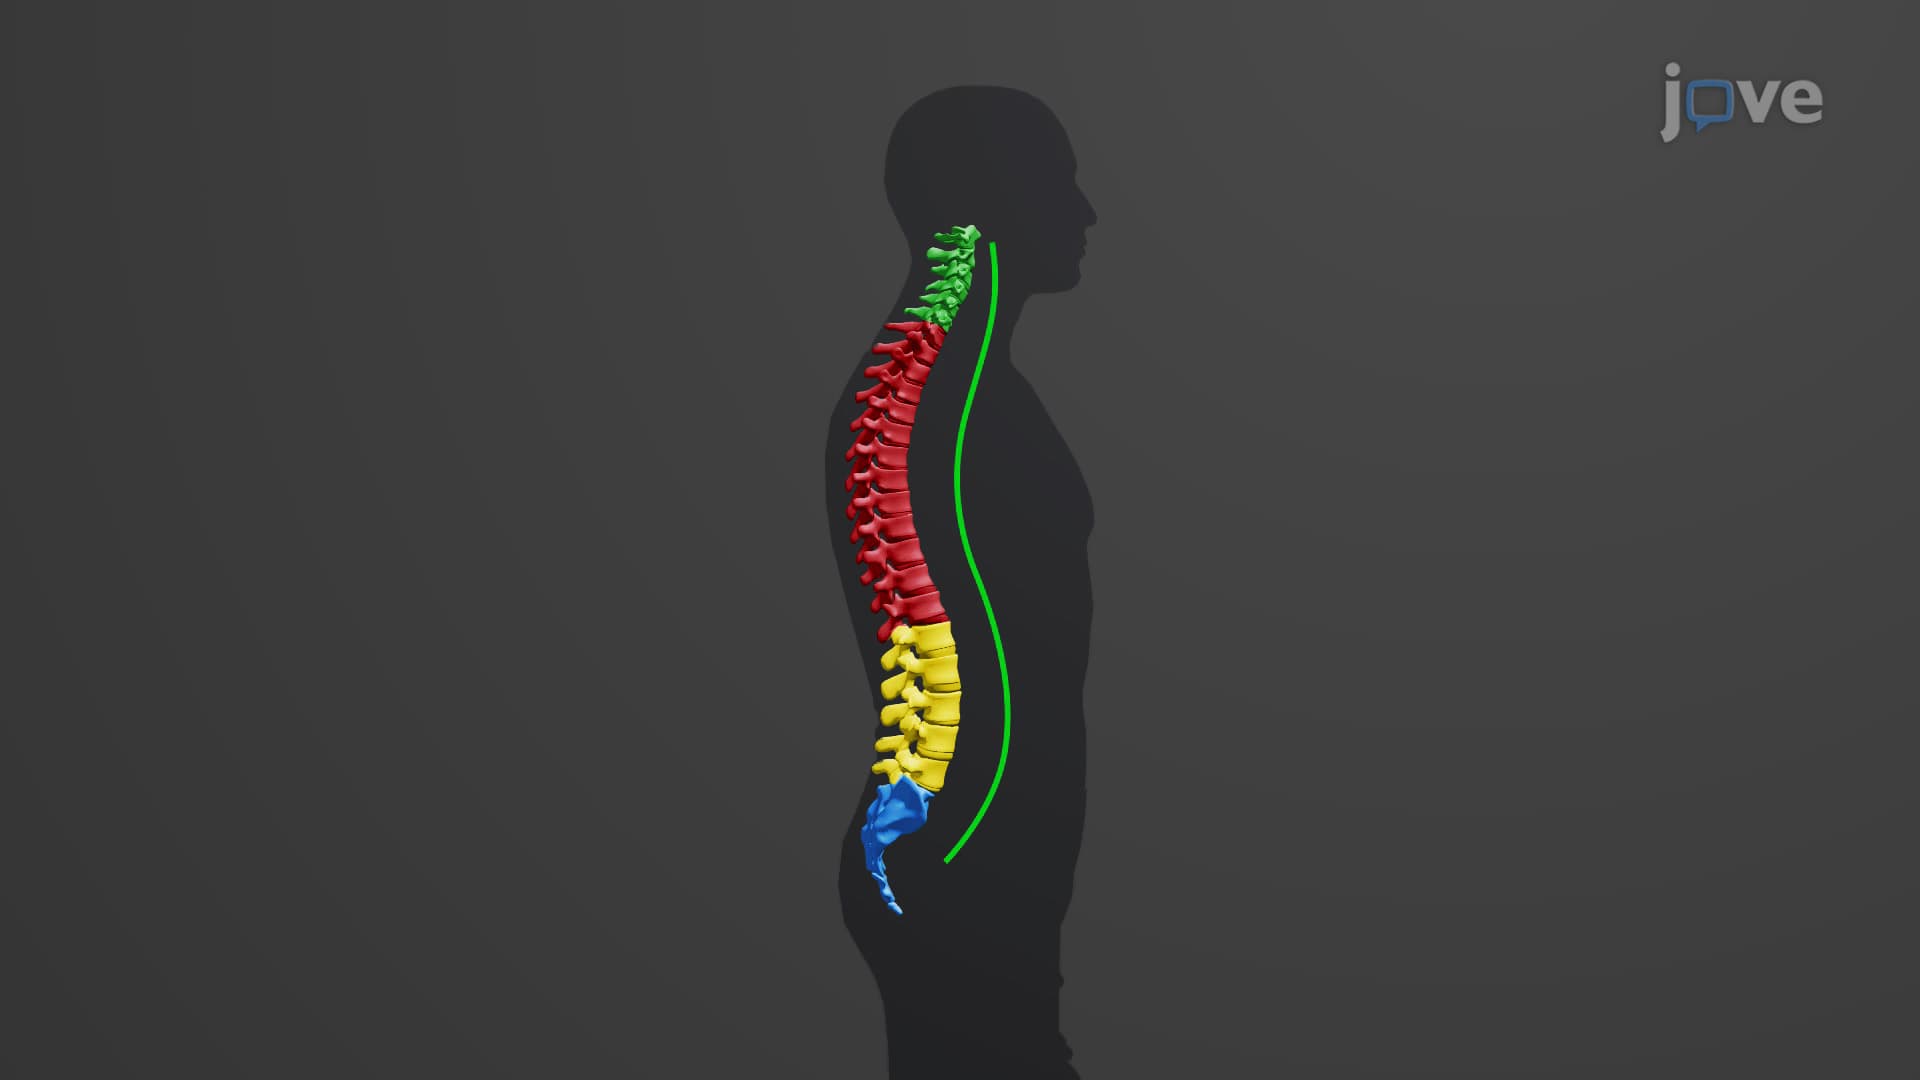
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form...
 01:30
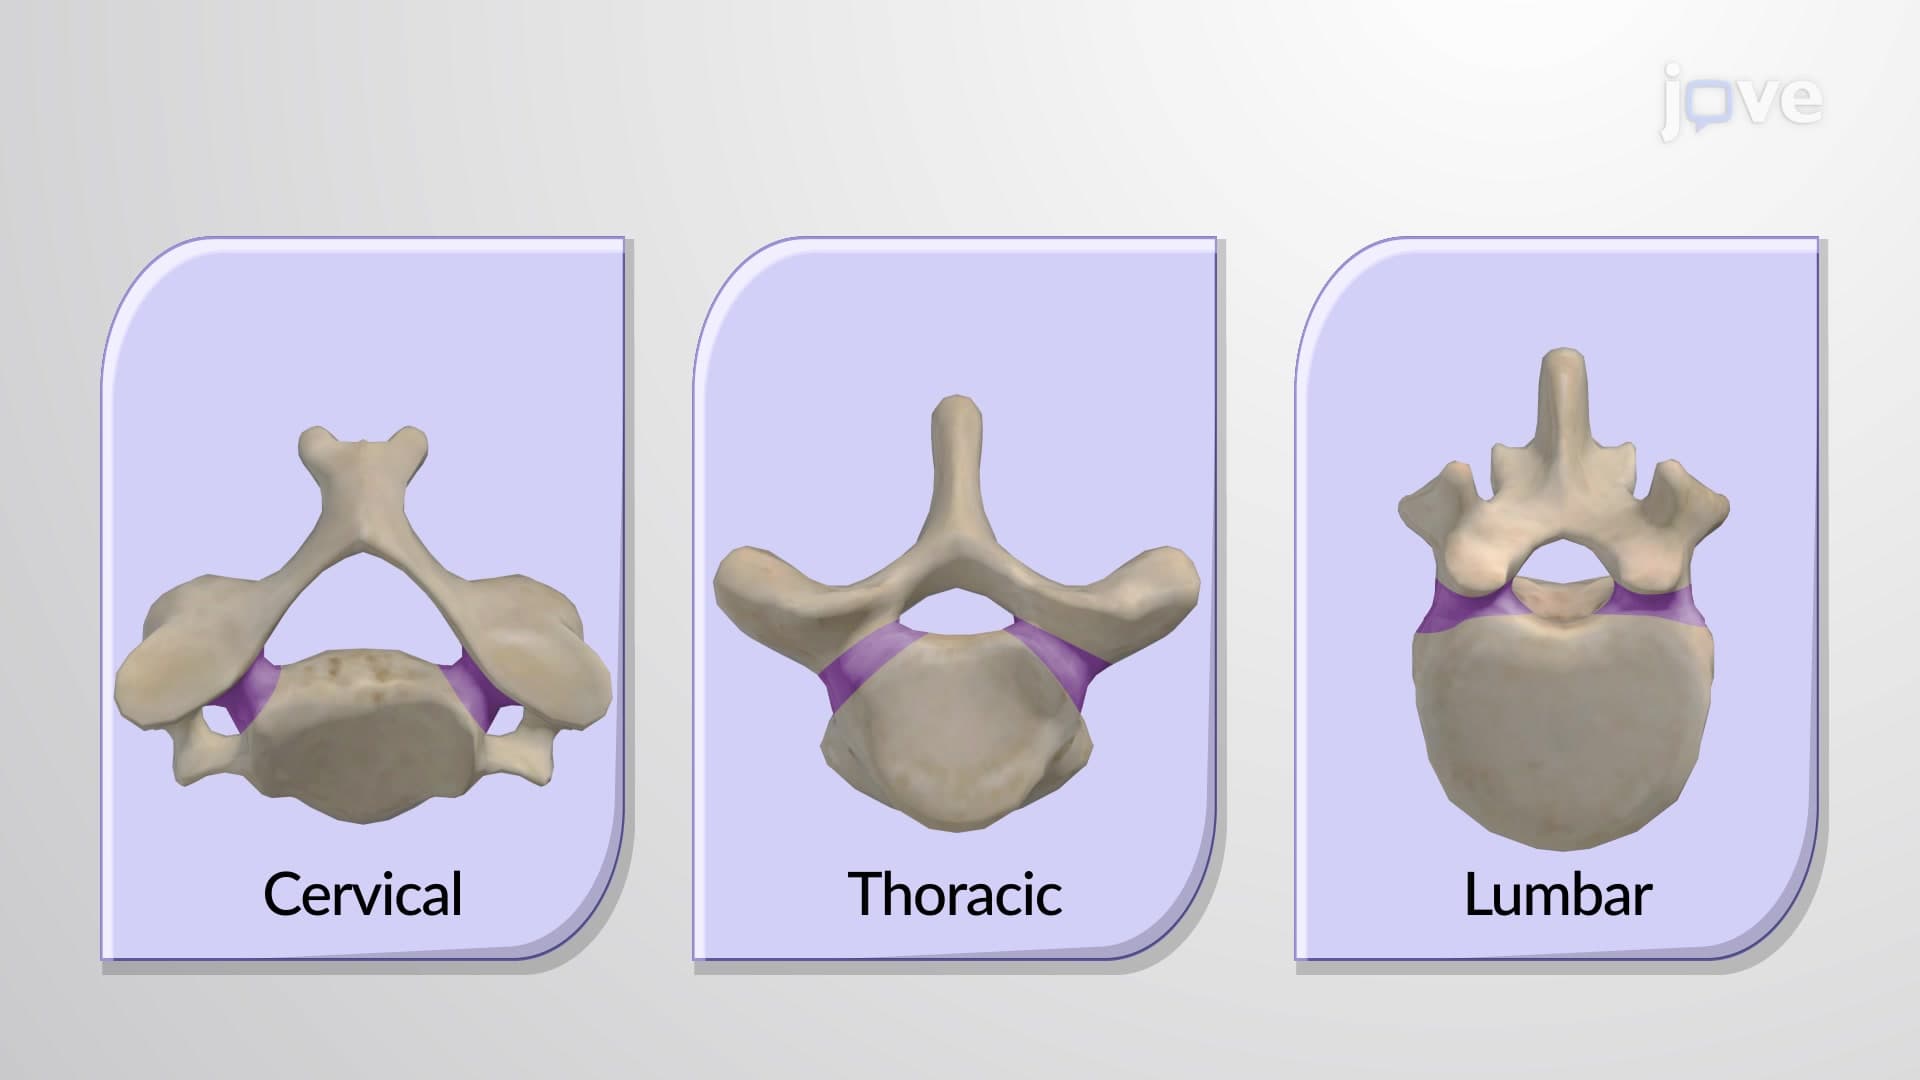
General Structure of a Vertebra