

Physical Activity, Hormone Therapy Use, and Stroke Risk among Women in the California Teachers Study Cohort
Charlie Zhong1, Jenna Voutsinas2, Joshua Z Willey3,4
1Division of Health Analytics, Department of Computational and Quantitative Medicine, Beckman Research Institute and the City of Hope, Duarte, California, USA, czhong@coh.org.

Background:
Postmenopausal hormone therapy (HT) increases the risk of stroke. Here we evaluate whether leisure time physical activity (LTPA) can change stroke risk in women using HT, leveraging data from the California Teachers Study.
Methods:
Female California educators without a prior history of stroke (n = 118,294) were followed from 1995 through 2015 for stroke end points. Based on statewide hospitalization data, 4,437 women had ischemic (n = 3,162; International Classification of Diseases [ICD]-9 433, 434, 436) or hemorrhagic (n = 1,275; ICD-9 430-432, excluding 432.1) stroke. LTPA and HT use were evaluated at 2 time points (baseline [1995-1996] and 10-year follow-up [2005-2006]). LTPA was assessed using American Heart Association (AHA) recommendations (>150 min/week moderate or >75 min/week strenuous physical activity). Using multivariable Cox proportional hazards models, we estimated the hazard ratios (HRs) and 95% CIs for the associations between HT use and concurrent LTPA with incident stroke.
Results:
Compared to women who never used HT, stroke risk was highest among women who were current HT users and did not meet AHA recommendations for LTPA at the time of their HT use: HRbaseline 1.28 (95% CI 1.13-1.44); HR10-year follow-up 1.17 (95% CI 0.91-1.50). Based on the baseline questionnaire, current HT users who met AHA recommendations for LTPA in 1995-1996 still had elevated stroke risk in the 20-year follow-up (HR 1.22, 95% CI 1.08-1.37). However, among current HT users who met AHA recommendations for LTPA at the 2005-2006 follow-up questionnaire, stroke risk was not elevated (HR 1.01, 95% CI 0.80-1.29). Evaluation of the 2 time points in concert further demonstrated that meeting AHA recommendations for LTPA at the most recent follow-up time point was required to reduce HT-related stroke risk.
Conclusion:
Concurrent physical activity may attenuate the short-term increase in risk of stroke risk associated with HT use.
More Related Videos
 06:18
An In Vivo Estrogen Deficiency Mouse Model for Screening Exogenous Estrogen Treatments of Cardiovascular Dysfunction After Menopause
Published on: August 13, 2019
 05:59
Visualization of Intensity Levels to Reduce the Gap Between Self-Reported and Directly Measured Physical Activity
Published on: March 7, 2019
Related Concept Videos
 01:26
Atherosclerosis III: Management
 01:17
Exercise and Cardiac Output
Sustained exercise increases the muscles' oxygen demand, which can be...
 01:20
Exercise and Cardiovascular Response
Light to moderate physical activity initiates a series of interconnected responses in the body. The heart rate modestly increases in anticipation of the workout, followed by widespread vasodilation as oxygen consumption by skeletal muscles increases. This results in decreased peripheral resistance, increased capillary blood flow, and accelerated...
 01:26
Coronary Artery Disease IV: Preventive Measures
 01:26
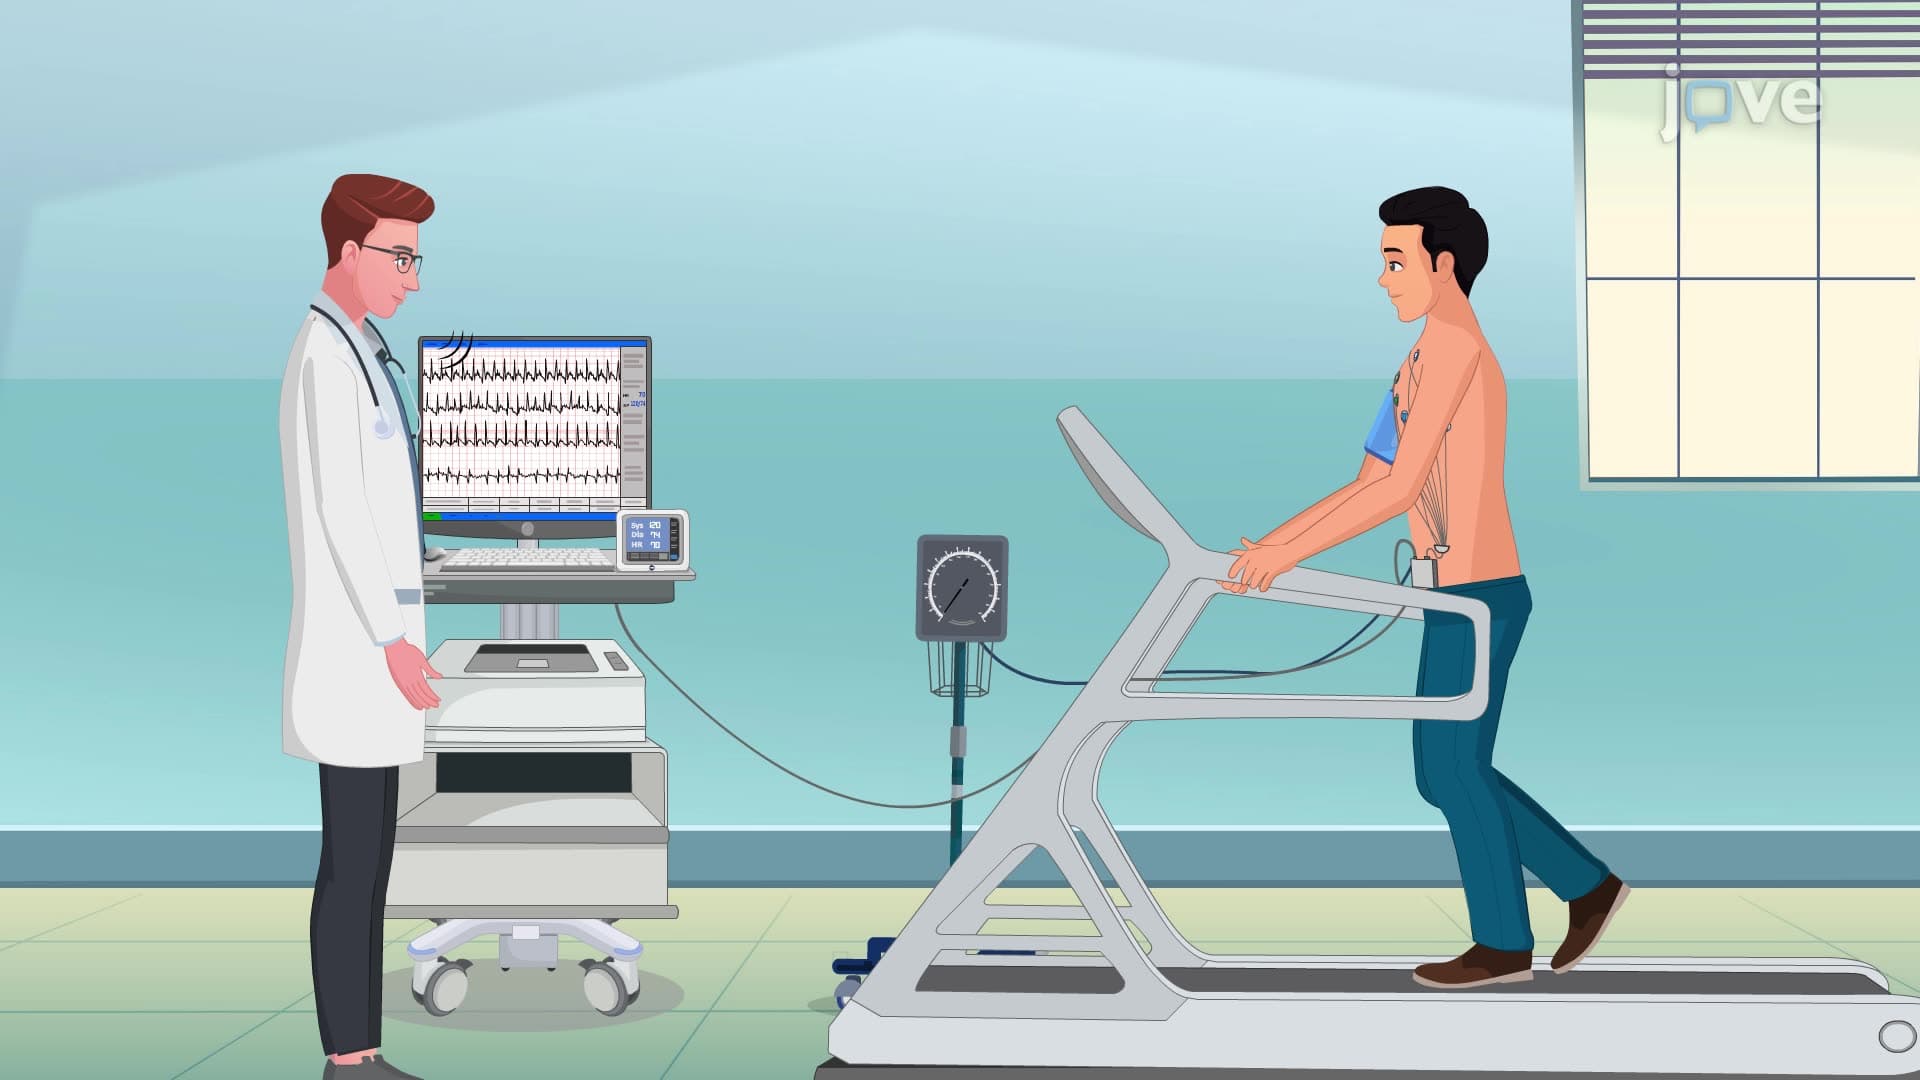
Exercise Stress Test
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes
 01:27
Peripheral Artery Disease III: Interprofessional Care