Related Experiment Video
Updated: Dec 28, 2025

The Transition to an Anterior-Based Muscle Sparing Approach Improves Early Postoperative Function but is Associated with a Learning Curve
Published on: September 7, 2022
Gender-Specific Sexual Activity After Hip Arthroscopy for Femoroacetabular Impingement Syndrome: Position Matters
Hannah Morehouse1, Kyle R Sochacki1, Shane J Nho2
1Houston Methodist Orthopedics and Sports Medicine, Houston, TX, USA.

Background:
There is limited evidence on the safety of return to sexual activity after hip arthroscopy.
Aim:
To determine the positional safety of sexual activity after hip arthroscopy relative to hip instability and/or impingement risk.
Study Design:
This study is an observational study.
Methods:
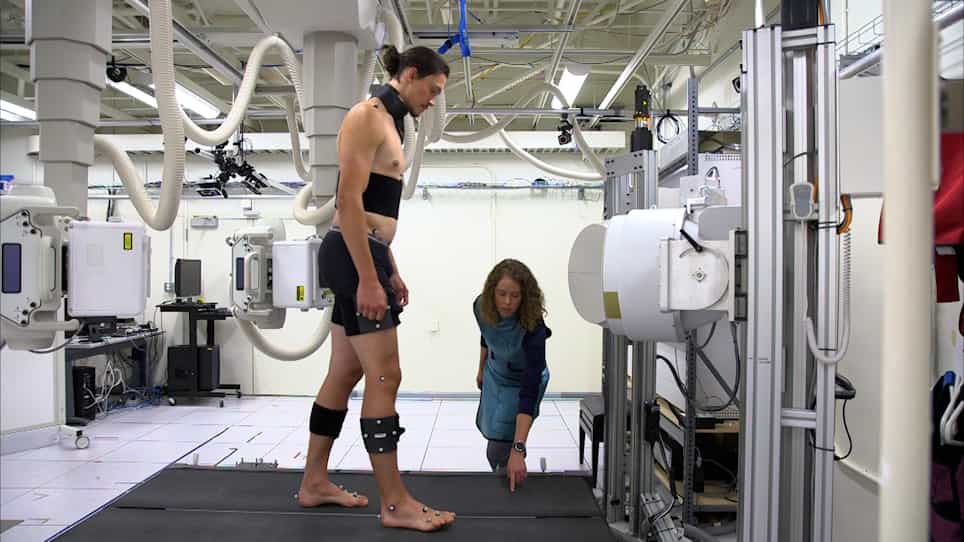
12 common sexual positions were identified based on previous research. Gender-specific hip motion was then assessed for the possibility of postarthroscopic hip instability (due to disruption of iliofemoral ligament [interportal capsulotomy] repair) and/or impingement (labral or capsular compressive stress with disrupted repair) for all 12 positions (both right and left hips; 15 unique male and 14 unique female positions). Instability risk was defined as greater than 0° hip extension, greater than 30° external rotation (ER), or greater than 30° abduction. Impingement risk was defined as greater than 90° hip flexion, greater than 10° internal rotation, and greater than 10° adduction.
Outcomes:
A majority of both male and female sexual positions caused either instability or impingement, with only 4 positions in women and 4 positions in men deemed "safe" by avoiding excessive hip motion.
Results:
Return to sexual activity after hip arthroscopy may cause instability in 10/15 of male positions and 5/14 female positions. Most male positions (6/10) were at risk for instability because of excessive ER. 2 positions were unstable because of a combination of ER and extension, one was due to extension, and one abduction. In female instability positions, all 5 were unstable because of excessive abduction. Impingement may be observed in 5 of 15 male positions and 6 of 14 female positions. In male impingement positions, all were due to excessive adduction. 4 female positions risked impingement due to excessive flexion and 2 positions due to internal rotation.
Clinical Implications:
This study demonstrates risks that should be considered when counseling patients preoperatively and postoperatively regarding sexual activity.
Strengths & Limitations:
This study closely models a hip preservation patient population by using 2 young and otherwise healthy individuals. The most significant limitation of this investigation was its basis with only 2 young healthy volunteers (one male, one female) in a single motion capture session using surface-based spherical retroreflective markers from a previous investigation.
Conclusion:
After hip arthroscopy, patients need to be made aware of the possibility of hip instability (10 of 15 men; 5 of 14 women) and impingement (5 of 15 men; 6 of 14 women) due to excessive hip motion that may compromise their outcome. Morehouse H, Sochacki KR, Nho SJ, et al. Gender-Specific Sexual Activity After Hip Arthroscopy for Femoroacetabular Impingement Syndrome: Position Matters. J Sex Med 2020;17:658-664.