Related Experiment Video
Updated: Dec 28, 2025
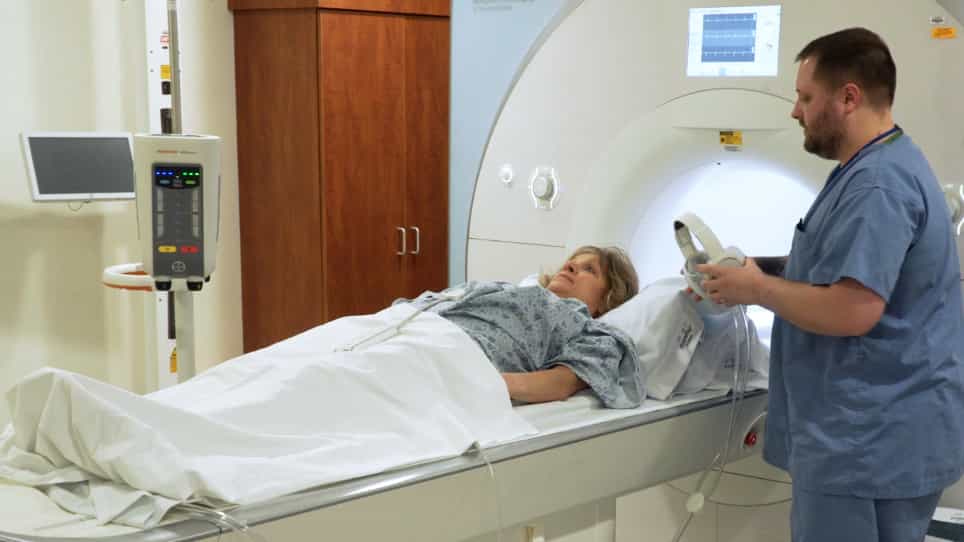

Cardiac Magnetic Resonance for the Evaluation of Suspected Cardiac Thrombus: Conventional and Emerging Techniques
Published on: June 11, 2019
Acute myocardial infarction, intraventricular thrombus and risk of systemic embolism
Stepan Hudec1, Martin Hutyra1, Jan Precek1
1Department of Internal Medicine I - Cardiology, University Hospital Olomouc and Faculty of Medicine and Dentistry, Palacky University, Olomouc, Czech Republic.

Insights
Left ventricular thrombus (LVT) after acute myocardial infarction (AMI) poses a risk of systemic embolism. Warfarin anticoagulation for 6 months is recommended for diagnosed LVT, but prophylactic warfarin in high-risk AMI patients is not advised.
Area of Science:
- Cardiology
- Cardiovascular Medicine
- Thrombosis Research
Background:
- Left ventricular thrombus (LVT) is a serious complication of acute myocardial infarction (AMI).
- Systemic embolism (SE) from LVT increases patient mortality and morbidity.
- Identifying the source of cardiac emboli is crucial for secondary prevention.
Purpose of the Study:
- To review the diagnosis and management of left ventricular thrombus (LVT) following acute myocardial infarction (AMI).
- To assess the efficacy and risks of anticoagulant therapies for LVT.
- To provide guidance on secondary prevention strategies for patients with LVT.
Main Methods:
- Echocardiography, particularly with contrast enhancement, is vital for LVT diagnosis.
- Cardiac magnetic resonance imaging serves as the gold standard but is not for initial screening.
- Review of current evidence on anticoagulant therapies, including warfarin and direct oral anticoagulants (DOACs).
Main Results:
- Diagnosed LVT requires at least 6 months of warfarin anticoagulation with echocardiographic follow-up.
- Prophylactic warfarin in high-risk anterior AMI patients does not improve outcomes and increases bleeding risk.
- Insufficient evidence currently supports the use of DOACs for LVT in this context.
Conclusions:
- Early diagnosis and appropriate anticoagulation are key in managing LVT post-AMI.
- Warfarin remains a standard treatment for diagnosed LVT, while prophylactic use is not recommended.
- Further research is needed to establish the role of newer anticoagulants like DOACs.
Abstract:
The development of left ventricular thrombus (LVT) is a well-known and serious complication of acute myocardial infarction (AMI) due to the risk of systemic arterial embolism (SE), which is variable in its clinical picture and has potentially serious consequences depending on the extent of target organ damage. SE results in an increase in mortality and morbidity in these patients. LVT is one of the main causes of the development of ischaemic cardio-embolic cardiovascular events (CVE) after MI and the determination of the source of cardiac embolus is crucial for the initiation of adequate anticoagulant therapy in secondary prevention. Echocardiography holds an irreplaceable place in the diagnosis of LVT, contrast enhancement provides higher sensitivity. The gold standard for LVT diagnosis is cardiac magnetic resonance imaging, but it is not suitable as a basic screening test. In patients with already diagnosed LVT, it is necessary to adjust antithrombotic therapy by starting warfarin anticoagulation for at least 6 months with the need for echocardiographic follow-up to detect thrombotic residues. The effect of prophylactic administration of warfarin in high-risk patients after anterior AMI does not outweigh the risk of severe bleeding complications and does not result in a decrease in mortality and morbidity. At the present time, there is not enough evidence to use direct oral anticoagulants in this indication.

Related Concept Videos
 01:30
Venous Thrombosis I: Introduction
 01:29
Venous Thrombosis III: Interprofessional Care
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:29
Pulmonary Embolism I: Introduction
 01:27
Pulmonary Embolism III: Nursing Management
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies