Bloodstream infections in critically ill patients: an expert statement
Related Experiment Video
Updated: Dec 28, 2025
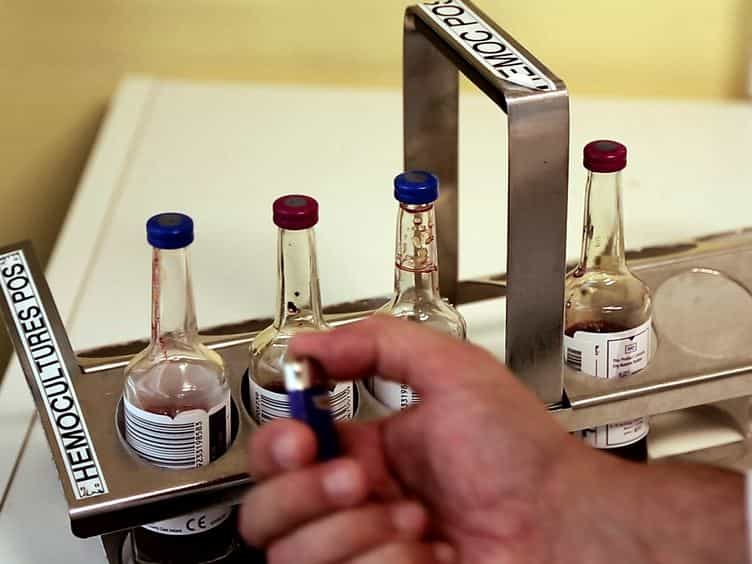
Preparation of a Blood Culture Pellet for Rapid Bacterial Identification and Antibiotic Susceptibility Testing
Published on: October 15, 2014
Jean-François Timsit1,2, Etienne Ruppé3,4, François Barbier5
1AP-HP, Hôpital Bichat, Medical and Infectious Diseases ICU, 75018, Paris, France. jean-francois.timsit@aphp.fr.

Abstract:
Bloodstream infection (BSI) is defined by positive blood cultures in a patient with systemic signs of infection and may be either secondary to a documented source or primary-that is, without identified origin. Community-acquired BSIs in immunocompetent adults usually involve drug-susceptible bacteria, while healthcare-associated BSIs are frequently due to multidrug-resistant (MDR) strains. Early adequate antimicrobial therapy is a key to improve patient outcomes, especially in those with criteria for sepsis or septic shock, and should be based on guidelines and direct examination of available samples. Local epidemiology, suspected source, immune status, previous antimicrobial exposure, and documented colonization with MDR bacteria must be considered for the choice of first-line antimicrobials in healthcare-associated and hospital-acquired BSIs. Early genotypic or phenotypic tests are now available for bacterial identification and early detection of resistance mechanisms and may help, though their clinical impact warrants further investigations. Initial antimicrobial dosing should take into account the pharmacokinetic alterations commonly observed in ICU patients, with a loading dose in case of sepsis or septic shock. Initial antimicrobial combination attempting to increase the antimicrobial spectrum should be discussed when MDR bacteria are suspected and/or in the most severely ill patients. Source identification and control should be performed as soon as the hemodynamic status is stabilized. De-escalation from a broad-spectrum to a narrow-spectrum antimicrobial may reduce antibiotic selection pressure without negative impact on mortality. The duration of therapy is usually 5-8 days though longer durations may be discussed depending on the underlying illness and the source of infection. This narrative review covers the epidemiology, diagnostic workflow and therapeutic aspects of BSI in ICU patients and proposed up-to-date expert statements.

Related Concept Videos
 01:28
Acute Pyelonephritis II: Diagnostic Studies and Management
 01:30
Pneumonia III: Complications and Assessment
 01:25
Endocarditis I: Introduction
 01:22
Healthcare Associated Infections II: Preventive Measures
The best practices for preventing healthcare-associated infections include hand hygiene, patient risk...
 01:26
Healthcare Associated Infections I: Iatrogenic, Exogenic and Endogenic
HAIs significantly increase the cost of health care. Extended stays in healthcare institutions, increased disability, increased costs of medications, including specialized antibiotics, and prolonged recovery times add to the patient's expenses and the healthcare institution and funding bodies.
 01:26
Factors Affecting the Risk of Infection
The integrity and count of the white blood cells help the body resist pathogens and fight infection. When impaired, it reduces the body's resistance to pathogens. The acidic pH levels of the gastrointestinal, genitourinary tracts, and skin...