Related Experiment Video
Updated: Dec 28, 2025
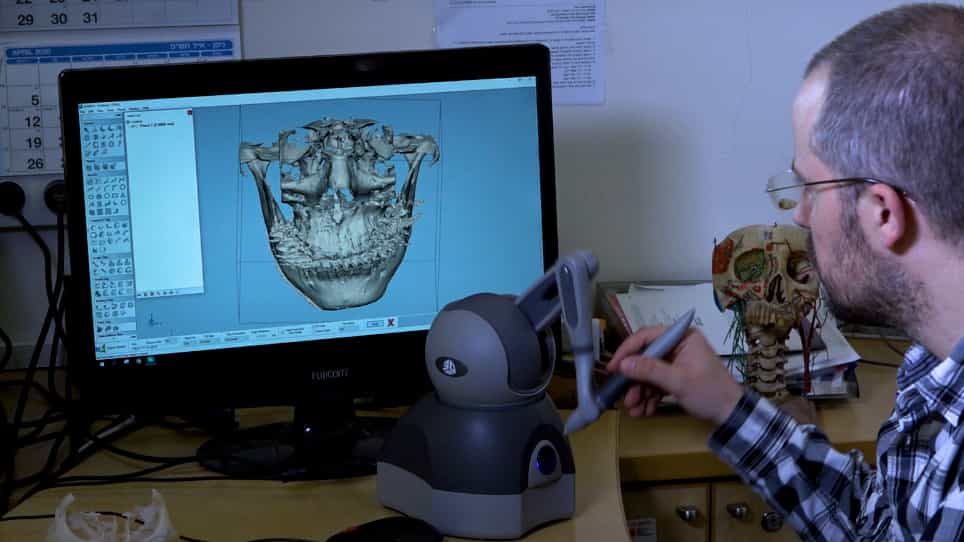
Treatment of Facial Deformities using 3D Planning and Printing of Patient-Specific Implants
Published on: May 23, 2020
Oblique Lateral Closing-Wedge Osteotomy for Cubitus Varus in Skeletally Immature Patients
Dustin A Greenhill1, Scott H Kozin2, Michael Kwon1
1St. Christopher's Hospital for Children, Philadelphia, Pennsylvania.

Background:
We perform an oblique lateral closing-wedge osteotomy of the distal end of the humerus to correct cubitus varus deformity in children. This deformity is often the consequence of undertreatment, malreduction, or malunion of supracondylar humeral fractures1. Although standard arcs of motion may be altered, cosmesis was traditionally considered a primary surgical indication. However, uncorrected cubitus varus leads to posterolateral rotatory instability of the elbow (PLRI)2, lateral condylar fractures3, snapping medial triceps, and ulnar nerve instability4. A contemporary understanding of these delayed sequelae has expanded our current indications. Detailed parameters predictive of late sequelae are needed to further specify surgical indications.
Description:
We remove an oblique lateral closing wedge from the distal end of the humerus via a standard lateral approach. The osteotomy is angled away from the varus joint line such that lateral cortices after reduction lack prominence. Kirschner wires provide adequate fixation in young patients. In older children, extension is simultaneously corrected, and fragments are stabilized via plate osteosynthesis.
Alternatives:
Patients who decline surgery are counseled regarding risks of delaying treatment until symptoms are present. PLRI manifests as lateral elbow pain or instability while rising from a chair. Once symptomatic, the lateral ulnar collateral ligament (LUCL) is irreversibly attenuated and morphologic changes in the ulnohumeral joint necessitate more extensive surgery to include distal humeral osteotomy, LUCL reconstruction, and possibly ulnar nerve transposition5. Alternative osteotomy techniques are described and categorized as simple lateral closing wedge, step-cut6-9, dome, 3-dimensional10, or distraction osteogenesis. Simple closing-wedge osteotomies include a distal cut parallel to the joint line and retain a problematic lateral prominence (if the medial cortex is intact or the distal end of the humerus is not translated medially)11,12. Step-cut osteotomies theoretically minimize this lateral prominence while enhancing inherent stability. However, these additional cuts mandate wide surgical exposure despite similar outcomes13. Three-dimensional planning employs computed tomography to create expensive anatomic cutting guides that address varus, extension, and internal rotation. However, residual internal rotation is generally well tolerated, derotation is associated with loss of fixation, and the extension deformity will successfully remodel in patients who are <10 years old14. We employ 3-dimensional planning in skeletally mature patients with complex deformity and no remodeling potential.
Rationale:
The oblique lateral closing wedge is ideal for skeletally immature patients because it is simple, reproducible, and efficient. It avoids the lateral prominence without increasing complexity or complications.
More Related Videos
 08:15
Three-Dimensional Preoperative Virtual Planning in Derotational Proximal Femoral Osteotomy
Published on: February 17, 2023
 07:35
Creating Rigidly Stabilized Fractures for Assessing Intramembranous Ossification, Distraction Osteogenesis, or Healing of Critical Sized Defects
Published on: April 11, 2012
Related Concept Videos
 01:27
Cranial Bones: Lateral View
The temporal bone forms the lower lateral side of the skull. The temporal bone is subdivided into several regions. The flattened upper portion is the squamous portion of the temporal bone. Below this area and projecting anteriorly is the zygomatic process of the temporal bone, which forms the posterior portion of the zygomatic arch. Posteriorly is the mastoid portion of the temporal bone. Projecting...
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...
 01:15
Bones of the Upper Limb: Ulna
 01:19
Bones of the Upper Limb: Humerus
 01:16
Bones of the Lower Limb: Femur and Patella