Related Experiment Video
Updated: Dec 28, 2025
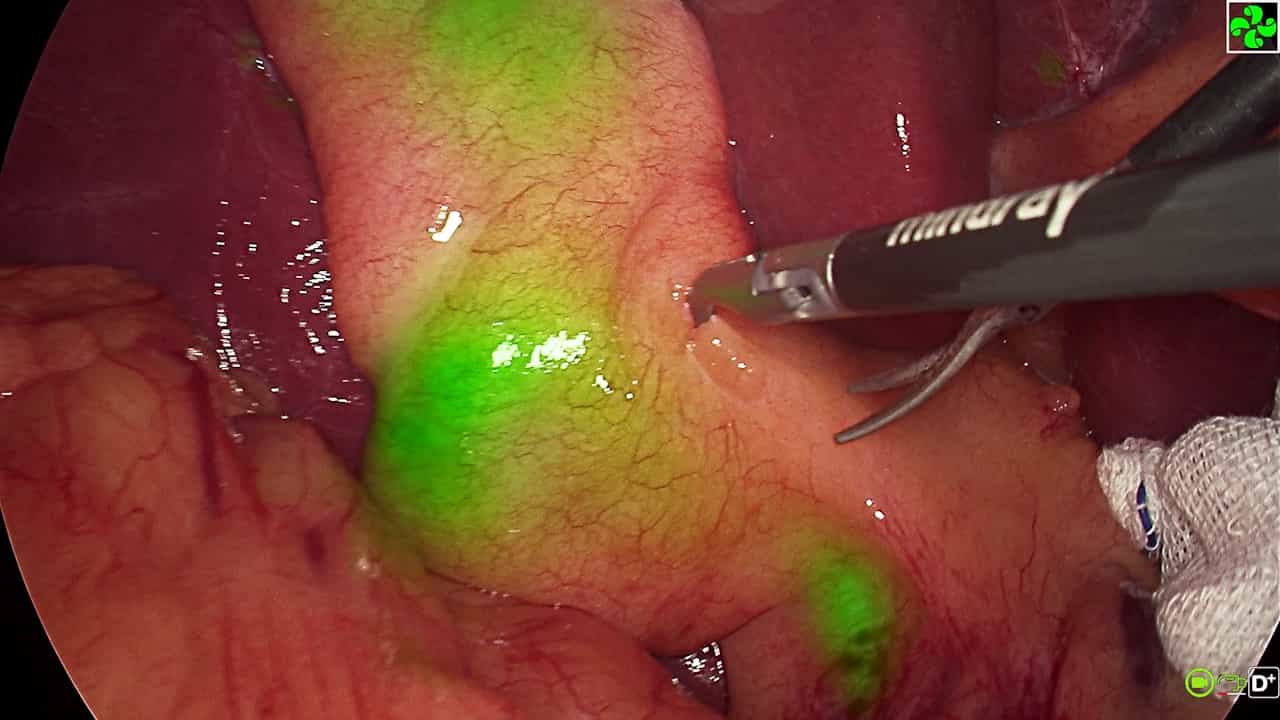

Laparoscopic Cholecystectomy with Indocyanine Green Fluorescence: Choledochoscopic Stone Extraction and Primary Duct Suture
Published on: November 25, 2025
Endoscopic transpapillary gallbladder drainage for acute cholecystitis is feasible for patients receiving
Ryota Sagami1, Kenji Hayasaka1, Tetsuro Ujihara1
1Departments of, Department of, Gastroenterology, New Tokyo Hospital, Chiba, Japan.

Insights
Endoscopic transpapillary gallbladder drainage (ETGBD) is safe for patients with acute cholecystitis on antithrombotic therapy (ATT). This study found no increased bleeding risk with ETGBD in patients continuing ATT, suggesting it
Area of Science:
- Gastroenterology and Hepatology
- Interventional Endoscopy
- Surgical Risk Management
Background:
- Patients with acute cholecystitis on antithrombotic therapy (ATT) face elevated bleeding risks during surgical or percutaneous interventions.
- Endoscopic transpapillary gallbladder drainage (ETGBD) is a recommended alternative, but robust evidence regarding its safety in ATT patients is limited.
Purpose of the Study:
- To evaluate the safety and efficacy of ETGBD in patients with acute cholecystitis who are undergoing antithrombotic therapy.
- To compare bleeding complication rates between patients continuing ATT and those discontinuing or not using ATT during ETGBD.
Main Methods:
- A retrospective multicenter study enrolled 130 patients with acute cholecystitis who underwent ETGBD.
- Patients were stratified into an ATT group (continued ATT) and a Non-ATT group (discontinued or no ATT).
- Primary outcome was bleeding complications; secondary outcomes included technical success, clinical success, and overall complication rates.
Main Results:
- No bleeding complications were observed in either the ATT group (n=83) or the Non-ATT group (n=47).
- Technical success rates (84.3% vs 89.4%) and clinical success rates (97.1% vs 100%) showed no significant differences between groups.
- Overall early complications were low (3.1%), including mild pancreatitis and cholangitis; 12-month stent patency was 69.0%.
Conclusions:
- ETGBD can be performed without an increased risk of bleeding complications in patients with acute cholecystitis receiving ATT.
- ETGBD emerges as a potentially ideal and safe drainage method for this high-risk patient population.
Objectives:
Patients with acute cholecystitis receiving antithrombotic therapy (ATT) have an increased risk of bleeding complications during surgery and percutaneous drainage. Endoscopic transpapillary gallbladder drainage (ETGBD) is recommended for such cases; however, evidence is limited. To investigate this issue further, we performed a retrospective multicenter study.
Methods:
One hundred thirty patients with acute cholecystitis who underwent ETGBD were enrolled. They were divided into an ATT group (continuation of ATT on the day of the procedure and/or heparin substitution) and a Non-ATT group (discontinuation or no use of ATT). The primary outcome was bleeding complication rate, and the secondary outcomes were technical success rate, clinical success rate and total complication rate.
Results:
Eighty-three patients were enrolled in the ATT group, and 47 were enrolled in the Non-ATT group. In the ATT group, 42.2% continued multi-agent ATT. No bleeding complications occurred in either group. There were no significant differences between the ATT and Non-ATT groups in the technical success rate (84.3% vs 89.4%, P = 0.426 respectively) or the clinical success rate (97.1% vs 100%, P = 0.259, respectively). The overall early complication rate was 3.1% (4/130): mild pancreatitis (n = 3) and cholangitis (n = 1). Stent dysfunction was found in 10.9% of patients (at 196 days on average), and the 12-month stent patency rate was 69.0%.
Conclusions:
No significant difference was found in the bleeding complication rate between ETGBD with and without ATT. ETGBD may be an ideal drainage method for patients with acute cholecystitis receiving ATT.
Related Concept Videos
 01:26
Endoscopic Procedures V: ERCP
Patient...
 01:29
Venous Thrombosis III: Interprofessional Care
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment: