Related Experiment Video
Updated: Dec 28, 2025


Multiplex Therapeutic Drug Monitoring by Isotope-dilution HPLC-MS/MS of Antibiotics in Critical Illnesses
Published on: August 30, 2018
Clinical audit of gentamicin use by Bayesian pharmacokinetic approach in critically ill children
Kannan Sridharan1, Amal Al Daylami2
1Department of Pharmacology & Therapeutics, College of Medicine and Medical Sciences, Arabian Gulf University, Manama, Bahrain.

Insights
Critically ill children, especially neonates, received higher gentamicin doses, leading to altered pharmacokinetics. Standardized pediatric treatment guidelines are needed for optimal gentamicin dosing and to reduce acute kidney injury risk.
Area of Science:
- Pediatric Critical Care Medicine
- Pharmacokinetics and Pharmacodynamics
- Antibiotic Stewardship
Background:
- Critically ill children exhibit altered gentamicin pharmacokinetics (PK).
- Gentamicin dosing requires careful consideration of PK parameters like peak concentration (Cmax), trough concentration (Cmin), and area under the concentration-time curve (AUC).
Purpose of the Study:
- To audit gentamicin use in critically ill children using Bayesian pharmacokinetic modeling.
- To evaluate gentamicin exposure (Cmax, Cmin, AUC) across different pediatric age groups.
- To assess the incidence of acute kidney injury (AKI) in relation to gentamicin exposure.
Main Methods:
- Bayesian adaptive control models were used to estimate gentamicin Cmax and AUC0-t.
- Seventy-three critically ill children with available serum gentamicin concentrations were analyzed (961 doses, 143 concentrations).
- Pediatric Risk, Injury, Failure, Loss, End Stage Renal Disease (pRIFLE) criteria were used to identify AKI.
Main Results:
- Gentamicin AUC0-24 was higher in younger children (neonates, infants) and decreased with age.
- Neonates had a higher risk of exceeding target Cmax levels (>10 mg/L).
- Children with augmented renal clearance had lower AUC0-24 and were less likely to achieve target levels; nearly one-third met pRIFLE criteria for AKI.
Conclusions:
- Higher initial gentamicin doses and peak concentrations were observed in neonates and infants compared to older critically ill children.
- There is a need for uniform, pediatric-specific standard treatment guidelines for gentamicin dosing.
- Optimizing gentamicin dosing in critically ill children is crucial for efficacy and minimizing nephrotoxicity.
Introduction:
Critically ill children tend to have altered gentamicin pharmacokinetics (PK); and so we carried out an audit of gentamicin use using the estimated peak concentrations (Cmax), trough concentrations (Cmin) and area-under-the-concentration-time curve (AUCs) by Bayesian approach.
Methods:
Critically ill children with at least one serum gentamicin concentrations available were recruited. We used multiple models Bayesian adaptive control to estimate Cmax, and AUC0-t following each dose. Pediatric risk, injury, failure, loss, end stage renal disease (pRIFLE) criteria was used to identify the incidence of acute kidney injury (AKI).
Results:
Seventy-three children (961 doses and 143 concentrations) were analysed. AUC0-24 was observed to be higher in earlier age groups with a steady decline in older children. Similar changes were observed in Cmax, Cmin and AUC0-24 at steady state. Significantly higher proportions of children in the other age groups were estimated to have Cmax between 5 and 10 mg/L compared to neonates. Neonates had a higher risk of Cmax above 10 mg/L. Patients with augmented renal clearance exhibited lower AUC0-24 and reduced proportion achieving the target AUC0-24 levels. Nearly one-third of children were observed to meet the pRIFLE criteria for AKI.
Conclusion:
We observed higher initial doses and peak concentrations of gentamicin in neonates and infants compared to older age groups in critically ill children. Uniformity in the paediatric-specific standard treatment guidelines for gentamicin is the need of the hour.
More Related Videos
 09:17
A Robust Pneumonia Model in Immunocompetent Rodents to Evaluate Antibacterial Efficacy against S. pneumoniae, H. influenzae, K. pneumoniae, P. aeruginosa or A. baumannii
Published on: January 2, 2017
 07:27
How to Administer Near-Infrared Spectroscopy in Critically ill Neonates, Infants, and Children
Published on: August 19, 2020
Related Concept Videos
 01:15
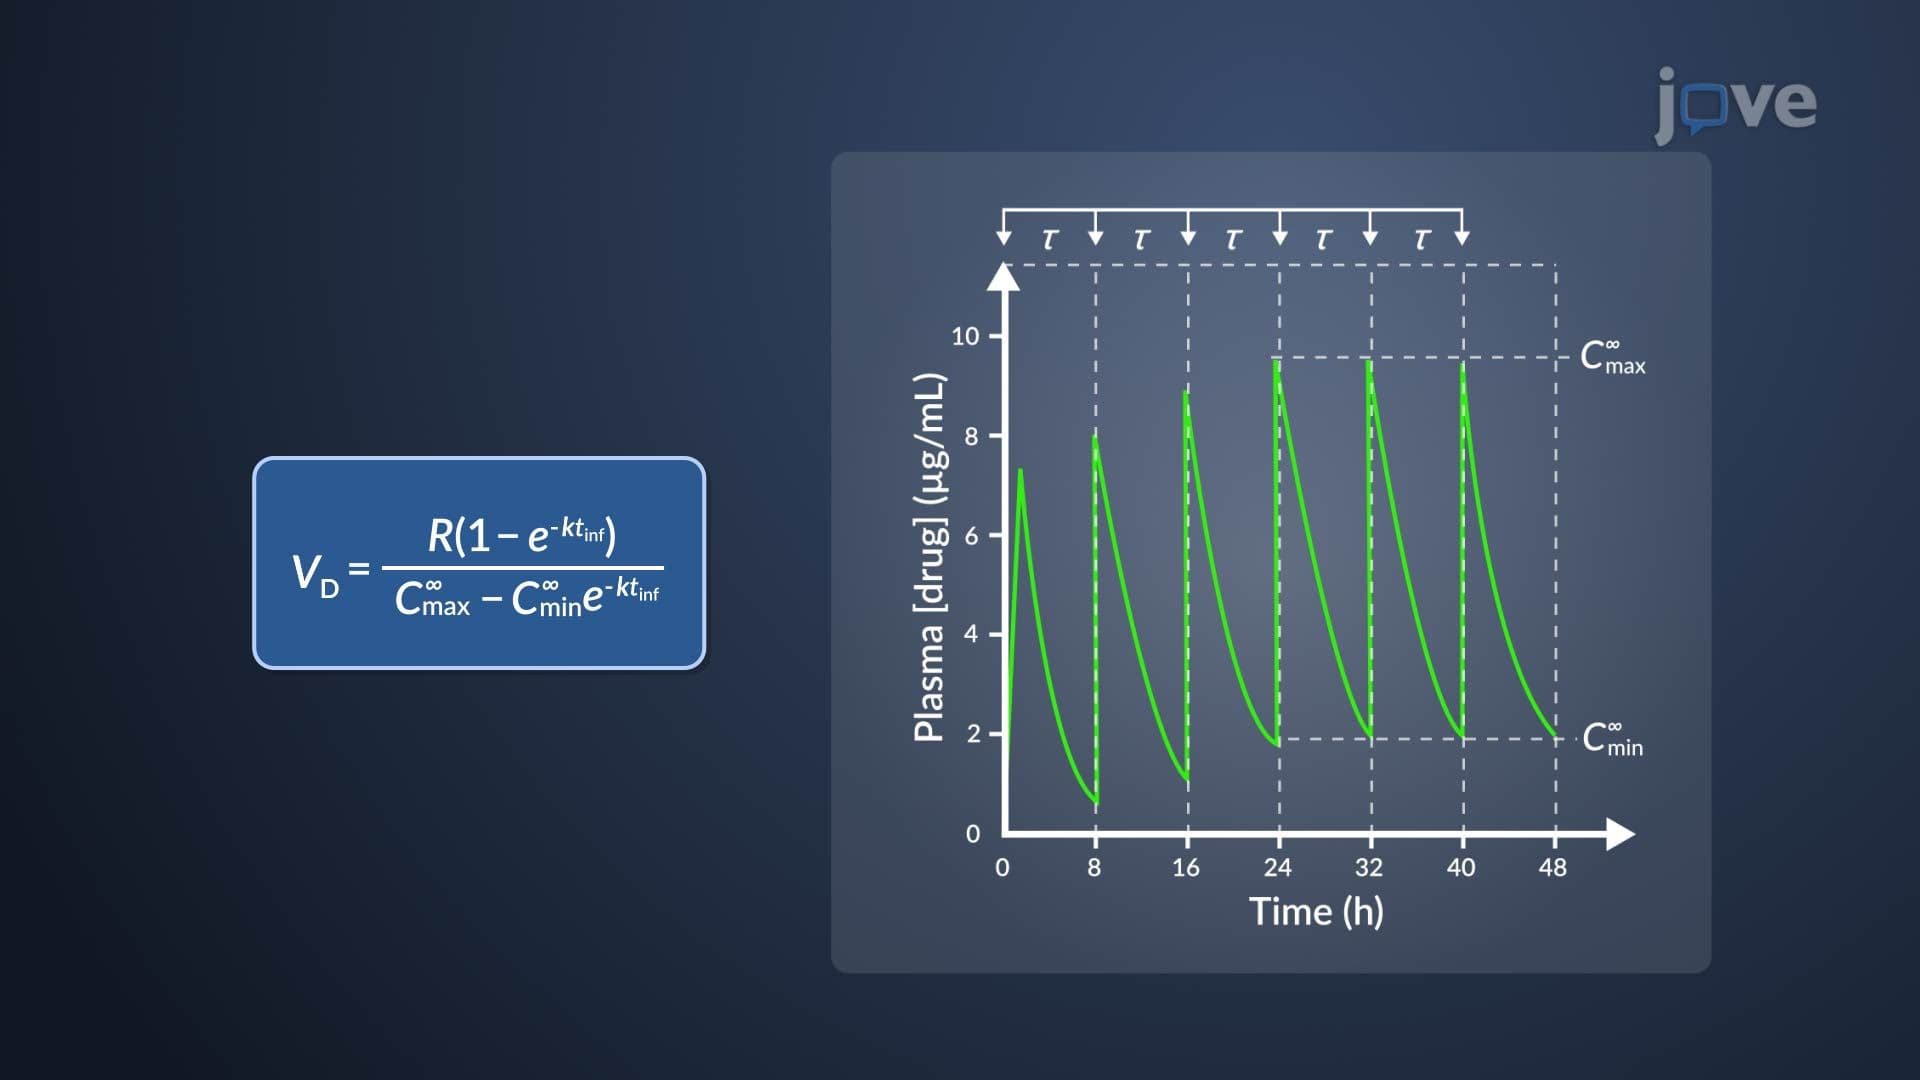
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:20
Estimation of k and VD of Aminoglycosides
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution
 01:18
Pharmacokinetics in Geriatric Patients: Effect of Age on Drug Excretion
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism