Related Experiment Video
Updated: Dec 28, 2025
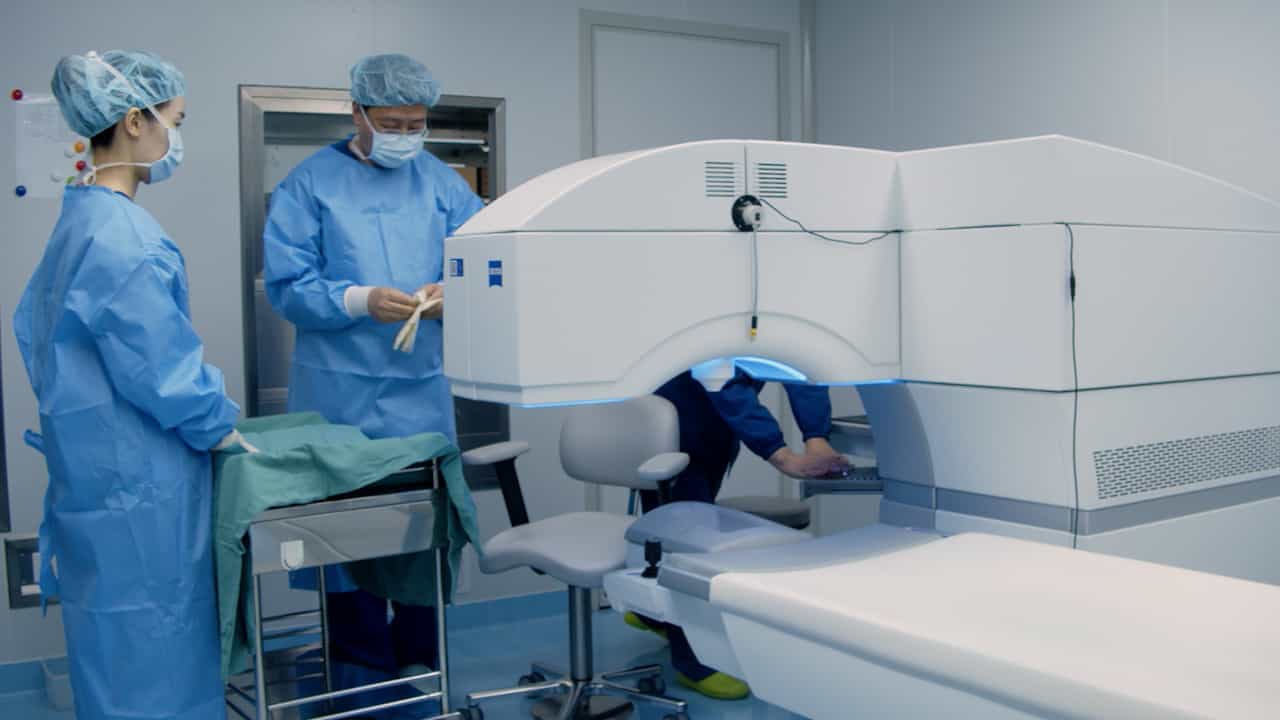

Ye's Swing Technique for Small-incision Lenticule Extraction Surgery
Published on: June 27, 2025
[Assessment of corneal biomechanical changes after small incision lenticule extraction with Pentacam and Corvis ST]
M Y Zhang1, F J Zhang2, Y Z Song2
1Beijing Tongren Eye Center, Beijing Tongren Hospital, Beijing Ophthalmology and Science Key Lab., Capital Medical University, Beijing 100730, China (Zhang Mingyue is now working at Department of Ophthalmology, Civil Aviation General Hospital, Beijing 100123, China).

Abstract:
Objective: To investigate the application value of Pentacam combined with Corvis ST in evaluation of the changes of corneal biomechanics after femtosecond laser small incision lenticule extraction (SMILE) in Chinese myopia with an irregular cornea. Methods: The clinical records for 104 eyes of 57 patients who received SMILE in the Refractive Center of Beijing Tongren Hospital during January 2018 and May 2018 were collected. According to the keratoconus severity index (KSI), they were divided into two groups: regular corneal group (KSI<15%) and irregular corneal group (KSI: 15% to 25%). In both groups, the anterior corneal surface radius curvature was>7.25 mm (K<46.50 diopters), the posterior corneal surface radius curvature was>5.90 mm, the thinnest pachymetry was>490 μm, and best corrected visual acuity was ≥1.0. The vision, refraction, and corneal biomechanics before and after SMILE were assessed. The Topographic and Biomechanics Index (TBI) was analyzed by Pentacam combined with Corvis ST. Results: Before SMILE, the Corvis Biomechanical Index (CBI), TBI, and Belin/Ambrósio Deviation Normalized Index (BADD) of the irregular corneal group were significantly higher (t=-2.17, -6.78, -4.37, P<0.05) than the regular corneal group, while the stiffness parameter (SPA1) was significantly lower (t=2.58, P=0.011) compared to the regular corneal group (P<0.05). In the irregular group, the TBI was (0.28±0.2); the maximum value was 0.03, and the minimum value was 0.43. The CBI was (0.09±0.21); the maximum value was 0.00, and the minimum value was 0.54. The BADD was (1.33±0.47); the maximum value was 0.42, and the minimum value was 2.26. In the regular group, the TBI was (0.05±0.08); the maximum value was 0.00, and the minimum value was 0.20. The CBI was (0.01±0.03); the maximum value was 0.00, and the minimum value was 0.17. The BADD was (0.92±0.46); the maximum value was 0.00, and the minimum value was 1.64. There was no significant difference between two groups in age (t=0.20, P=0.508), central corneal thickness (t=1.64, P=0.104), biomechanical corrected IOP (t=0.73, P=0.468), max inverse radius (t=-0.24, P=0.815), spherical equivalent (t=-0.97, P=0.335), and best corrected visual acuity (t=0.21, P=0.833). After SMILE, the deformation amplitude in the irregular group was significantly higher at 1 month and 3 months (t=-3.13, -3.09, P<0.05). The irregular group had a significantly higher deformation amplitude ratio at 1 week, 1 month, and 1 year (t=-2.72, -3.39, -2.51, P<0.05). The SPA1 in the irregular group was significantly lower than the regular group at 1 week, 1 month, and 3 months (t=2.11, 2.73, 3.70, P=0.335, 0.010,<0.001). The changes of deformation amplitude (t=0.50, -1.10, -0.73, 2.12, P>0.05), max inverse radius (t=-1.52, -1.41, 0.01, -0.79, P>0.05), and SPA1(t=0.89, 0.90, 1.12, 0.90, P>0.05) after SMILE were similar between the irregular and regular groups, except that at 1 month after SIMILE, the deformation amplitude ratio changed more significantly in the irregular group (t=-3.01, P=0.003). Conclusions: The changes of corneal biomechanics in the groups of regular cornea and irregular cornea were stable with no significant difference during 1 year of post-SMILE. The diagnosis based on the corneal topography and corneal biomechanics is of certain significance for the screening of early keratoconus before keratorefractive surgery. (Chin J Ophthalmol, 2020, 56:103-109).

