Dose-Dependent Hyperkalemia Among Hospitalized, HIV-Infected Patients Receiving Sulfamethoxazole/Trimethoprim
Related Experiment Video
Updated: Dec 27, 2025

Multiplex Therapeutic Drug Monitoring by Isotope-dilution HPLC-MS/MS of Antibiotics in Critical Illnesses
Published on: August 30, 2018
Celeste R Caulder1, Caitlin S Kocherla2, Zaina P Qureshi3
1University of South Carolina College of Pharmacy, Columbia, SC, USA.

Abstract:
Background: Sulfamethoxazole-trimethoprim (SXT) therapy is commonly used in HIV-infected patients and is associated with hyperkalemia and elevated serum creatinine (SCr). Objective: The purpose of this study was to examine the frequency of hyperkalemia and elevated SCr in hospitalized, HIV-infected patients receiving SXT. Methods: This was a retrospective, single-center cohort study. HIV-infected hospitalized patients receiving a minimum of 3 consecutive days of SXT were included. Patients were grouped according to high dose (≥10 mg/kg/d) and low dose (<10 mg/kg/d) trimethoprim. The primary end point was the frequency of hyperkalemia, severe hyperkalemia, and elevated SCr. Secondary end points included an evaluation of concomitant potassium-altering medications and concomitant nephrotoxic drugs. Results: A total of 100 consecutive patients were selected from all possible patients who met inclusion criteria. Overall, 47 patients experienced at least 1 adverse drug event (ADE) of either hyperkalemia or increased SCr, with 20 patients experiencing these ADEs in the low-dose group and 27 patients experiencing these ADEs in the high-dose group (P = 0.229). The ADEs of hyperkalemia or increased SCr occurred after a shorter period (5.5 vs 8.7 days) in the high-dose group (P = 0.049). Overall frequency of elevated SCr was 24% and of elevated serum K was 36%. Hyperkalemia requiring a therapeutic intervention occurred in 12 patients in the high-dose group compared with 2 in the low-dose group (P = 0.009). Conclusion and Relevance: Rates of elevated SCr and hyperkalemia in hospitalized HIV-infected patients receiving SXT are significant. Hyperkalemia requiring intervention is more common in patients receiving high-dose SXT.

Related Concept Videos
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:24
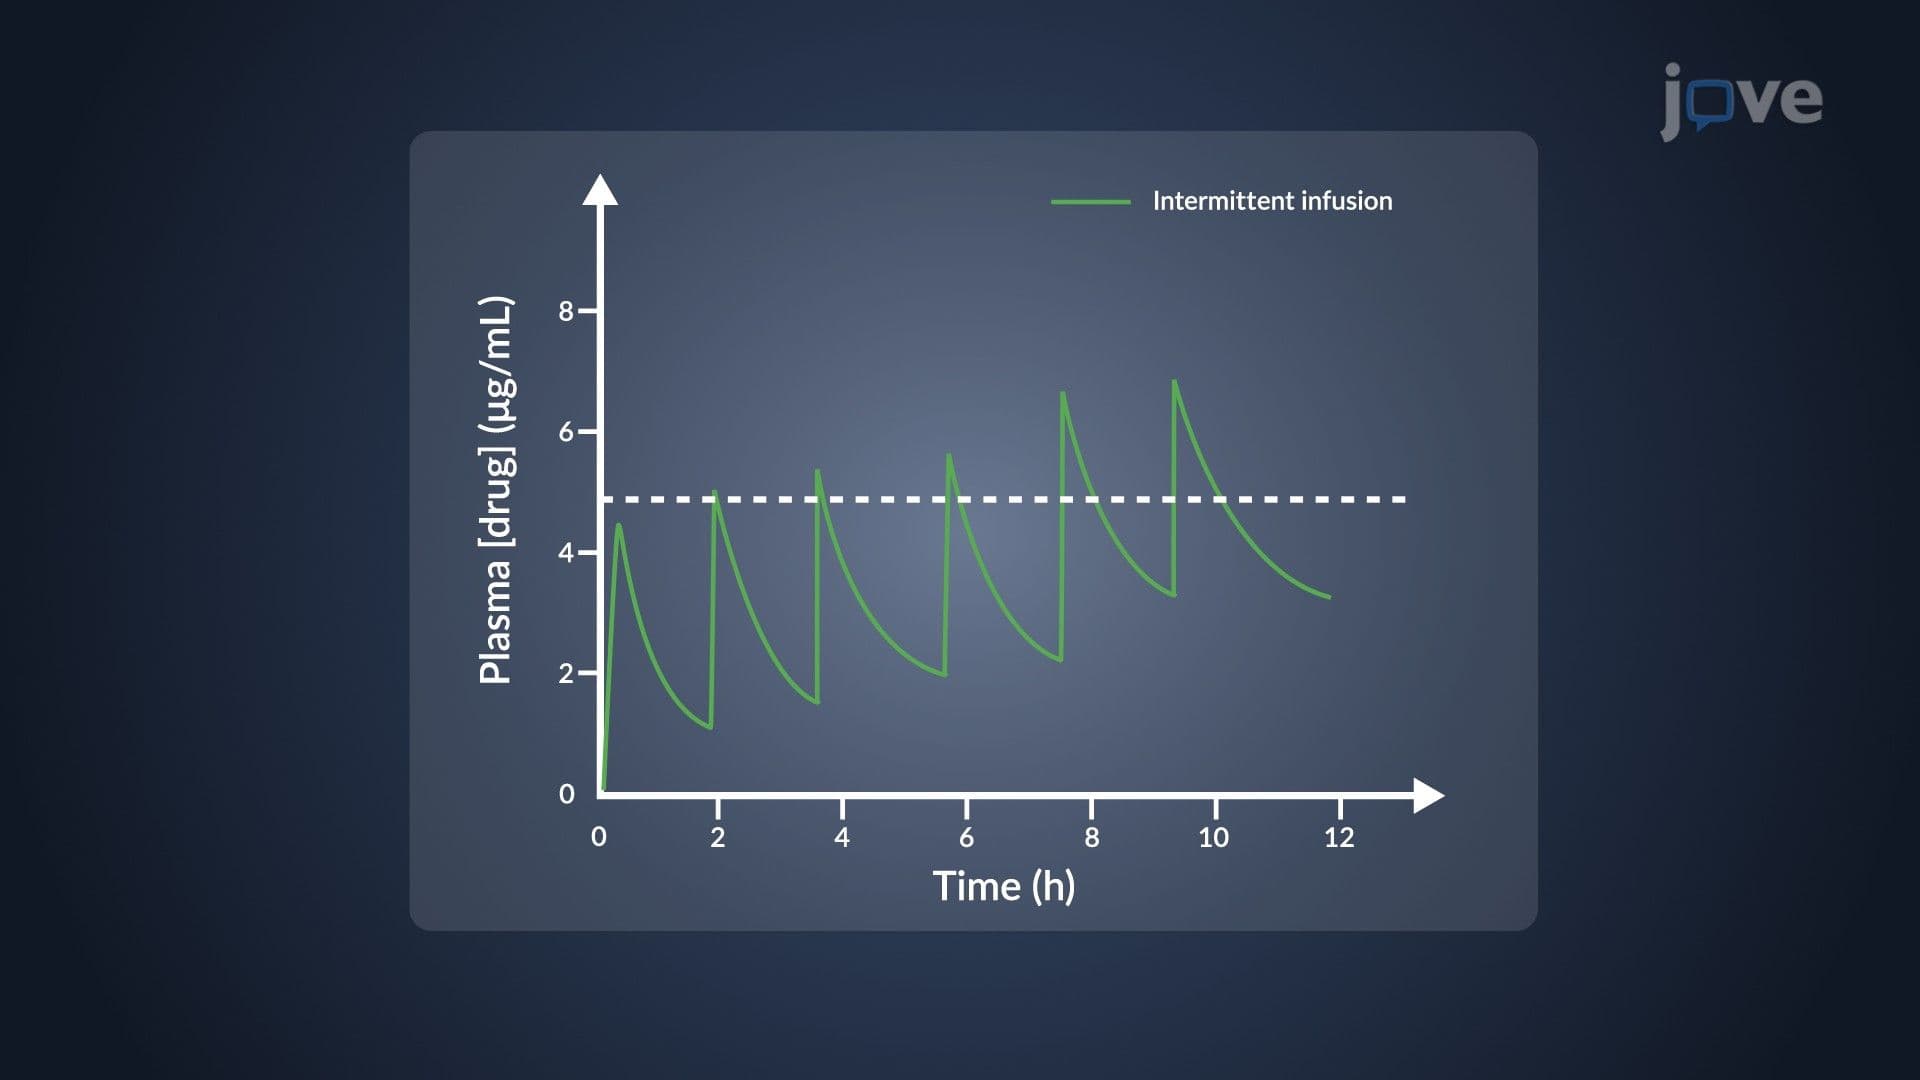
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:08
Effect of Hepatic Disease on Pharmacokinetics: Dose Adjustments Due to Hepatic Impairment
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...