Shorter corridors can be used for the six-minute walk test in subjects with chronic lung diseases
Related Experiment Video
Updated: Dec 27, 2025
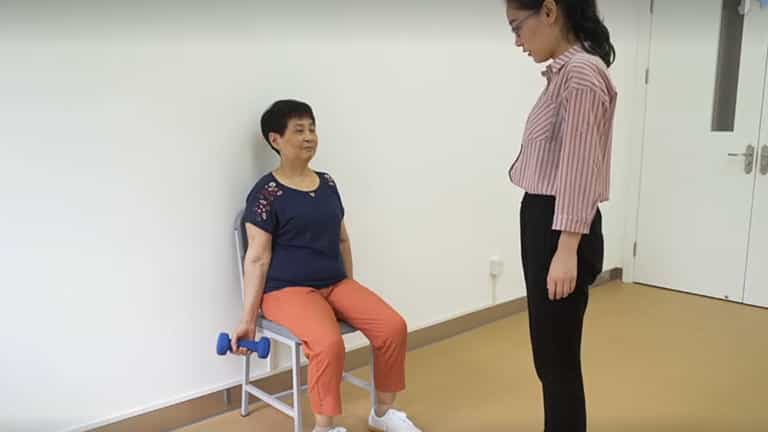
Home-Based Prescribed Pulmonary Exercise in Patients with Stable Chronic Obstructive Pulmonary Disease
Published on: August 24, 2019
Laura Gochicoa-Rangel1, María C Ramírez-José2, Prysila Troncoso-Huitrón2
1Departamento de Fisiología Respiratoria, Instituto Nacional de Enfermedades Respiratorias "Ismael Cosío Villegas", Tlalpan 4502, Sección XXI, Alcaldía Tlalpan, Ciudad de México, 14080, Mexico; Laboratorio de Función Pulmonar, Insituto de Desarrollo e Innovación en Fisiología Respiratoria S. de R.L, Av. Baja California 67-301, Romar Sur, Alcaldia Cuauhtémoc, Ciudad de México, 06760, Mexico.

Background:
The main limitation of the six-minute walk test (6-MWT) is that not all pulmonary function testing facilities have an indoor flat, 30-m-long corridor. Therefore, this study aimed 1) to evaluate the correlation and agreement of the distances walked in 30-m- vs. 15-m-long corridors by subjects with chronic lung diseases (CLD group) and 2) to compare the levels of oxygen saturation (nSpO2), blood pressure (BP), heart rate recovery at minute one post-exercise (HRR1), and Borg scale scores for dyspnea and fatigue between the two distances walked.
Methods:
A prospective, cross-sectional study was conducted at the National Institute of Respiratory Diseases in Mexico City. Subjects with chronic lung diseases and healthy adults were invited to participate. The distance of the 6-MWT was randomly assigned based on whether the first test was in the 15-m or 30-m corridor.
Results:
Ninety individuals were included; the correlation in meters walked between the two corridors was r = 0.96 in CLD; the 95% limits of agreement for the 6-MWT ranged from -73 to +37 m. Most subjects walked further in the 30-m corridor (82%); however, the percent predicted values for the CLD group were 3.5% lower for the 15-m corridor than the 30-m corridor. Only 10.5% of the subjects with CLD would have been falsely classified as having a normal 6-MWT (false negative). No significant differences in the nSpO2, Borg scale, BP or HRR1 were found between the two 6-MWT corridor lengths.
Conclusion:
The 6-MWT can be performed using a 15-m corridor in subjects with CLD, and the results for the distance walked, HRR1, nSpO2, and Borg scale scores are similar to between the 15-m and 30-m corridors.
More Related Videos
 04:24
Acupoint Application as a Traditional Chinese Medicine Treatment for Fatigue Associated with Chronic Obstructive Pulmonary Disease
Published on: September 5, 2025
 08:44
Author Spotlight: Integrating Alveolar-Capillary Reserve Measurements in Exercise Adaptation and Therapeutic Strategies
Published on: February 2, 2024
Related Concept Videos
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:22
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:25
Pulmonary Function Tests
Pulmonary Function Tests are crucial diagnostic tools for assessing respiratory function, particularly in patients with chronic respiratory disorders. They comprehensively evaluate lung volumes, ventilatory function, breathing mechanics, diffusion, and gas exchange. These tests help diagnose pulmonary diseases and play a significant role in monitoring disease progression, evaluating disability, and assessing response to therapy.
PFTs involve using a spirometer, a...
 01:25
Chronic Obstructive Pulmonary Disease-III: Symptoms and Complications.
Symptoms of COPD can be classified as primary or systemic. Primary symptoms relate to reduced airflow, while systemic or extrapulmonary symptoms relate to COPD's broader impact on the body.
Primary Symptoms of COPD:
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction