Related Experiment Video
Updated: Dec 27, 2025

Analysis of Minerals Produced by hFOB 1.19 and Saos-2 Cells Using Transmission Electron Microscopy with Energy Dispersive X-ray Microanalysis
Published on: June 24, 2018
Hyperphosphatemia with low FGF7 and normal FGF23 and sFRP4 levels in the circulation characterizes pediatric
Michael P Whyte1, Fan Zhang2, Deborah Wenkert2
1Center for Metabolic Bone Disease and Molecular Research, Shriners Hospitals for Children - St Louis, St. Louis, MO 63110, USA; Division of Bone and Mineral Diseases, Department of Internal Medicine, Washington University School of Medicine at Barnes-Jewish Hospital, St. Louis, MO 63110, USA.

Abstract:
Hypophosphatasia (HPP) is the inborn-error-of-metabolism caused by loss-of-function mutation(s) of the ALPL gene that encodes the tissue-nonspecific isoenzyme of alkaline phosphatase (TNSALP). TNSALP in healthy individuals is on cell surfaces richly in bone, liver, and kidney. Thus, TNSALP natural substrates accumulate extracellularly in HPP, including inorganic pyrophosphate (PPi), a potent inhibitor of hydroxyapatite crystal formation and growth. Superabundance of extracellular PPi (ePPi) in HPP impairs mineralization of bones and teeth, often leading to rickets during childhood and osteomalacia in adult life and to tooth loss at any age. HPP's remarkably broad-ranging severity is largely explained by nearly four hundred typically missense mutations throughout the ALPL gene that are transmitted as an autosomal dominant or autosomal recessive trait. In the clinical laboratory, the biochemical hallmark of HPP is low serum ALP activity (hypophosphatasemia). However, our experience indicates that hyperphosphatemia from increased renal reclamation of filtered inorganic phosphate (Pi) is also common. Herein, from our prospective single-center study, we document throughout the clinical spectrum of non-lethal pediatric HPP that hyperphosphatemia reflects increased renal tubular threshold maximum for phosphorus adjusted for the glomerular filtration rate (TmP/GFR). To explore its pathogenesis, we studied mineral metabolism and quantitated circulating levels of three phosphatonins [fibroblast growth factor 23 (FGF23), secreted frizzled-related protein 4 (sFRP4), and fibroblast growth factor 7 (FGF7)] in 41 pediatric patients with HPP, 73 with X-linked hypophosphatemia (XLH), and 15 healthy pediatric control (CTR) subjects. The HPP and XLH cohorts had normal serum total and ionized calcium and parathyroid hormone levels (Ps > 0.10) and uncompromised glomerular filtration. In XLH, serum FGF23 was characteristically elevated (P < 0.0001) and despite hypophosphatemia sFRP4 was normal (P > 0.4) while FGF7 was low (P < 0.0001). In HPP, despite hyperphosphatemia serum FGF23 and sFRP4 were normal (Ps > 0.8) while FGF7 was low (P < 0.0001). Subsequently, in rats, we confirmed that FGF7 is phosphaturic. Thus, hyperphosphatemia in non-lethal pediatric HPP is associated with phosphatonin insufficiency together with, as we discuss, ePPi excess and diminished renal TNSALP activity.


Related Concept Videos
 01:27
Roles of Electrolytes: Calcium and Phosphate
The calcium concentration in blood plasma is primarily...
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution
 01:42
Phosphoinositides and PIPs
Different phosphoinositides are synthesized and recruited on the cytosolic face of the plasma membrane. The localization of specific phosphoinositides concentrated in separate membrane...
 01:24
Chronic Kidney Disease II: Clinical Manifestations
 01:33
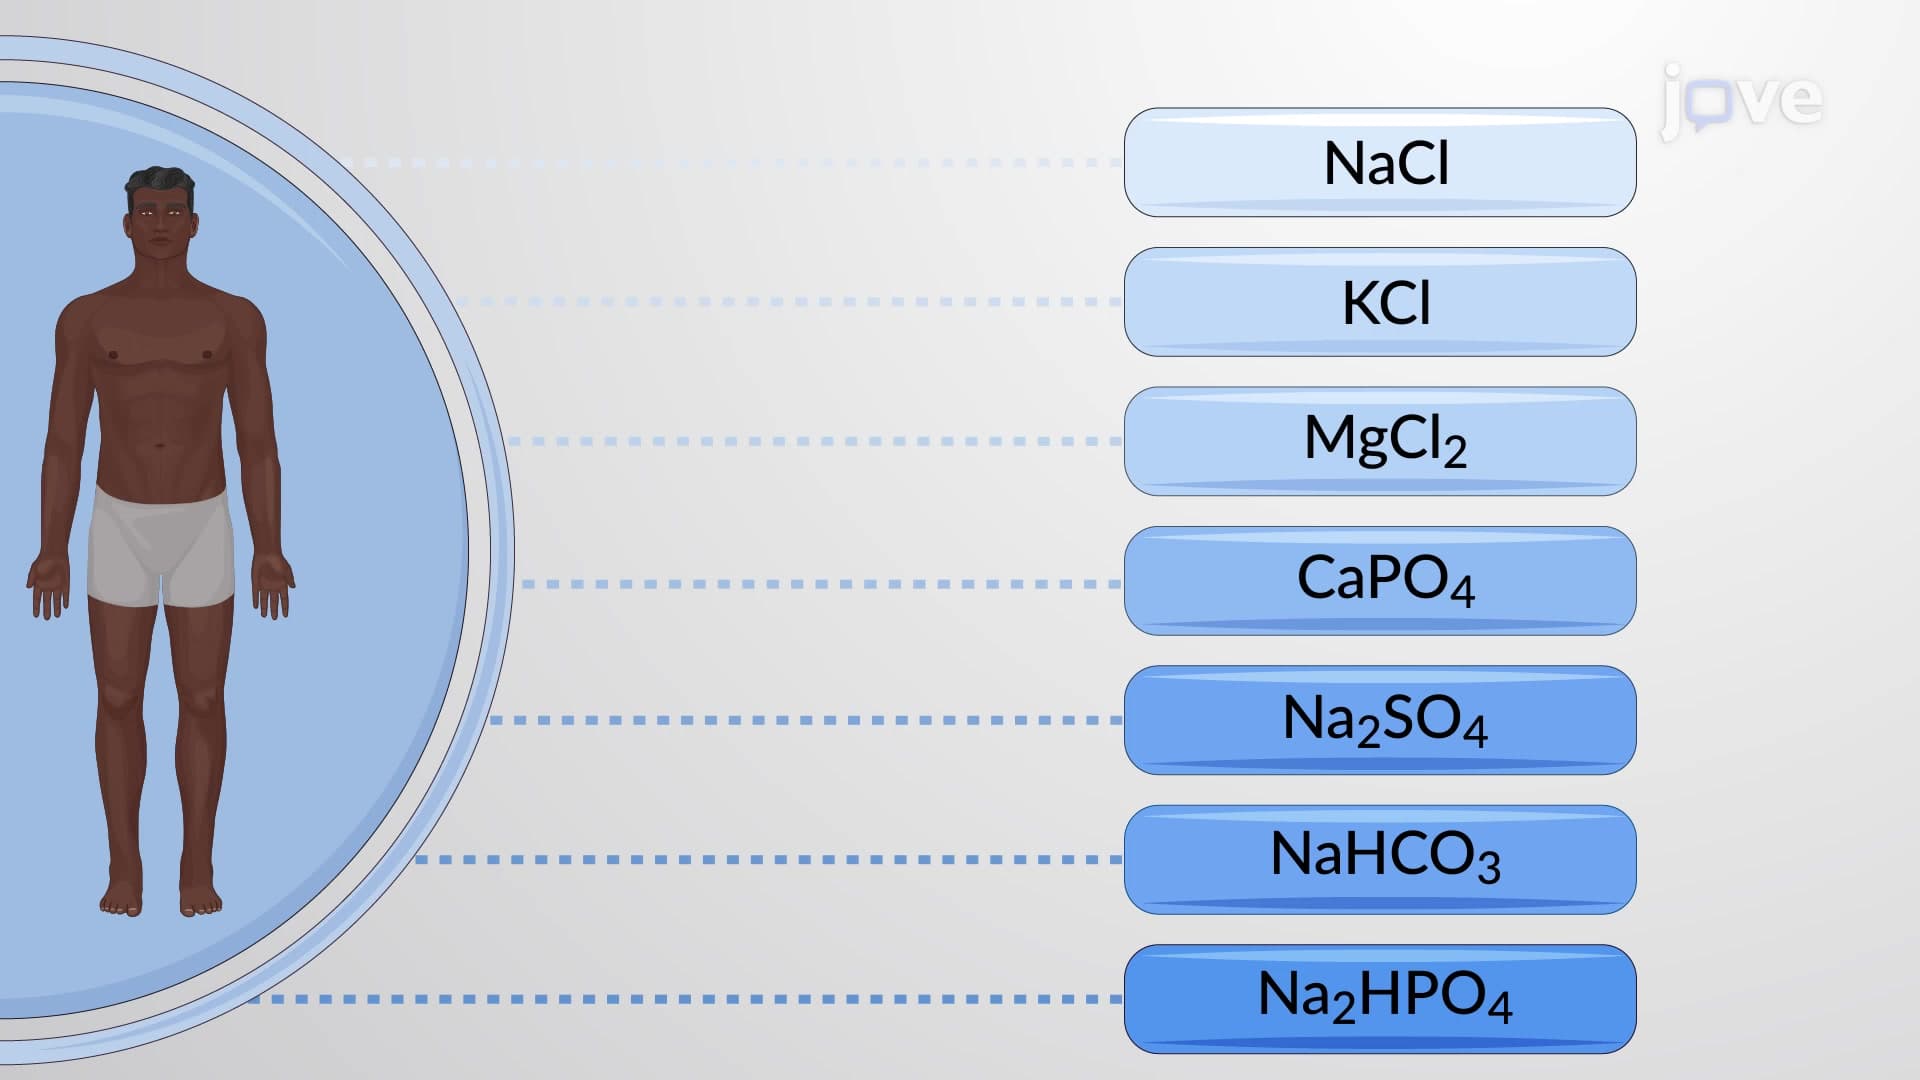
Introduction to Electrolytes
Role of Sodium
One...
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...