Related Experiment Video
Updated: Dec 26, 2025


Author Spotlight: Advancing Early Detection and Treatment of Gastrointestinal Tumors
Published on: February 16, 2024
Helicobacter pylori Gastritis in Children-The Link between Endoscopy and Histology
Ana-Maria Teodora Domșa1, Raluca Lupușoru2,3, Dan Gheban1,4
1Department of Pathology, "Iuliu Hațieganu" University of Medicine and Pharmacy, 400000 Cluj-Napoca, Romania.

Insights
Helicobacter pylori (H. pylori) infection in children often presents with chronic inflammation, primarily pangastritis. While endoscopic nodularity and histological lymphoid follicles suggest infection, invasive testing remains necessary for accurate diagnosis.
Area of Science:
- Pediatric Gastroenterology
- Infectious Diseases
- Gastrointestinal Pathology
Background:
- Helicobacter pylori (H. pylori) infection is a global health challenge, particularly in pediatric populations where acquisition often occurs in childhood.
- Effective management strategies for H. pylori in children require a deep understanding of its impact on the gastric mucosa.
Purpose of the Study:
- To investigate the endoscopic and histopathologic alterations in the gastric mucosa of children diagnosed with H. pylori infection.
- To analyze the relationship between H. pylori infection and specific inflammatory markers in pediatric patients.
Main Methods:
- A retrospective analysis of 248 pediatric patients (0-18 years) undergoing upper gastrointestinal endoscopy (UGE) over five years.
- Review of endoscopy reports and histological slides to record clinical, endoscopic, and histopathologic data.
Main Results:
- H. pylori infection was identified in 33.06% of the pediatric cohort, with no significant differences in age or symptoms compared to uninfected children.
- A strong correlation was observed between H. pylori infection and acute/chronic inflammatory infiltrates, with bacterial load influencing inflammation intensity (p < 0.001).
- Pangastritis was the predominant pattern of inflammation (p = 0.04), characterized by similar inflammatory degrees in the antrum and corpus.
Conclusions:
- Endoscopic findings like antral mucosal nodularity and histological lymphoid follicles are indicative of H. pylori infection in children (p < 0.05).
- Despite suggestive signs, the concordance between endoscopic and histological diagnoses is suboptimal (Cohen's k = 0.42), underscoring the continued need for invasive diagnostic procedures.
Background:
The management of Helicobacter pylori (H. pylori) infection raises important challenges, still being the most common chronic infection worldwide in all age groups. In high-prevalence regions, paediatric patients need a specific focus, as the acquisition of the infection takes place in childhood. The objective of this study was to analyze the endoscopic and histopathologic changes of the gastric mucosa in H. pylori infected children.
Material And Methods:
A retrospective study was performed on consecutive paediatric patients, ranging from 0 to 18 years of age, who underwent an upper gastrointestinal endoscopy (UGE) for a period of 5 years, regardless of their symptomatology. Endoscopy reports and histological slides were reviewed and clinical, endoscopic, and histologic data were recorded.
Results:
A total of 248 patients were included in the study, 82 (33.06%) of them being H. pylori infected. There was no difference in age and symptoms between the infected and noninfected group. A significant association was found between the H. pylori infection and histopathological parameters such as acute and chronic inflammatory infiltrate. The bacterial load influences the intensity of inflammation (p < 0.001). The chronic inflammation was predominant, only 23.2% of the patients displayed acute inflammation (p < 0.0001). The topographic distribution of inflammation was dominated by pangastritis (p = 0.04) with 58.6% of the patients presenting similar degrees of inflammation both in the antrum and corpus.
Conclusion:
Endoscopic features such as nodularity of the antral mucosa (p < 0.05) along with histological findings as lymphoid follicles (p < 0.05) are suggestive of H. pylori infection. However, the concordance between the endoscopic and histological diagnosis is still far from perfect (Cohen's k coefficient = 0.42), maintaining the need for an invasive approach in children.


Related Concept Videos
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
 01:17
Gastritis-II: Pathophysiology
In acute gastritis, the gastric mucosa becomes swollen and red and undergoes superficial erosion. Superficial ulceration may lead to bleeding.
In chronic gastritis, persistent or repeated insults lead to chronic inflammatory changes and, eventually, thinning or atrophy of the gastric tissue.
Gastritis can stem from various causes, each...
 01:22
Pathophysiology of Peptic Ulcer Disease: Injurious Factors
In the antrum region, G cells secrete the gastrin hormone that binds to gastrin-cholecystokinin-B (CCK2) receptors on parietal and enterochromaffin-like (ECL) cells in the fundic glands. Simultaneously, the vagus nerve releases acetylcholine, which binds...
 01:16
Treating Helicobacter pylori in Peptic Ulcers: Antimicrobial Therapy
 01:30
Peptic Ulcer Disease I: Introduction
An acute ulcer, marked by superficial erosion and minimal inflammation, swiftly resolves upon identifying and addressing the underlying cause. In contrast, a chronic ulcer persists, potentially eroding through the muscular wall and forming fibrous tissue.
Peptic ulcers can also be...
 01:26
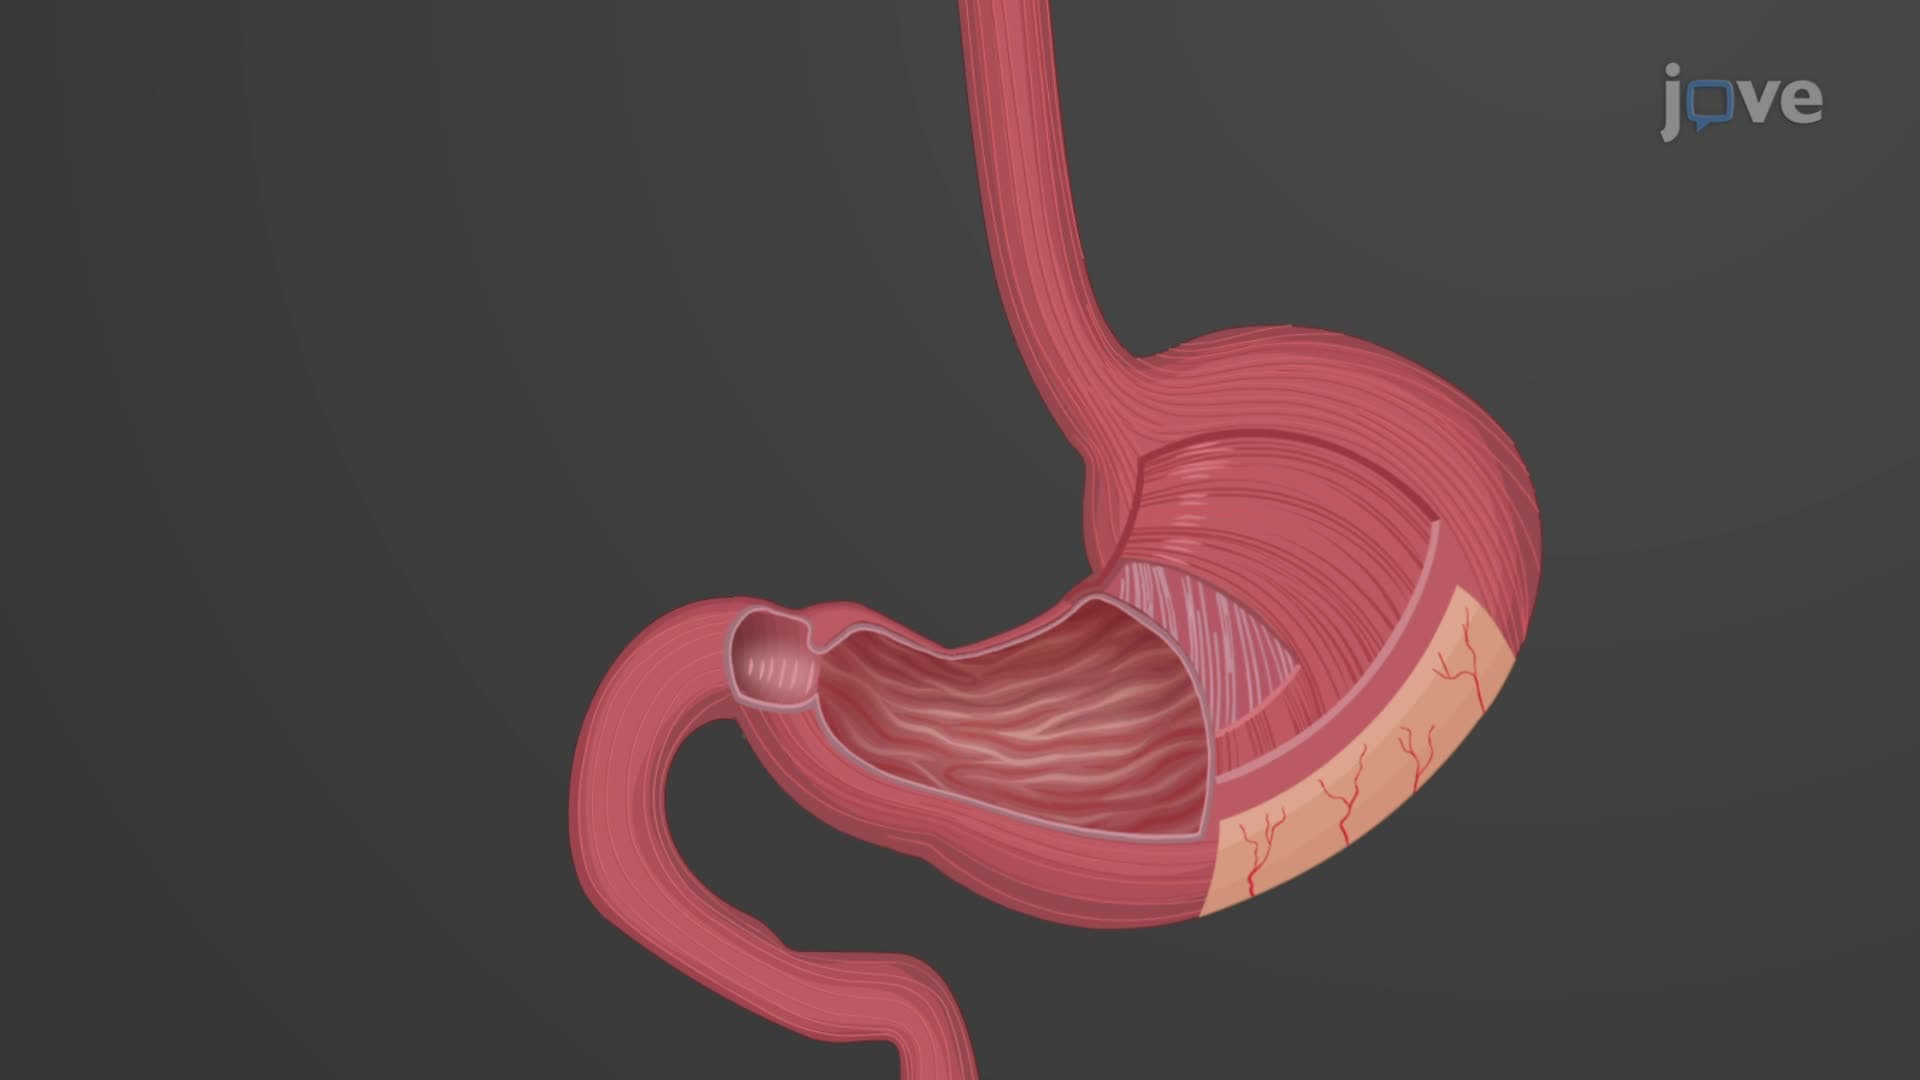
Stomach Histology