Related Experiment Video
Updated: Dec 26, 2025
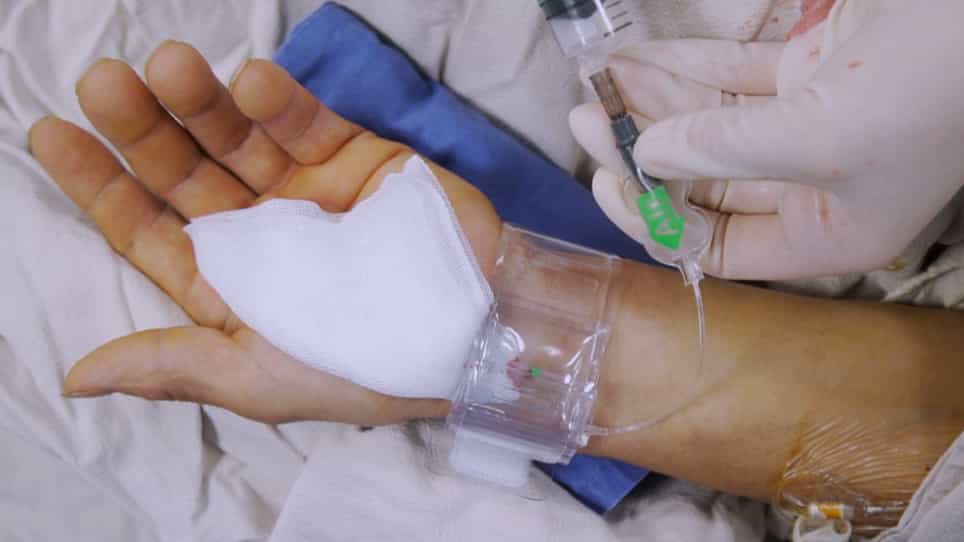
Transradial Access Chemoembolization for Hepatocellular Carcinoma Patients
Published on: September 20, 2020
Transradial vs. Transfemoral Percutaneous Coronary Intervention in Patients With or Without High Bleeding Risk
Ko Yamamoto1, Masahiro Natsuaki2, Takeshi Morimoto3
1Department of Cardiovascular Medicine, Kyoto University Graduate School of Medicine.

Insights
Transradial percutaneous coronary intervention (PCI) significantly reduces bleeding and mortality in high bleeding risk (HBR) patients. Benefits were not observed in non-HBR patients, suggesting tailored approaches for PCI access site selection.
Area of Science:
- Cardiology
- Interventional Cardiology
- Vascular Access
Background:
- Transradial approach (TRA) is linked to fewer bleeding complications and lower mortality post-percutaneous coronary intervention (PCI).
- Clinical benefits of TRA versus transfemoral PCI (TFA) in high bleeding risk (HBR) and non-HBR patients remain unclear.
Purpose of the Study:
- To investigate whether the clinical advantages of TRA over TFA in PCI differ between HBR and non-HBR patient groups.
- To compare the incidence of major bleeding and all-cause mortality between radial and femoral access sites stratified by bleeding risk.
Main Methods:
- Retrospective analysis of 6,828 patients undergoing first PCI from the CREDO-Kyoto Registry Cohort-2.
- Patients were stratified into HBR and non-HBR groups based on Academic Research Consortium criteria.
- Outcomes (major bleeding, all-cause death) at 30 days were compared between radial and femoral access within each risk group.
Main Results:
- In HBR patients, TRA was associated with significantly lower 30-day major bleeding (1.9% vs. 4.7%) and all-cause death (0.3% vs. 0.9%) compared to TFA.
- In non-HBR patients, no significant differences in 30-day major bleeding (0.5% vs. 1.0%) or all-cause death (0.1% vs. 0.1%) were observed between TRA and TFA.
- Adjusted analyses confirmed these findings, showing a reduced risk for major bleeding and mortality with TRA in HBR patients.
Conclusions:
- Transradial PCI demonstrates a reduced risk of 30-day major bleeding and mortality compared to transfemoral PCI specifically in patients with high bleeding risk.
- The clinical benefits of transradial PCI regarding bleeding and mortality were not evident in the non-high bleeding risk patient population.
Background:
The transradial approach is reportedly associated with reduced bleeding complications and mortality after percutaneous coronary intervention (PCI). It is unknown whether the clinical benefits of transradial vs. transfemoral PCI differ between high bleeding risk (HBR) and non-HBR patients.
Methods And Results:
After excluding patients with acute myocardial infarction, dialysis, and a transbrachial approach from the 13,087 patients undergoing first PCI in the CREDO-Kyoto Registry Cohort-2, 6,828 patients were eligible for this study. Patients were divided into 2 groups according to bleeding risk based on Academic Research Consortium HBR criteria, and then divided into a further 2 groups according to access site, radial or femoral: HBR-radial, n=1,054 (38.3%); HBR-femoral, n=1,699 (61.7%); non-HBR-radial, n=1,682 (41.3%); and non-HBR-femoral, n=2,393 (58.7%). In the HBR group, the 30-day incidence and adjusted risk for major bleeding (1.9% vs. 4.7% [P<0.001]; adjusted hazard ratio [aHR] 0.44, 95% confidence interval [CI] 0.26-0.71 [P<0.001]) and all-cause death (0.3% vs. 0.9% [P=0.04]; aHR 0.30, 95% CI 0.07-0.93 [P=0.04]) were significantly lower in the radial than femoral group. There were no significant differences in the 30-day incidence and adjusted risk for major bleeding (0.5% vs. 1.0% [P=0.09]; aHR 0.68, 95% CI 0.30-1.45 [P=0.33]) or all-cause death (0.1% vs. 0.1% [P=0.96]; aHR 1.51, 95% CI 0.19-9.54 [P=0.67]) between the radial and femoral approaches in the non-HBR group.
Conclusions:
Compared with transfemoral PCI, transradial PCI was associated with lower risk for 30-day major bleeding and mortality in HBR but not non-HBR patients.


