Related Experiment Video
Updated: Dec 25, 2025


Isolation, Characterization, And High Throughput Extracellular Flux Analysis of Mouse Primary Renal Tubular Epithelial Cells
Published on: June 20, 2018
Incomplete distal renal tubular acidosis in children
Marta Alonso-Varela1,2, Helena Gil-Peña3, Fernando Santos2,3
1Hospital Universitario Cruces, Baracaldo, Vizcaya, Spain.

Insights
Incomplete distal renal tubular acidosis (iDRTA) in children presents differently than in adults. Further research is needed to characterize iDRTA
Area of Science:
- Pediatric Nephrology
- Renal Tubular Acidosis Research
- Urine Acidification Studies
Background:
- Incomplete distal renal tubular acidosis (iDRTA) is diagnosed in patients unable to acidify urine despite lacking overt metabolic acidosis.
- iDRTA is more commonly identified in adults with autoimmune diseases, kidney stones, or bone density loss.
- Limited data exists on iDRTA in pediatric populations, often associated with rickets, urogenital abnormalities, or growth failure.
Purpose of the Study:
- To describe the characteristics of incomplete distal renal tubular acidosis (iDRTA) in pediatric patients.
- To review diagnostic methods for urinary acidification.
- To discuss pathophysiological mechanisms and clinical findings of iDRTA in children.
Main Methods:
- Systematic review of English-language publications from a PubMed search using the keyword 'incomplete distal renal tubular acidosis'.
- Analysis of 161 retrieved entries.
- Revision of tests used to assess urinary acidification.
Main Results:
- iDRTA has been reported in a small number of pediatric patients, often linked to conditions like rickets and congenital kidney abnormalities.
- The presentation and clinical features of iDRTA in children appear distinct from those observed in adults.
- Pathophysiological mechanisms and biochemical findings in pediatric iDRTA require further elucidation.
Conclusions:
- The clinical and biochemical profile of iDRTA in children is not well-characterized.
- Pediatric iDRTA presentation differs significantly from adult cases.
- Investigating iDRTA in specific pediatric groups (e.g., gene mutation carriers, hypocitraturia/hypercalciuria) may offer insights into its pathophysiology and natural history.
Aim:
To describe incomplete distal renal tubular acidosis (iDRTA) in paediatric patients, a term used for the diagnosis of patients who do not develop spontaneous overt metabolic acidosis but are unable to acidify the urine in response to an ammonium chloride load.
Methods:
Tests used to explore urinary acidification were revised. In addition, publications in English extracted from 161 entries yielded by a PubMed database search, using 'incomplete distal renal tubular acidosis' as keyword, were reviewed.
Results:
Incomplete distal renal tubular acidosis has mostly been identified in adults with autoimmune diseases, nephrolithiasis, nephrocalcinosis and/or osteopenia. iDRTA has been reported in few paediatric patients with rickets, congenital abnormalities of kidney and urological tract and/or growth failure. The pathophysiological mechanisms potentially responsible for the defect of urinary acidification are discussed as well as the clinical and biochemical findings of iDRTA described in children.
Conclusion:
The presentation of iDRTA in children differs from adults. The clinical and biochemical features of iDRTA are not well characterised in paediatric patients. The detection of iDRTA in groups of population such as heterozygous carriers of primary DRTA gene mutations and children with hypocitraturia or hypercalciuria might be of clinical interest to better know the pathophysiology and natural history of iDRTA.
More Related Videos
 08:46
Implementing Patch Clamp and Live Fluorescence Microscopy to Monitor Functional Properties of Freshly Isolated PKD Epithelium
Published on: September 1, 2015
 07:35
Use of Ultra-high Field MRI in Small Rodent Models of Polycystic Kidney Disease for In Vivo Phenotyping and Drug Monitoring
Published on: June 23, 2015
Related Concept Videos
 01:24
Renal Tubule and Collecting Duct
Proximal Convoluted Tubule (PCT):
The PCT is the initial segment of the renal tubule, extending from the Bowman's capsule that encloses the glomerulus. Its convoluted structure and microvilli-lined cells increase the surface area for reabsorption. The PCT reabsorbs glucose, amino acids, sodium, and water from the filtrate, ensuring essential...
 01:29
Renal Regulation of Acid-Base Balance
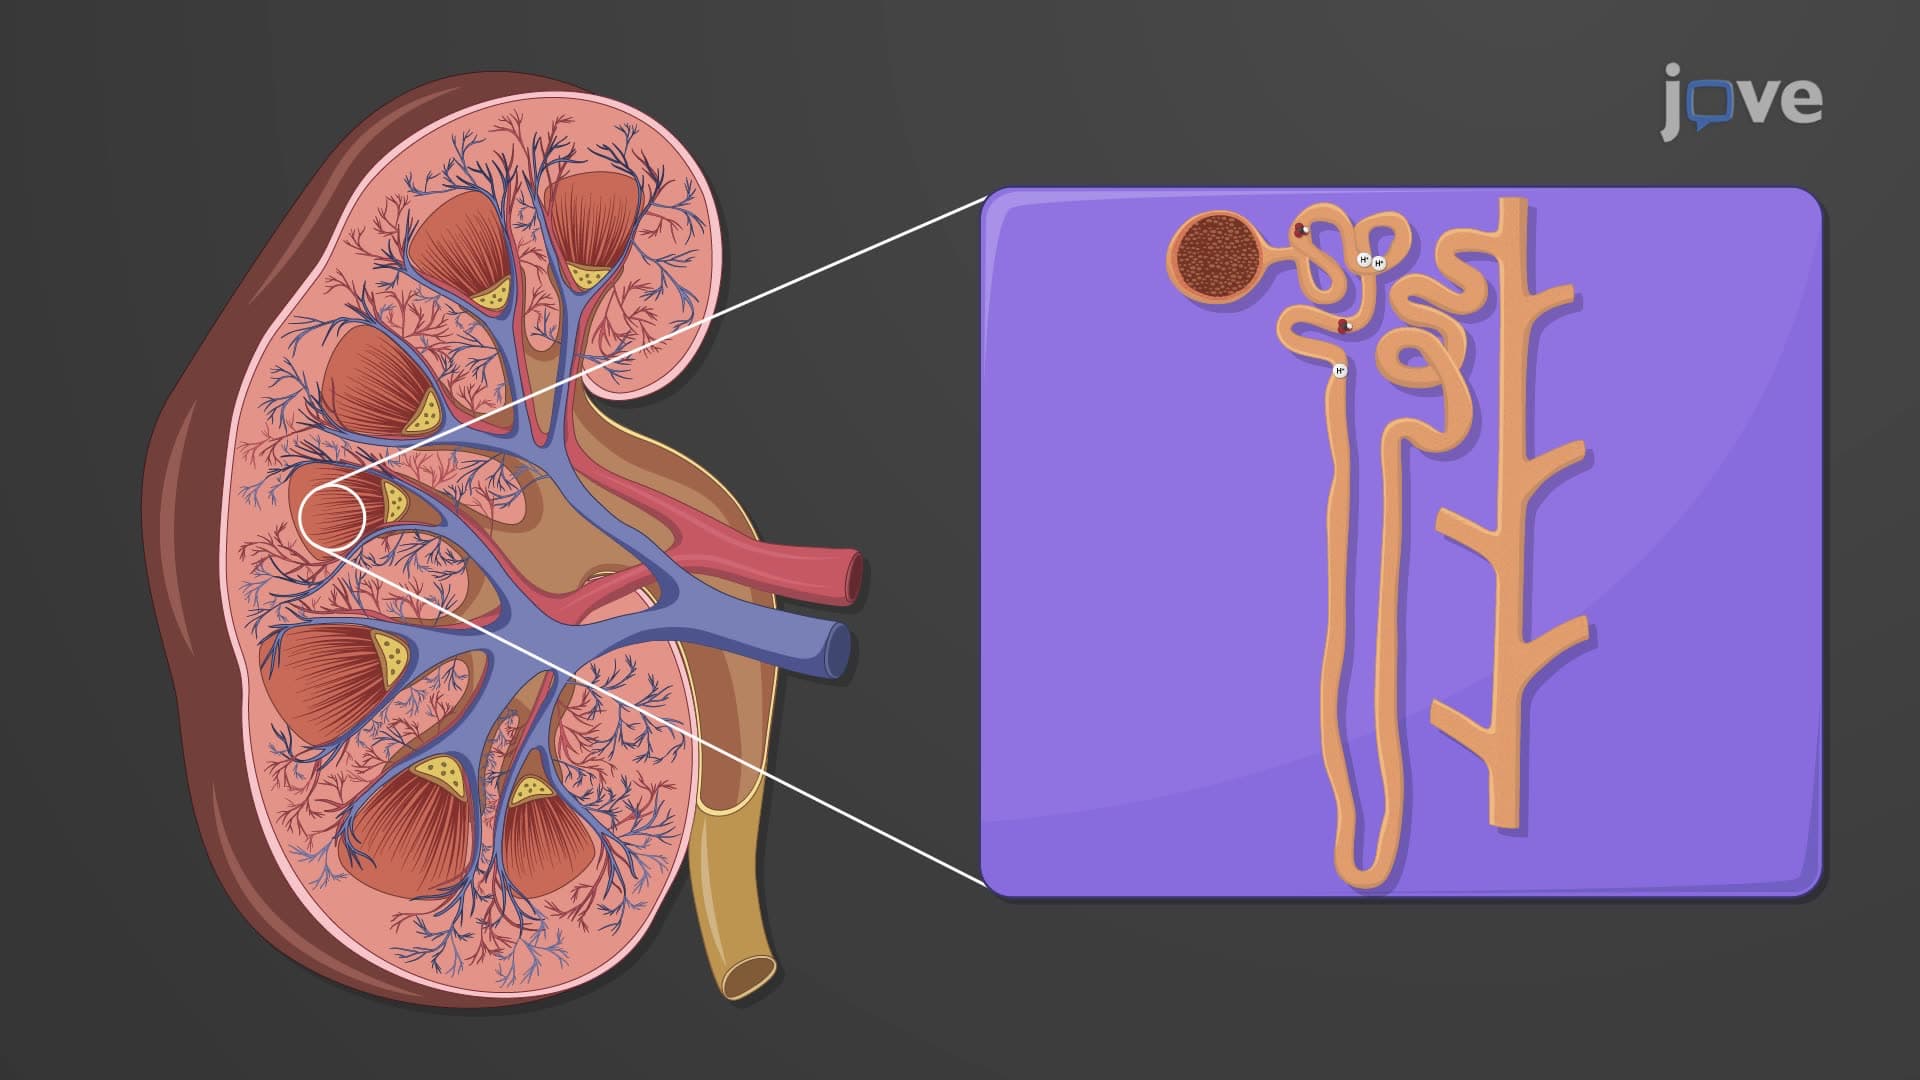
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
 01:29
Acute Kidney Injury III: Clinical Manifestations
 01:22
Acute Kidney Injury I: Introduction
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:29
Acute Kidney Injury II: Pathophysiology