Related Experiment Video
Updated: Dec 25, 2025


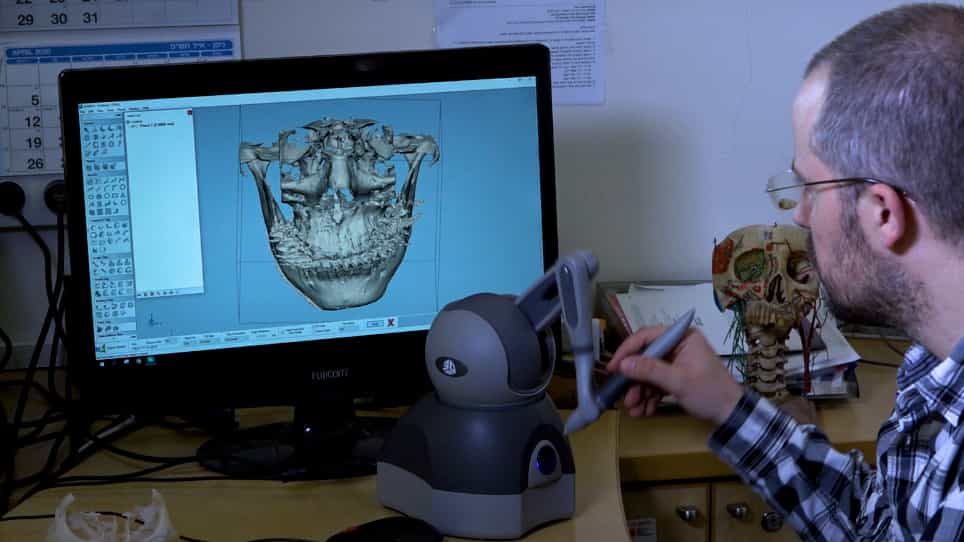
Three-Dimensional Reconstruction of Orbital Fractures
Published on: May 16, 2025
Pediatric Frontal Bone and Sinus Fractures: Cause, Characteristics, and a Treatment Algorithm
Joseph Lopez1, Kevin Pineault1, Tejus Pradeep1
1From the Department of Plastic and Reconstructive Surgery, Johns Hopkins Hospital; the Rush Medical College of Rush University; and the R Adams Cowley Shock Trauma Center, University of Maryland Medical Center.

Background:
The purpose of this study was to assess the incidence, cause, characteristics, presentation, and management of pediatric frontal bone fractures.
Methods:
A retrospective cohort review was performed on all patients younger than 15 years with frontal fractures that presented to a single institution from 1998 to 2010. Charts and computed tomographic images were reviewed, and frontal bone fractures were classified into three types based on anatomical fracture characteristics. Fracture cause, patient demographics, management, concomitant injuries, and complications were recorded. Primary outcomes were defined by fracture type and predictors of operative management and length of stay.
Results:
A total of 174 patients with frontal bone fractures met the authors' inclusion criteria. The mean age of the patient sample was 7.19 ± 4.27 years. Among these patients, 52, 47, and 75 patients were classified as having type I, II, and III fractures, respectively. A total of 14, 9, and 24 patients with type I, II, and III fractures underwent operative management, respectively. All children with evidence of nasofrontal outflow tract involvement and obstruction underwent cranialization (n = 11).
Conclusions:
The authors recommend that type I fractures be managed according to the usual neurosurgical guidelines. Type II fractures can be managed operatively according to the usual pediatric orbital roof and frontal sinus fracture indications (e.g., significantly displaced posterior table fractures with associated neurologic indications). Lastly, type III fractures can be managed operatively as for type I and II indications and for evidence of nasofrontal outflow tract involvement. The authors recommend cranialization in children with nasofrontal outflow tract involvement.
Clinical Question/Level Of Evidence:
Risk, II.

Related Concept Videos
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...
 01:27
Cranial Bones: Lateral View
The temporal bone forms the lower lateral side of the skull. The temporal bone is subdivided into several regions. The flattened upper portion is the squamous portion of the temporal bone. Below this area and projecting anteriorly is the zygomatic process of the temporal bone, which forms the posterior portion of the zygomatic arch. Posteriorly is the mastoid portion of the temporal bone. Projecting...
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History: