Related Experiment Video
Updated: Dec 25, 2025
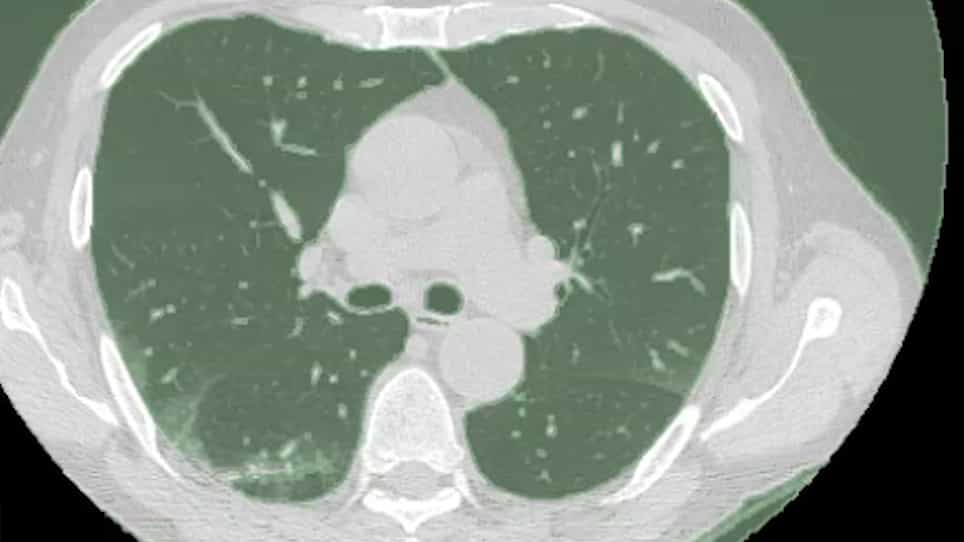

Lung CT Segmentation to Identify Consolidations and Ground Glass Areas for Quantitative Assesment of SARS-CoV Pneumonia
Published on: December 19, 2020
Quantitative CT Evidence of Airway Inflammation in WTC Workers and Volunteers with Low FVC Spirometric Pattern
Jonathan Weber1, Anthony P Reeves2, John T Doucette3
1Department of Research and Education, Saint Francis Hospital, Roslyn, NY, USA.

Background:
The most common abnormal spirometric pattern reported in WTC worker and volunteer cohorts has consistently been that of a nonobstructive reduced forced vital capacity (low FVC). Low FVC is associated with obesity, which is highly prevalent in these cohorts. We used quantitative CT (QCT) to investigate proximal and distal airway inflammation and emphysema in participants with stable low FVC pattern.
Methods:
We selected study participants with at least two available longitudinal surveillance spirometries, and a chest CT with QCT measurements of proximal airway inflammation (wall area percent, WAP), end-expiratory air trapping, suggestive of distal airway obstruction (expiratory to inspiratory mean lung attenuation ratio, MLAEI), and emphysema (percentage of lung volume with attenuation below - 950 HU, LAV%). The comparison groups in multinomial logistic regression models were participants with consistently normal spirometries, and participants with stable fixed obstruction (COPD).
Results:
Compared to normal spirometry participants, and after adjusting for age, sex, race/ethnicity, BMI, smoking, and early arrival at the WTC disaster site, low FVC participants had higher WAP (ORadj 1.24, 95% CI 1.06, 1.45, per 5% unit), suggestive of proximal airway inflammation, but did not differ in MLAEI, or LAV%. COPD participants did not differ in WAP with the low FVC ones and were more likely to have higher MLAEI or LAV% than the other two subgroups.
Discussion:
WTC workers with spirometric low FVC have higher QCT-measured WAP compared to those with normal spirometries, but did not differ in distal airway and emphysema measurements, independently of obesity, smoking, and other covariates.
Related Concept Videos
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:25
Pulmonary Function Tests
Pulmonary Function Tests are crucial diagnostic tools for assessing respiratory function, particularly in patients with chronic respiratory disorders. They comprehensively evaluate lung volumes, ventilatory function, breathing mechanics, diffusion, and gas exchange. These tests help diagnose pulmonary diseases and play a significant role in monitoring disease progression, evaluating disability, and assessing response to therapy.
PFTs involve using a spirometer, a...
 01:30
Radiological Investigation II: MRI and Ventilation Perfusion Scan
Magnetic Resonance Imaging (MRI) and Ventilation Perfusion Scans are two radiological investigations that offer detailed diagnostic images of the body, particularly lung structures.
MRI
MRI uses magnetic fields and radiofrequency signals to distinguish between normal and abnormal tissues. This technology provides a more detailed diagnostic image than CT scans, enabling it to characterize pulmonary nodules, stage bronchogenic carcinoma, and evaluate inflammatory activity in...
 01:24
Physical Assessment of the Respiratory Tract II: Palpation
Thoracic Palpation
Thoracic palpation detects tenderness, masses, lesions, respiratory excursions, and vocal fremitus. The nurse assesses...
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction