Related Experiment Video
Updated: Dec 25, 2025
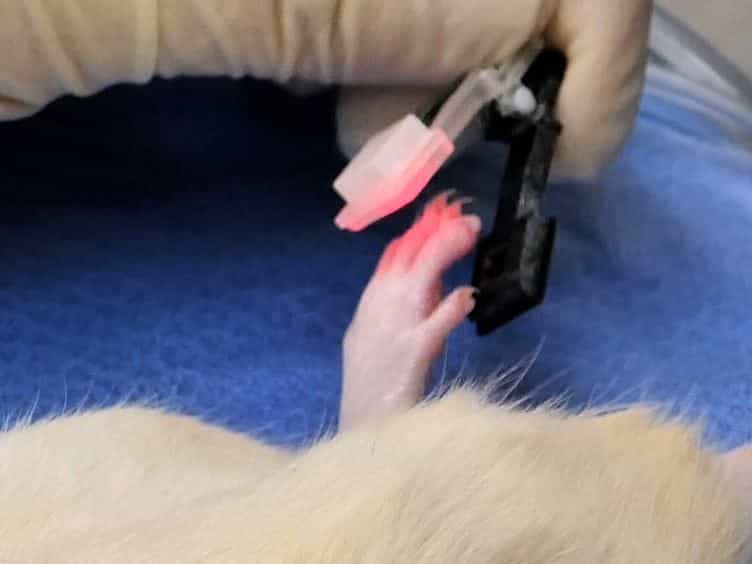

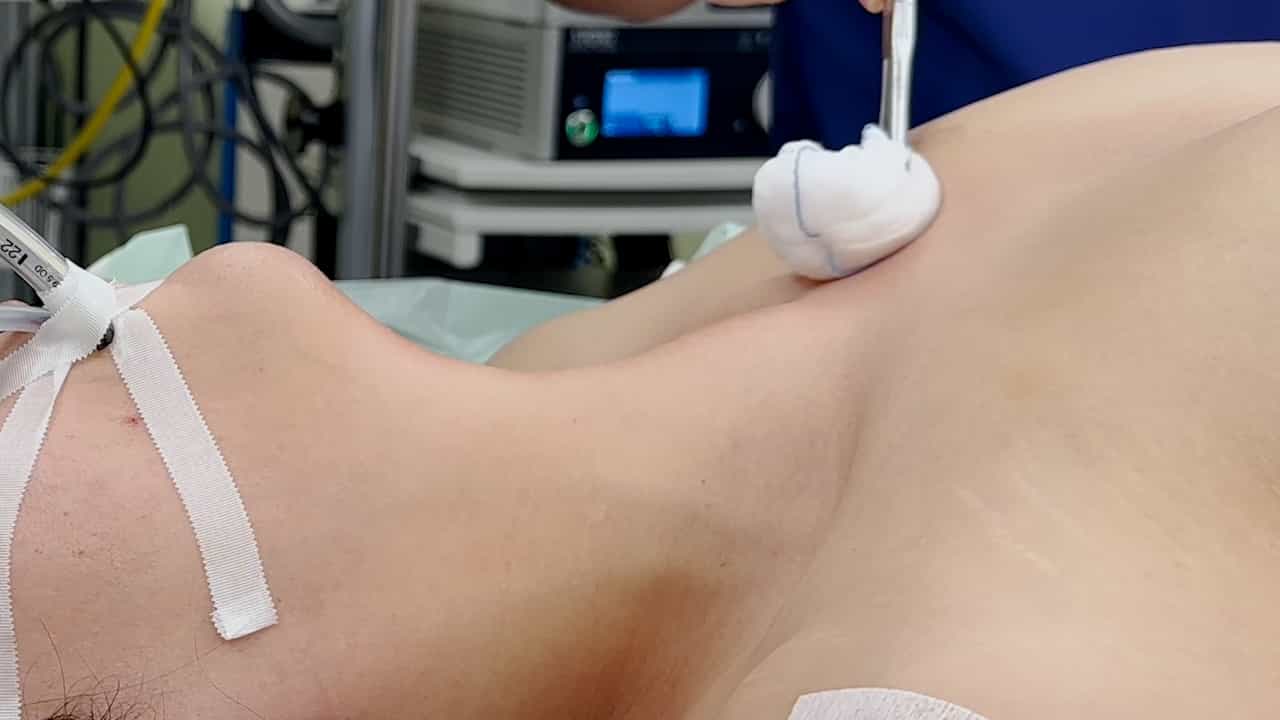
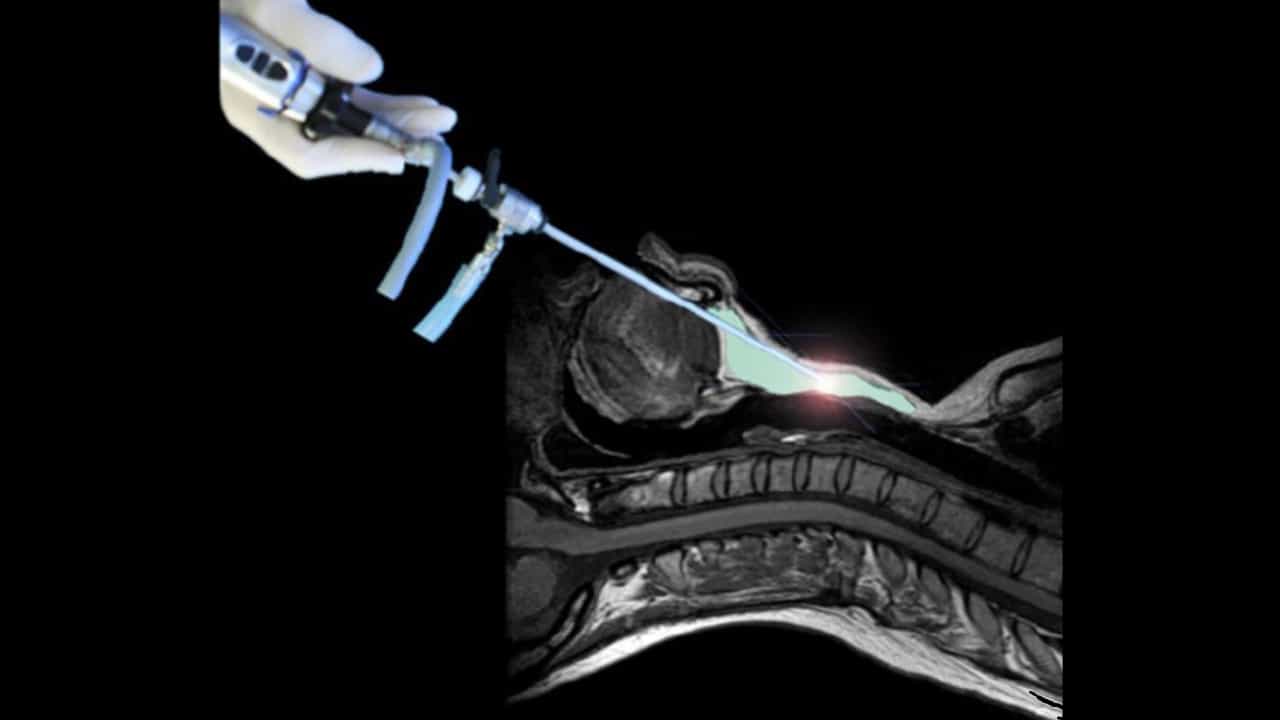
Complete Thymectomy in Adult Rats with Non-invasive Endotracheal Intubation
Published on: December 29, 2014
A national analysis of open versus minimally invasive thymectomy for stage I to III thymoma
Chi-Fu Jeffrey Yang1, Jacob Hurd2, Shivani A Shah3
1Stanford University, Stanford, Calif.

Objective:
The oncologic efficacy of minimally invasive thymectomy for thymoma is not well characterized. We compared short-term outcomes and overall survival between open and minimally invasive (video-assisted thoracoscopic and robotic) approaches using the National Cancer Data Base.
Methods:
Perioperative outcomes and survival of patients who underwent open versus minimally invasive thymectomy for clinical stage I to III thymoma from 2010 to 2014 in the National Cancer Data Base were evaluated using multivariable Cox proportional hazards modeling and propensity score-matched analysis. Predictors of minimally invasive use were evaluated using multivariable logistic regression. Outcomes of surgical approach were evaluated using an intent-to-treat analysis.
Results:
Of the 1223 thymectomies that were evaluated, 317 (26%) were performed minimally invasively (141 video-assisted thoracoscopic and 176 robotic). The minimally invasive group had a shorter median length of stay when compared with the open group (3 [2-4] days vs 4 [3-6] days, P < .001). In a propensity score-matched analysis of 185 open and 185 minimally invasive (video-assisted thoracoscopic + robotic) thymectomy, the minimally invasive group continued to have a shorter median length of stay (3 vs 4 days, P < .01) but did not have significant differences in margin positivity (P = .84), 30-day readmission (P = .28), 30-day mortality (P = .60), and 5-year survival (89.4% vs 81.6%, P = .20) when compared with the open group.
Conclusions:
In this national analysis, minimally invasive thymectomy was associated with shorter length of stay and was not associated with increased margin positivity, perioperative mortality, 30-day readmission rate, or reduced overall survival when compared with open thymectomy.