Related Experiment Video
Updated: Dec 25, 2025
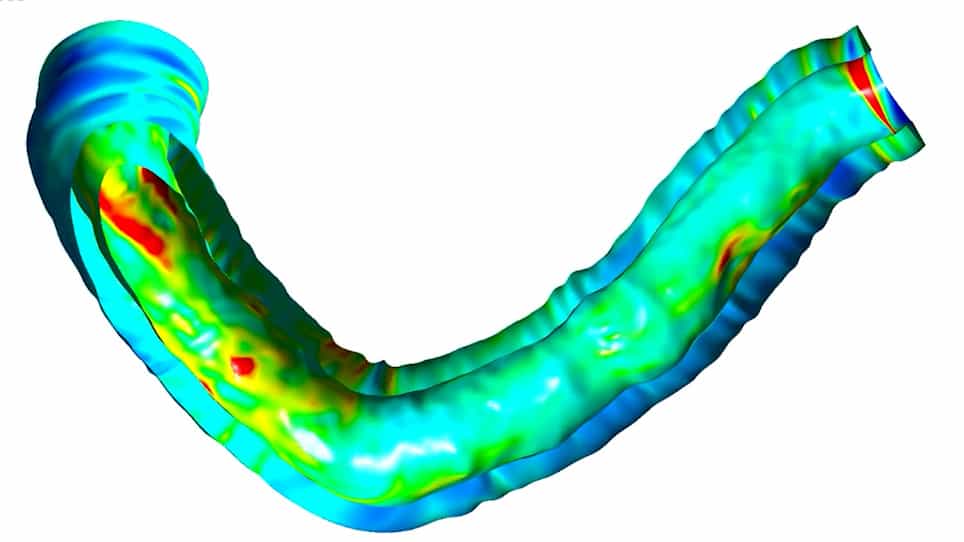

Optical Coherence Tomography Based Biomechanical Fluid-Structure Interaction Analysis of Coronary Atherosclerosis Progression
Published on: January 15, 2022
Coronary Artery Disease: From Mechanism to Clinical Practice
Chunli Shao1, Jingjia Wang1, Jian Tian1
1Department of Cardiology, Fu Wai Hospital, National Center for Cardiovascular Diseases, Chinese Academy of Medical Sciences and Peking Union Medical College, 167 Beilishi Road, Beijing, 100037, China.

Insights
Coronary artery disease (CAD) and atherosclerosis are leading causes of death, influenced by risk factors like hypertension and lifestyle. Understanding angina pectoris and myocardial infarction (MI) is crucial for patient outcomes.
Area of Science:
- Cardiovascular Medicine
- Atherosclerosis Research
- Public Health
Background:
- Coronary artery disease (CAD), primarily due to atherosclerosis, is a major cause of mortality in developed nations.
- While acute myocardial infarction (MI) mortality declined significantly from the 1990s to 2000s, CAD incidence remains linked to age, gender, and socioeconomic factors.
- Atherosclerosis involves complex processes including lipid disturbances, inflammation, thrombosis, and genetic predisposition, with numerous modifiable and non-modifiable risk factors.
Purpose of the Study:
- To review the multifactorial nature of coronary artery disease (CAD) and atherosclerosis.
- To discuss the clinical manifestations of angina pectoris and its classification.
- To highlight the diagnostic advancements and complications associated with acute myocardial infarction (MI).
Main Methods:
- Literature review of coronary artery disease (CAD) and atherosclerosis.
- Analysis of risk factors, including hypertension, dyslipidemia, diabetes, and lifestyle choices.
- Examination of diagnostic criteria and complications of myocardial infarction (MI).
Main Results:
- CAD is a complex disease with numerous interconnected pathological processes and risk factors.
- Angina pectoris, a symptom of myocardial ischemia, is characterized by chest pain and is graded using systems like the Canadian Cardiovascular Society (CCS) classification.
- New diagnostic criteria for MI have become necessary due to advancements in biomarkers and imaging techniques, with various potential complications identified.
Conclusions:
- Effective management of CAD requires addressing its diverse risk factors and understanding its underlying pathophysiology.
- Accurate diagnosis and classification of angina pectoris are essential for guiding treatment.
- Recognizing the complications of acute myocardial infarction (MI) is critical for improving patient prognosis and outcomes.
Abstract:
In most developed countries, coronary artery disease (CAD), mostly caused by atherosclerosis of coronary arteries, is one of the primary causes of death. From 1990s to 2000s, mortality caused by acute MI declined up to 50%. The incidence of CAD is related with age, gender, economic, etc. Atherosclerosis contains some highly correlative processes such as lipid disturbances, thrombosis, inflammation, vascular smooth cell activation, remodeling, platelet activation, endothelial dysfunction, oxidative stress, altered matrix metabolism, and genetic factors. Risk factors of CAD exist among many individuals of the general population, which includes hypertension, lipids and lipoproteins metabolism disturbances, diabetes mellitus, chronic kidney disease, age, genders, lifestyle, cigarette smoking, diet, obesity, and family history. Angina pectoris is caused by myocardial ischemia in the main expression of pain in the chest or adjoining area, which is usually a result of exertion and related to myocardial function disorder. Typical angina pectoris would last for minutes with gradual exacerbation. Rest, sit, or stop walking are the usual preference for patients with angina, and reaching the maximum intensity in seconds is uncommon. Rest or nitroglycerin usage can relieve typical angina pectoris within minutes. So far, a widely accepted angina pectoris severity grading system included CCS (Canadian Cardiovascular Society) classification, Califf score, and Goldman scale. Patients with ST-segment elevated myocardial infarction (STEMI) may have different symptoms and signs of both severe angina pectoris and various complications. The combination of rising usage of sensitive MI biomarkers and precise imaging techniques, including electrocardiograph (ECG), computed tomography, and cardiac magnetic resonance imaging, made the new MI criteria necessary. Complications of acute myocardial infarction include left ventricular dysfunction, cardiogenic shock, structural complications, arrhythmia, recurrent chest discomfort, recurrent ischemia and infarction, pericardial effusion, pericarditis, post-myocardial infarction syndrome, venous thrombosis pulmonary embolism, left ventricular aneurysm, left ventricular thrombus, and arterial embolism.
More Related Videos


Related Concept Videos
 01:26
Coronary Artery Disease II: Pathophysiology
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations
 01:30
Coronary Artery Disease III: Clinical Manifestations
 01:30
Coronary Artery Disease I: Introduction
 01:27
Coronary Artery Disease V: Interprofessional Care
 01:27
Atherosclerosis II: Clinical Manifestations and Diagnostic Tests