Related Experiment Video
Updated: Dec 25, 2025

Noninvasive Determination of Vortex Formation Time Using Transesophageal Echocardiography During Cardiac Surgery
Published on: November 28, 2018
Adverse cardiac events after vascular surgery are prevalent despite negative results of preoperative stress testing
Jesse A Columbo1, J Aaron Barnes1, Douglas W Jones2
1Section of Vascular Surgery, Geisel School of Medicine at Dartmouth, Hanover, NH.

Insights
A negative cardiac stress test before vascular surgery does not eliminate cardiac event risk, especially for major procedures. Patients undergoing certain vascular surgeries with negative stress tests had a higher risk of postoperative cardiac events or death.
Area of Science:
- Cardiovascular Medicine
- Vascular Surgery
- Perioperative Medicine
Background:
- Cardiac risk assessment is vital before vascular surgery.
- The benefit of a negative cardiac stress test in predicting outcomes is not well-defined.
- Preoperative testing practices for vascular surgery vary significantly.
Purpose of the Study:
- To compare postoperative cardiac event rates in vascular surgery patients with negative stress tests versus those without testing.
- To evaluate the predictive value of negative stress tests in different types of vascular procedures.
- To inform risk stratification and management strategies for patients undergoing vascular interventions.
Main Methods:
- Retrospective review of patients undergoing elective open abdominal aortic aneurysm repair, suprainguinal bypass, EVAR, CEA, or infrainguinal bypass (2003-2017).
- Exclusion of patients with positive stress tests.
- Comparison of outcomes between patients with negative stress tests and those without any stress testing (n=26,910).
Main Results:
- A negative stress test was associated with a 37% increased odds of cardiac events or death after open repair and a 52% increase after suprainguinal bypass.
- For EVAR, CEA, and infrainguinal bypass, negative stress tests showed no significant difference in event rates compared to no testing.
- Significant variation in stress test utilization was observed across different centers and procedure types.
Conclusions:
- Negative preoperative stress test results do not guarantee freedom from postoperative cardiac events in vascular surgery patients.
- The utility of stress testing varies by procedure type, with higher-risk procedures showing a potential increased risk despite negative tests.
- Clinical judgment remains crucial, and a negative stress test should not lead to complacency regarding cardiac risk in major vascular operations.
Objective:
Cardiac risk assessment is a critical component of vascular disease management before surgical intervention. The predictive risk reduction of a negative cardiac stress test result remains poorly defined. The objective of this study was to compare the incidence of postoperative cardiac events among patients with negative stress test results vs those who did not undergo testing.
Methods:
We reviewed all patients who underwent elective open abdominal aortic aneurysm repair, suprainguinal bypass, endovascular aneurysm repair (EVAR), carotid endarterectomy (CEA), and infrainguinal bypass within the Vascular Study Group of New England from 2003 to 2017. We excluded patients with positive stress test results (n = 3312) and studied two mutually exclusive groups: elective surgery patients with a negative stress test result and elective surgery patients with no stress test (total n = 26,910). The primary outcome was a composite of in-hospital postoperative cardiac events (dysrhythmia, heart attack, heart failure) or death.
Results:
A preoperative stress test was obtained in 66.3% of open repairs, 42.8% of suprainguinal bypasses, 37.1% of EVARs, 36.0% of CEAs, and 31.2% of infrainguinal bypasses. The proportion of patients receiving a preoperative stress test varied widely across centers, from 37.1% to 80.0%. The crude odds ratio of in-hospital postoperative cardiac event or death was 1.37 (95% confidence interval [CI], 1.07-1.76) for open repair and 1.52 (CI, 1.13-2.03) for suprainguinal bypass, indicating that patients with negative stress test results before these procedures were 37% and 52% more likely to suffer a postoperative event or die compared with patients selected to proceed directly to surgery without testing. Conversely, the crude odds ratio was 0.92 (CI, 0.66-1.29) for EVAR, 0.92 (CI, 0.70-1.21) for CEA, and 1.13 (CI, 0.90-1.40) for infrainguinal bypass, indicating that patients undergoing these procedures had a similar likelihood of sustaining an event whether they had a negative stress test result or proceeded directly to surgery without a stress test.
Conclusions:
The use of cardiac stress testing before vascular surgery varies widely throughout New England. Whereas patients are often appropriately selected to proceed directly to surgery, a negative preoperative stress test result should not assuage the concern for an adverse outcome as these patients retain a substantial likelihood of cardiac events, especially after large-magnitude procedures.


Related Concept Videos
 01:26
Cardiac Catheterization IV: Nursing Management
 01:28
Cardiomyopathy VII: Pre and Post Operative Nursing Management
 01:22
Aneurysm IV: Nursing Management
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management
 01:28
Cardiac Catheterization I: Pre-Procedure Overview
 01:26
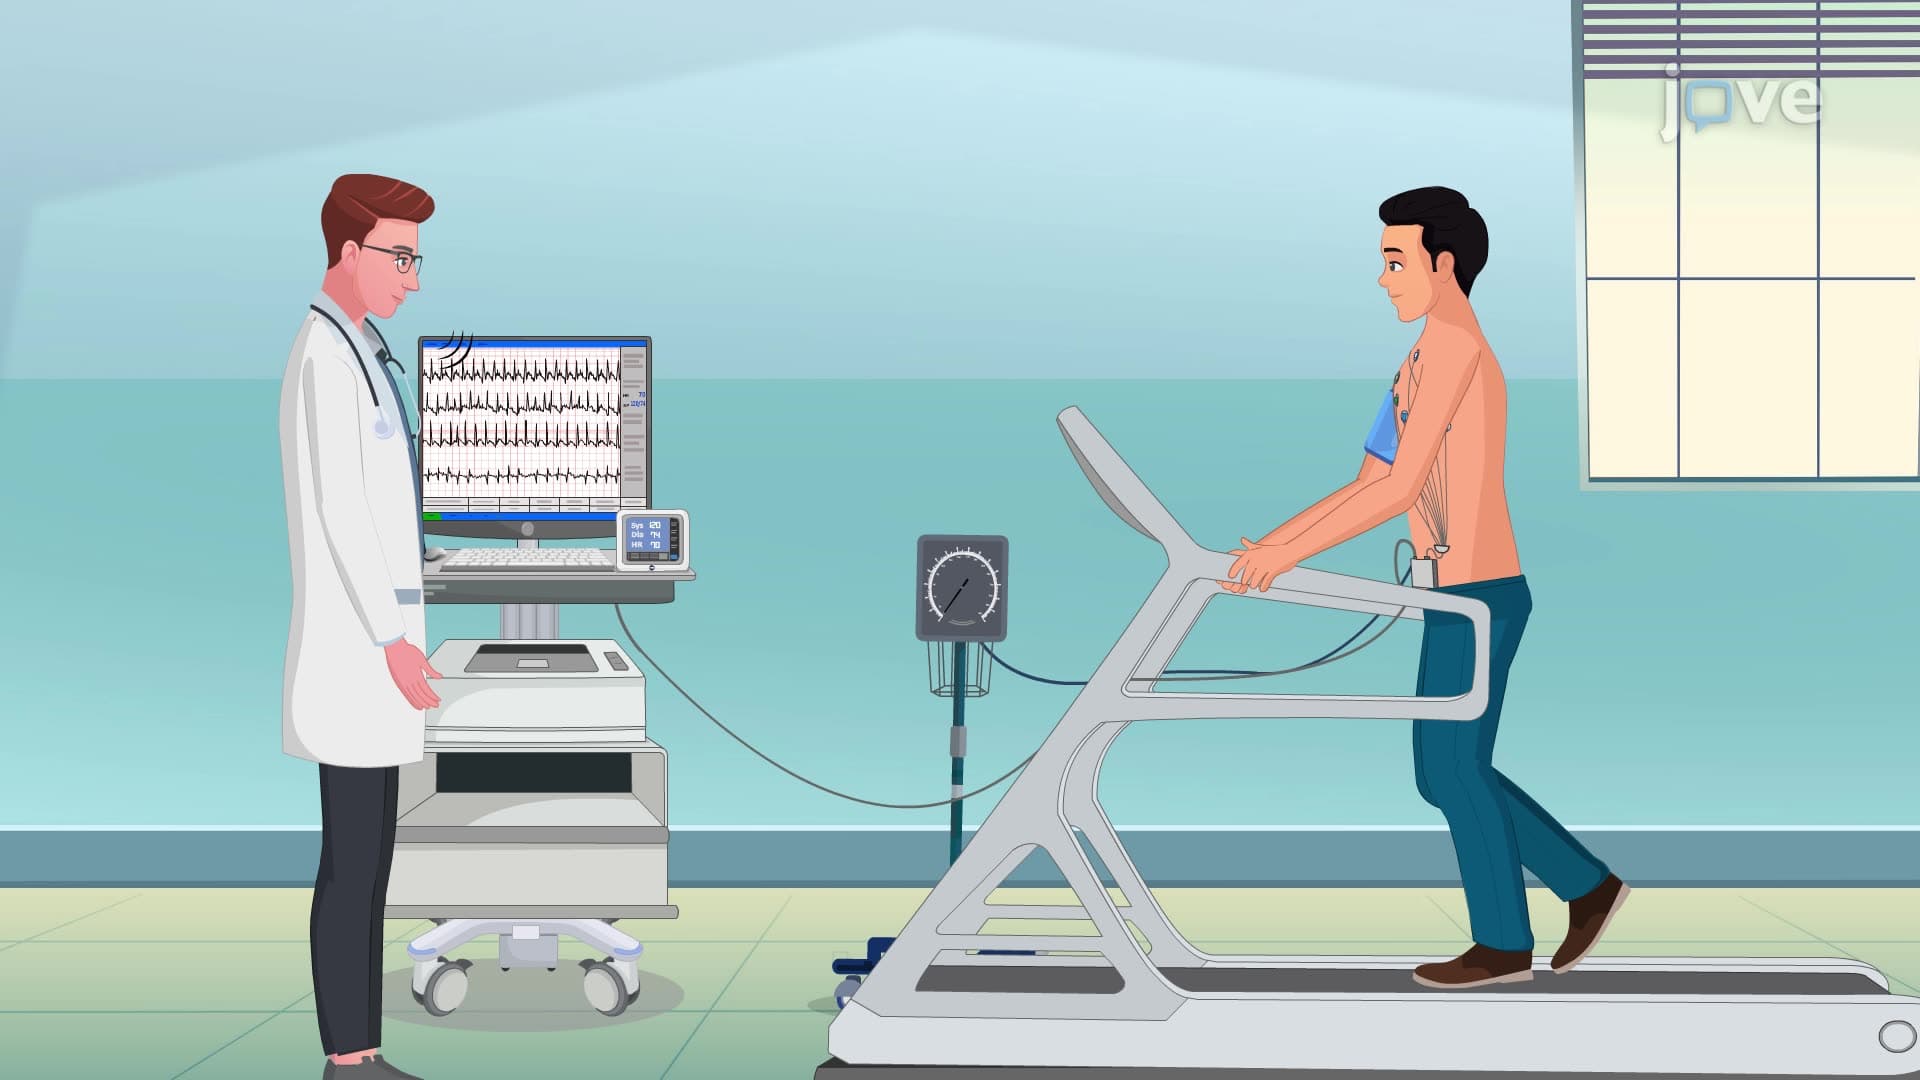
Exercise Stress Test
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes