Related Experiment Video
Updated: Dec 24, 2025

Generation of Hypoparathyroid Rats via Carbon-Nanoparticle-Assisted Parathyroidectomy
Published on: July 14, 2023
Biochemical Characteristics of Bone Mineral Metabolism before and throughout the First Year after Kidney
Lourdes Balcázar-Hernández1, Guadalupe Vargas-Ortega1, Baldomero González-Virla1
1Endocrinology Department, Hospital de Especialidades, Centro Médico Nacional Siglo XXI, Instituto Mexicano del Seguro Social, Cuauhtémoc 330, Colonia Doctores, 06720 México City, Mexico.

Abstract:
Bone mineral metabolism disease, which included persistent hyperparathyroidism, is common after successful kidney transplantation (KT) and is related with negative outcomes in kidney transplant recipients. There is a lack of information about bone mineral metabolism, persistent hyperparathyroidism, and its risk factors in Latin kidney transplant recipients (KTRs). Material and Methods: A retrospective study was conducted in 74 patients aged 18-50 years with evolution of 12 months after KT and estimated glomerular filtration rate (eGFR) >60 ml/min; biochemical data of bone mineral metabolism before and at 1, 3, 6, and 12 months of KT were registered. Results. Age was 33 (IQR 27-37) years; 54% (n = 40) were men. Before KT, all patients had hyperparathyroidism, 40% (n = 30) hypocalcemia, 86% (n = 64) hyperphosphatemia, and 42% (n = 31) hyperphosphatasemia. After KT, an increase of calcium and a diminution of PTH, phosphorus, and alkaline phosphatase were corroborated (p=0.001). All patients had hypovitaminosis D (deficiency: 91% (n = 67); insufficiency: 9% (n = 7)); 40% (n = 30) had persistent hyperparathyroidism at 12 months. Hyperphosphatasemia before KT (OR = 4.17 (95% CI: 1.21-14.44); p=0.04), hyperparathyroidism at 6 months (OR = 1.84 (95% CI; 1.67-2.06); p=0.02), hypovitaminosis D at 6 months (OR = 3.94 (95% CI: 1.86-17.9); p=0.01), and hyperphosphatasemia at 6 months (OR = 1.47 (95% CI: 1.07-2.86); p=0.03) were risk factors for persistent hyperparathyroidism at 12 months after KT. Conclusion. Persistent hyperparathyroidism at 6 months, hypovitaminosis D, and hyperphosphatasemia are risk factors for persistent hyperparathyroidism at 1 year of KT in Latin population.


Related Concept Videos
 01:21
Skeleton and Calcium Homeostasis
 01:40
Bone Remodeling
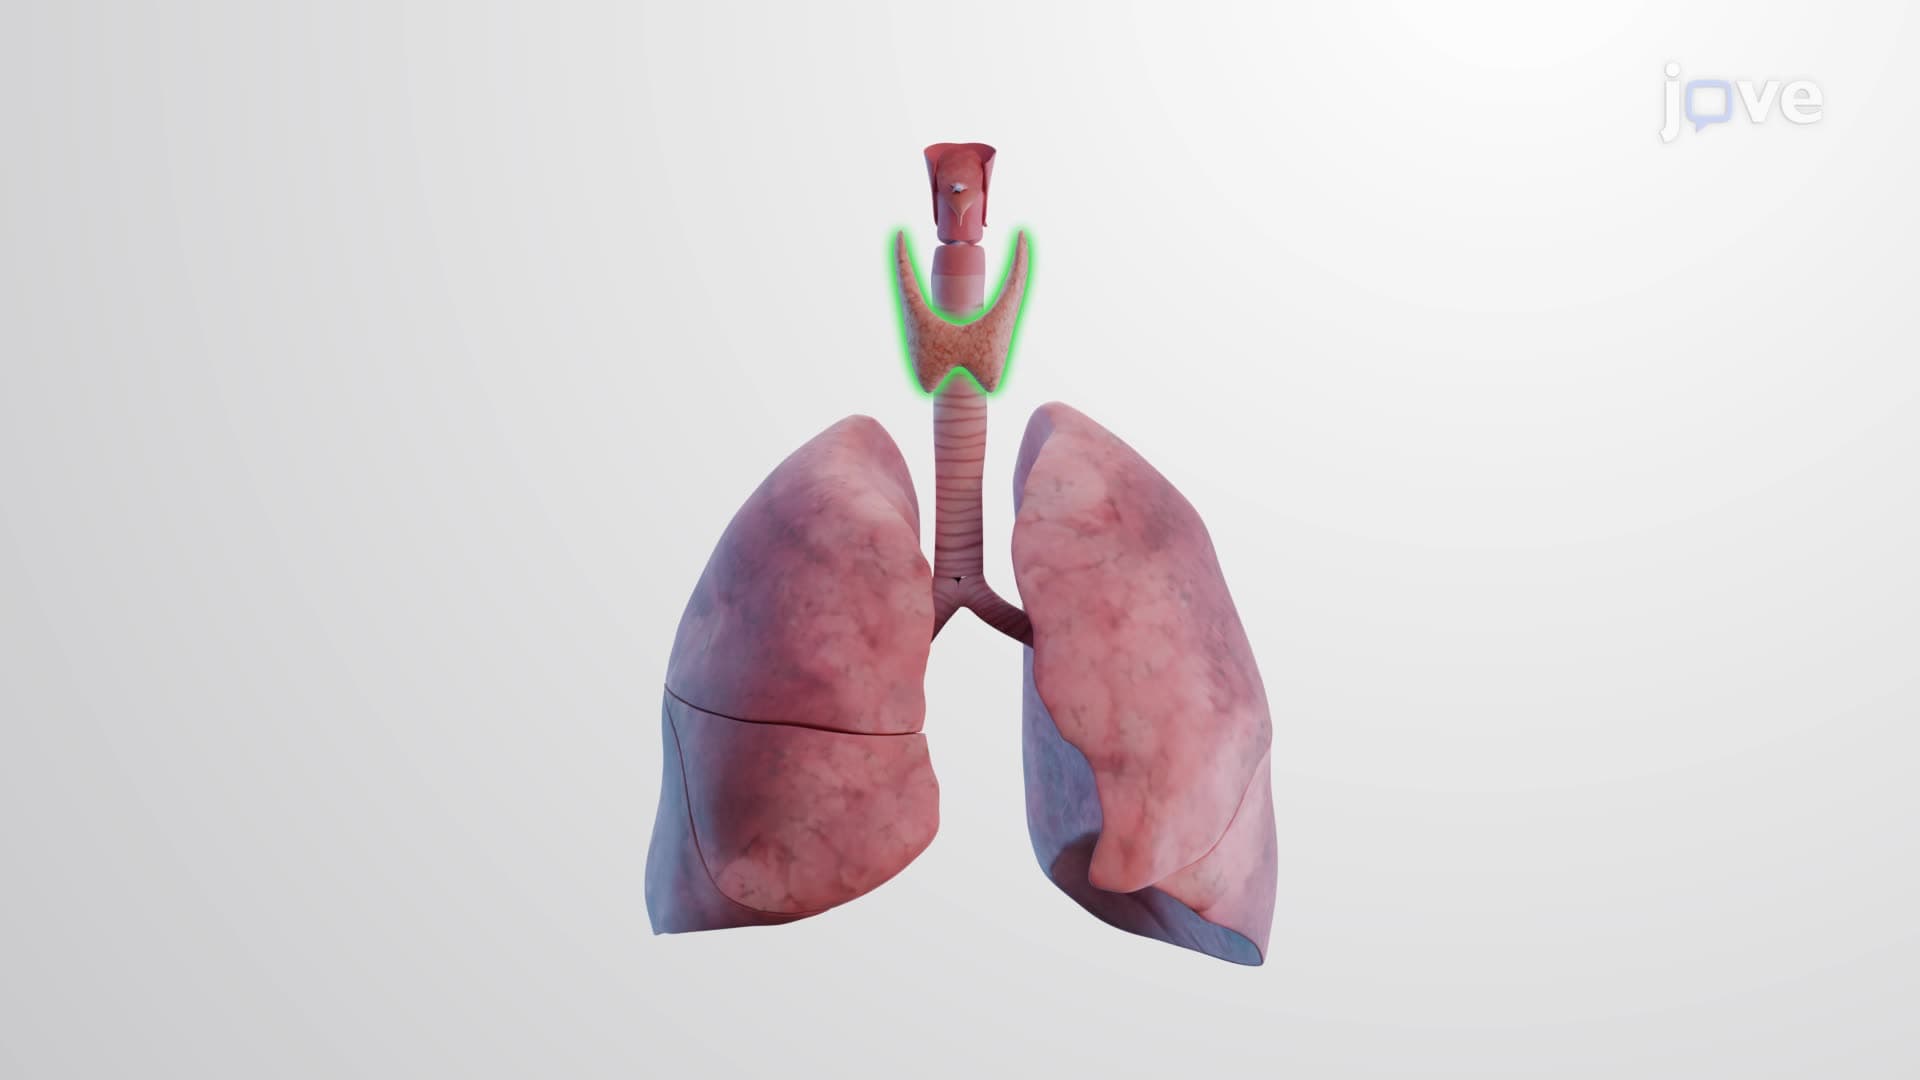 00:59
The Parathyroid Glands
Oxyphil cells, whose functions remain elusive, emerge during late puberty, adding a layer of complexity to the parathyroid gland's intricacies. In contrast, principal parathyroid cells undertake a vital role by...
 01:17
Hormones and Bone Tissue
Hormones That Influence Osteoblasts and/or Maintain the Matrix
Several hormones are necessary for controlling bone growth and maintaining the bone matrix. The pituitary gland secretes growth hormone (GH), which, as its name implies, controls bone growth. This happens in several ways: first, it triggers chondrocyte...
 01:24
Chronic Kidney Disease II: Clinical Manifestations
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...