
Transdiagnostic and Illness-Specific Functional Dysconnectivity Across Schizophrenia, Bipolar Disorder, and Major
Chu-Chung Huang1, Qiang Luo2, Lena Palaniyappan3
1The Institute of Science and Technology for Brain-Inspired Intelligence, Fudan University, Shanghai, China; Key Laboratory of Computational Neuroscience and Brain-Inspired Intelligence (Fudan University), Ministry of Education, Shanghai, China; Institute of Neuroscience, National Yang-Ming University, Taipei, Taiwan.

Background:
Mental disorders are typically defined as distinct diagnostic entities, but similar patterns of clinical and cognitive impairments are frequently found across diagnostic groups. We investigated whether these transdiagnostic deficits result from common neural substrates across disorders or various illness-specific mechanisms, or a combination of both.
Methods:
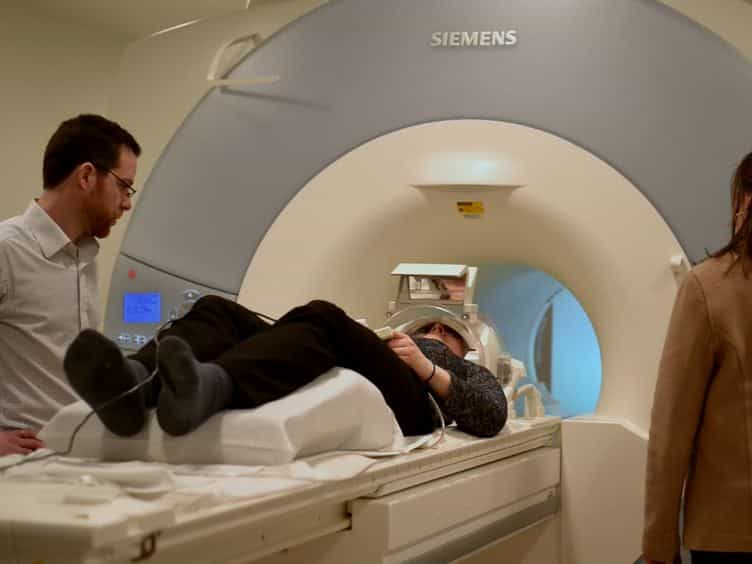
Functional magnetic resonance imaging data were collected from clinically stable patients with major depressive disorder (n = 53), bipolar disorder (n = 78), or schizophrenia (n = 100) and matched healthy control subjects (n = 109) using a single scanner. Group comparisons were conducted to identify transdiagnostic and illness-specific features, and possible confounding effects of medication were considered. A multivariate approach with cross-validation was used to associate dysconnectivity features with shared cognitive deficits.
Results:
Transdiagnostic dysconnectivities were identified within somatomotor (Cohen's d = 0.50-0.58) and salience (Cohen's d = 0.52-0.58) networks and between subcortical-limbic (Cohen's d = 0.55-0.69) and subcortical-dorsal attention (Cohen's d = 0.56-0.61) networks. The executive control network was found to be illness-specifically disconnected from the prefrontal-limbic-pallidal circuit in major depressive disorder (Cohen's d = 0.57-0.58), prefronto-striato-parietal circuit in bipolar disorder (Cohen's d = 0.48-0.53), and default mode network in schizophrenia (Cohen's d = 0.47-0.56). Working memory deficits were associated with a linear combination of 11 transdiagnostic and 5 illness-specific dysconnectivities (r = .322, p= 9.7 × 10⁻⁴, n = 340). The associations of the identified dysconnectivities with medication dosage were nonsignificant.
Conclusions:
Disconnectivity in the somatomotor network was a common transdiagnostic profile, while there were illness-specific patterns in different parts of the prefrontal cortex for different disorders. These findings suggest that prominent psychiatric disorders share common impairments, possibly linked to perception and motor output, as well as unique dysconnectivity profiles that hypothetically mediate the more distinctive features of the disorder-specific psychopathology.

Related Concept Videos
 01:30
Bipolar Disorder
 01:30
Negative and Cognitive Symptoms of Schizophrenia
Negative Symptoms
Negative symptoms of schizophrenia manifest as deficits in normal emotional and behavioral functioning, profoundly impacting daily life. Individuals with schizophrenia often display a flat affect, characterized by a near-total absence of emotional expression,...
 01:29
Biological Causes of Schizophrenia
Genetic Factors in Schizophrenia
The genetic basis of schizophrenia is strongly supported by family and twin...
 01:27
Depressive Disorders: MDD and Dysthymia
 01:18
Depression: Overview
 01:17
Schizophrenia