Related Experiment Video
Updated: Dec 24, 2025


Author Spotlight: Repetitive Transcranial Magnetic Stimulation Combined with Movement Observation in Cerebral Palsy
Published on: August 9, 2024
Botulinum toxin for the management of spasticity in multiple sclerosis: the Italian botulinum toxin network study
Marcello Moccia1,2, Jessica Frau3, Antonio Carotenuto4
1Multiple Sclerosis Clinical Care and Research Centre, Department of Neuroscience, Reproductive Sciences and Odontostomatology, "Federico II" University of Naples, Via Sergio Pansini 5, edificio 17 piano terra, 80131, Naples, Italy. moccia.marcello@gmail.com.

Background:
Botulinum toxin (BT) is an effective and safe treatment for spasticity, with limited evidence in multiple sclerosis (MS). We aim to describe the use of BT for the management of MS spasticity in the clinical practice, its combination with other anti-spastic treatments in MS and possible MS clinical correlates.
Methods:
This is a multicentre cross-sectional observational study including 386 MS patients, receiving BT for spasticity in 19 Italian centres (age 53.6 ± 10.9 years; female 228 (59.1%); disease duration 18.7 ± 9.2 years; baseline Expanded Disability Status Scale (EDSS) 6.5 (2.0-9.0)).
Results:
BT was used for improving mobility (n = 170), functioning in activities of daily living (n = 56), pain (n = 56), posturing-hygiene (n = 63) and daily assistance (n = 41). BT formulations were AbobotulinumtoxinA (n = 138), OnabotulinumtoxinA (n = 133) and IncobotulinumtoxinA (n = 115). After conversion to unified dose units, higher BT dose was associated with higher EDSS (Coeff = 0.591; p < 0.001), higher modified Ashworth scale (Coeff = 0.796; p < 0.001) and non-ambulatory patients (Coeff = 209.382; p = 0.006). Lower BT dose was used in younger patients (Coeff = - 1.746; p = 0.009), with relapsing-remitting MS (Coeff = - 60.371; p = 0.012). BT dose was higher in patients with previous BT injections (Coeff = 5.167; p = 0.001), and with concomitant treatments (Coeff = 43.576; p = 0.022). Three patients (0.7%) reported on post-injection temporary asthenia/weakness (n = 2) and hypophonia (n = 1).
Conclusion:
BT was used for spasticity and its consequences from the early stages of MS, without significant adverse effects. MS-specific goals and injection characteristics can be used to refer MS patients to BT treatment, to decide for the strategy of BT injections and to guide the design of future clinical trials and observational studies.

Related Concept Videos
 01:26
Directly Acting Muscle Relaxants: Dantrolene and Botulinum Toxin
The binding of dantrolene to the RYR1...
 01:31
Skeletal Muscle Relaxants: Therapeutic Uses
 01:28
Classification of Skeletal Muscle Relaxants
Peripherally acting skeletal muscle relaxants interfere with the neurotransmission at the neuromuscular end plate to induce paralysis during...
 01:09
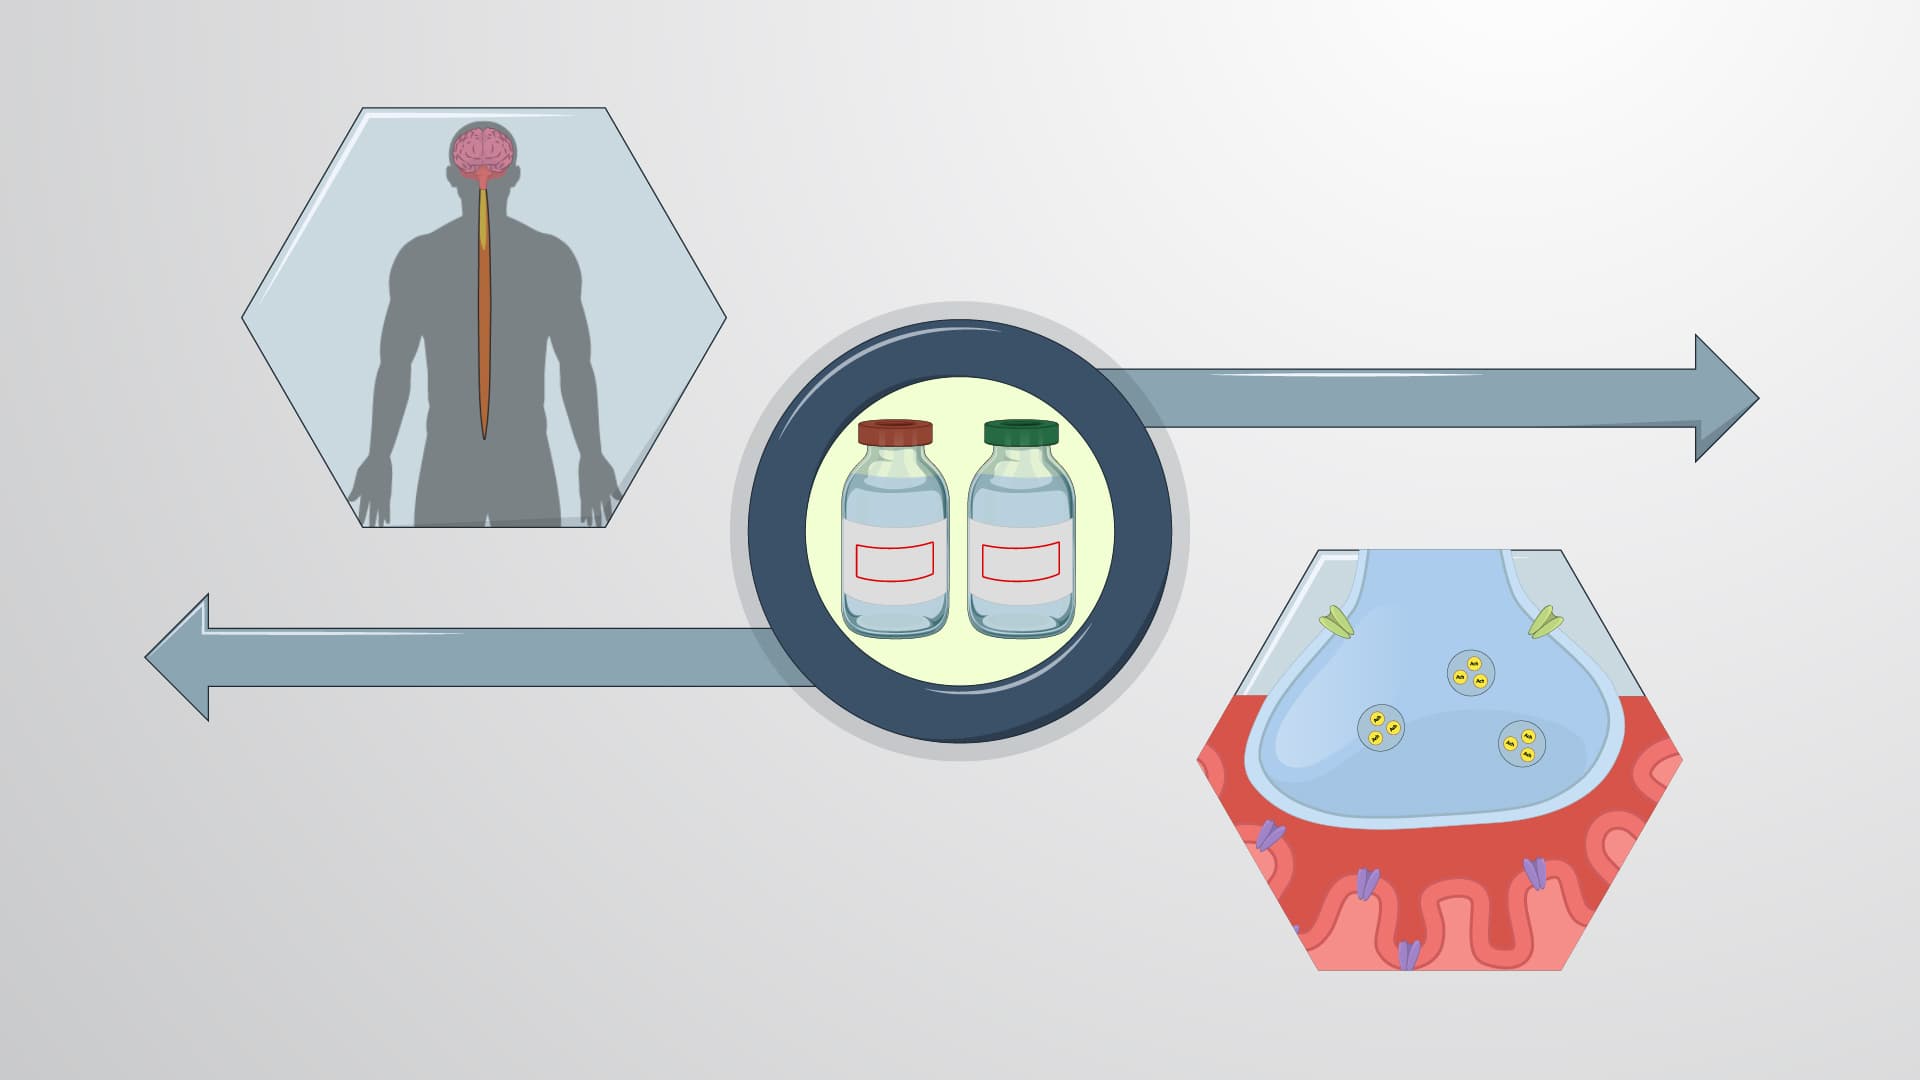
Peripherally and Centrally Acting Muscle Relaxants: A Comparison
Centrally acting muscle relaxants can be further divided into spasmolytic and antispasmodic drugs. Spasmolytic...
 01:29
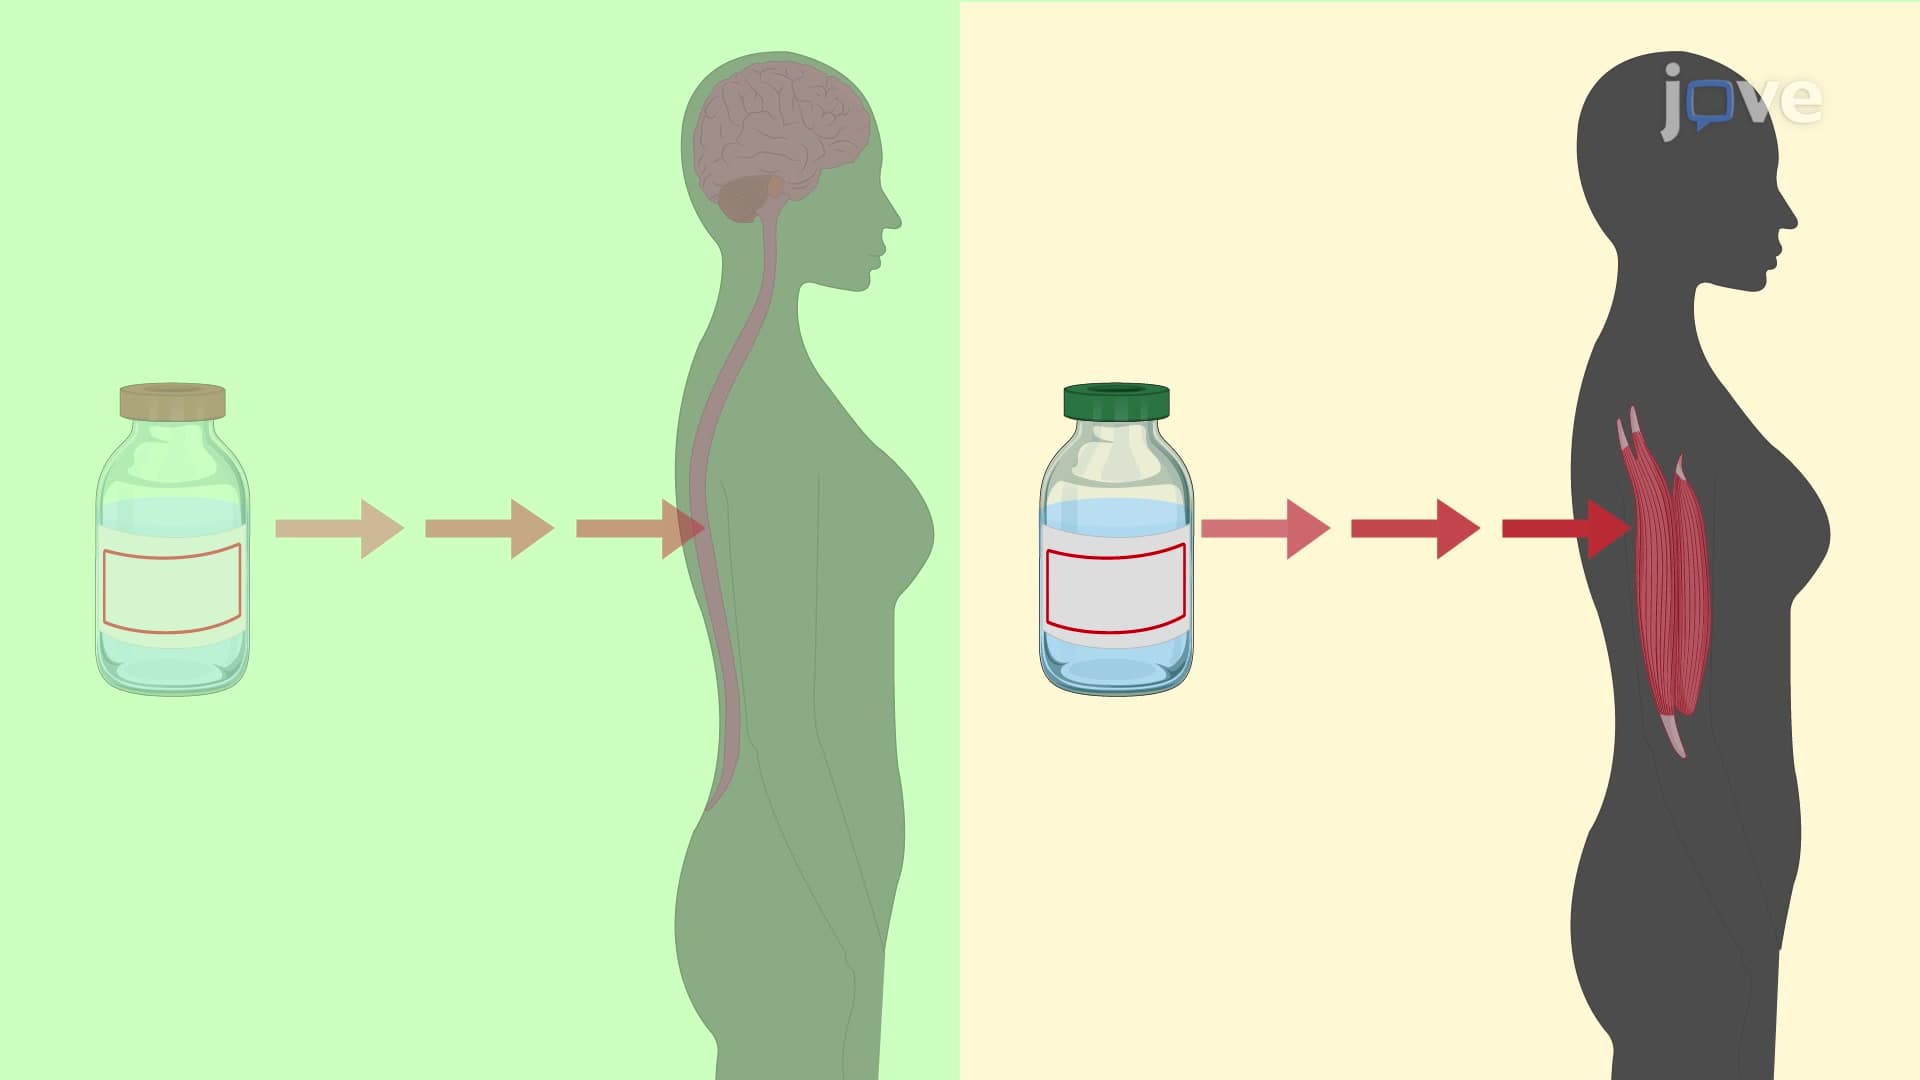
Spasmolytic Agents: Chemical Classification
A major class of centrally acting spasmolytics is the α2-agonist, such as tizanidine. These drugs bind to α2-adrenoceptors, inhibiting the release of the excitatory neurotransmitter glutamate. They also...
 01:24
Centrally Acting Muscle Relaxants: Therapeutic Uses
Centrally acting drugs are classified into spasmolytic and antispasmodic drugs. Spasmolytic drugs such as baclofen, diazepam, and tizanidine inhibit spinal motor neurons and decrease muscle tone. Spasmolytic drugs are administered for severe and chronic spasms due to multiple sclerosis, cerebral palsy, stroke, and spinal cord and muscle injuries. However,...