[Extracorporeal membrane oxygenation (ECMO) in adults]
Related Experiment Video
Updated: Dec 24, 2025
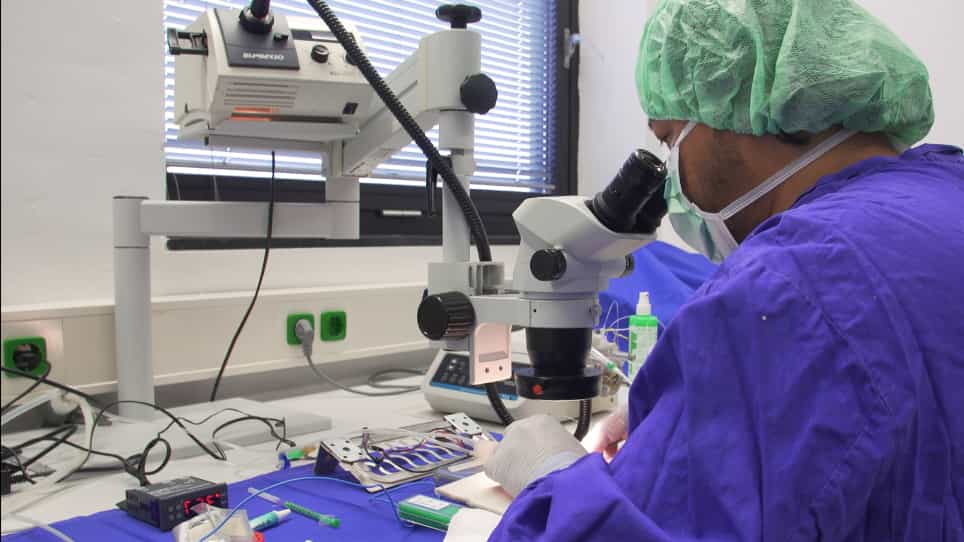
Veno-Venous Extracorporeal Membrane Oxygenation in a Mouse
Published on: October 24, 2018
1Institut für Anästhesiologie und Operative Intensivmedizin Universitätsklinikum Mannheim Theodor-Kutzer-Ufer 1-3 68167 Mannheim, Germany Tel.: (1149)621/383-5963 /383-1952 E-Mail: juergen.meinhardt@anaes.ma.uni-heidelberg.de, , , , DE.

Abstract:
Despite ongoing discussions, ECMO (extracorporeal membrane oxygenation) has become an important part of treatment options in acute lung injury and ARDS (acute respiratory distress syndrome) even in adults. On the other hand, none of the two RCT (randomized controlled trial) studies resulted in reduced letality of the artificial lung therapy when compared to convention treatment. Both authors concluded, that ECMO is not recommended in ARDS. Meanwhile experience with ECMO in adults is extensive in various institutions worldwide, exceeding 1000 patients by the end of 2001. Growing experience and improved technical equipment reduce the rate of technical complications substantially. However, for different reasons ECMO incidence in adults is progressively decreasing in recent years. Inclusion and exclusion criteria vary among different ECMO centers. Potential reversibility of lung injury and persisting life-threatening gas exchange disorder under maximal conventional therapy are commonly seen as requirements for ECMO therapy. ECMO criteria are Murray lung injury score >3.5 (chest x-ray, PaO2/FiO2-index, static compliance Cstat, PEEP), Morel-classification >3 (chest x-ray, AaDO2/FiO2-index, Cstat, PEEP), AaDO2 >600mmHg, intrapulmonal shunt QS/QT >30%, and increase in extravascular lung water >15 ml/kg bodyweight. Commonly accepted absolute contraindications are (1) severely consuming disorders with poor prognosis, (2) CNS damage with poor prognosis, (3) advanced chronic lung disorders, and (4) progressive multiple organ failure. Relative contraindications are immunosuppresion, active bleeding, age over 60 years, and days on mechanical ventilation. In our experience, early contact to an ECMO reference center can optimise early identification of patients which benefit from ECMO, as well as treatment and transportation modalities, and improves outcome. Due to high technical and personal requirements and decreasing incidence in the adult sector, ECMO should be limited to a small number of reference centers with substantial experience in extracorporeal circulation.
More Related Videos
 03:40
Point-of-Care Ultrasound for Peripheral Veno-Arterial Extracorporeal Membrane Oxygenation Without Left Ventricular Venting
Published on: January 17, 2025
 09:54
Lung Rapid Recovery Procurement Combined with Abdominal Normothermic Regional Perfusion in Controlled Donation after Circulatory Death
Published on: August 15, 2022
Related Concept Videos
 01:16
Oxygen Delivering System II: Venturi Mask and Transtracheal Oxygen
Venturi Mask
The Venturi mask, named after the Venturi effect, is designed to deliver precise oxygen concentrations. It consists of a large tube with an oxygen inlet that narrows down, causing a pressure drop that pulls air in through adjustable side ports. The mask is a lightweight,...
 01:17
Assessment of Diffusion and Perfusion
The Role of Diffusion in Respiration
Diffusion is the process by which molecules move from an area of higher concentration to an area of lower concentration. In the respiratory system, this...
 01:30
Administering Oxygen by Mask
Administering oxygen by mask is a common nursing intervention that provides supplemental oxygen to patients with respiratory distress or chronic lung conditions. This procedure involves delivering oxygen at a specified rate through a face mask connected to an oxygen source.
Equipment
The equipment necessary for this procedure includes:
 01:23
Acute Respiratory Failure-IV
 01:30
Acute Respiratory Failure-III
 01:21
Cardiopulmonary Resuscitation I: Adult