Related Experiment Video
Updated: Dec 23, 2025


Integration of Brain Tissue Saturation Monitoring in Cardiopulmonary Exercise Testing in Patients with Heart Failure
Published on: October 1, 2019
Early Warning of Acute Altitude Sickness by Physiological Variables and Noninvasive Cardiovascular Indicators
Zong Bin Li1, Chun Wei Liu1, Jun Guo1
1Department of Cardiology, Chinese PLA General Hospital, Beijing 100853, China.

Abstract:
Objective To examine if the variations at sea level would be able to predict subsequent susceptibility to acute altitude sickness in subjects upon a rapid ascent to high altitude. Methods One hundred and six Han nationality male individuals were recruited to this research. Dynamic electrocardiogram, treadmill exercise test, echocardiography, routine blood examination and biochemical analysis were performed when subjects at sea level and entering the plateau respectively. Then multiple regression analysis was performed to construct a multiple linear regression equation using the Lake Louise Score as dependent variable to predict the risk factors at sea level related to acute mountain sickness (AMS). Results Approximately 49.05% of the individuals developed AMS. The tricuspid annular plane systolic excursion (22.0±2.66 vs. 23.2±3.19 mm, t=1.998, P=0.048) was significantly lower in the AMS group at sea level, while count of eosinophil [(0.264±0.393)×109/L vs. (0.126±0.084)×109/L, t=-2.040, P=0.045], percentage of differences exceeding 50 ms between adjacent normal number of intervals (PNN50, 9.66%±5.40% vs. 6.98%±5.66%, t=-2.229, P=0.028) and heart rate variability triangle index (57.1±16.1 vs. 50.6±12.7, t=-2.271, P=0.025) were significantly higher. After acute exposure to high altitude, C-reactive protein (0.098±0.103 vs. 0.062±0.045 g/L, t=-2.132, P=0.037), aspartate aminotransferase (19.7±6.72 vs. 17.3±3.95 U/L, t=-2.231, P=0.028) and creatinine (85.1±12.9 vs. 77.7±11.2 mmol/L, t=-3.162, P=0.002) were significantly higher in the AMS group, while alkaline phosphatase (71.7±18.2 vs. 80.6±20.2 U/L, t=2.389, P=0.019), standard deviation of normal-to-normal RR intervals (126.5±35.9 vs. 143.3±36.4 ms, t=2.320, P=0.022), ejection time (276.9±50.8 vs. 313.8±48.9 ms, t=3.641, P=0.001) and heart rate variability triangle index (37.1±12.9 vs. 41.9±11.1, t=2.020, P=0.047) were significantly lower. Using the Lake Louise Score as the dependent variable, prediction equation were established to estimate AMS: Lake Louise Score=3.783+0.281×eosinophil-0.219×alkaline phosphatase+0.032×PNN50. Conclusions We elucidated the differences of physiological variables as well as noninvasive cardiovascular indicators for subjects after high altitude exposure compared with those at sea level. We also created an acute high altitude reaction early warning equation based on the physiological variables and noninvasive cardiovascular indicators at sea level.
More Related Videos
 10:21
Evaluation of Hydration Status by Bioelectrical Impedance Vector Analysis in Patients with Ischemic Heart Disease Undergoing Exercise Stress Test
Published on: September 22, 2023
 09:33
Using Near-Infrared Spectroscopy Wearable Devices to Identify Central Versus Peripheral Limitations During Exercise
Published on: December 19, 2024
Related Concept Videos
 01:23
Acute Respiratory Failure-IV
 01:26
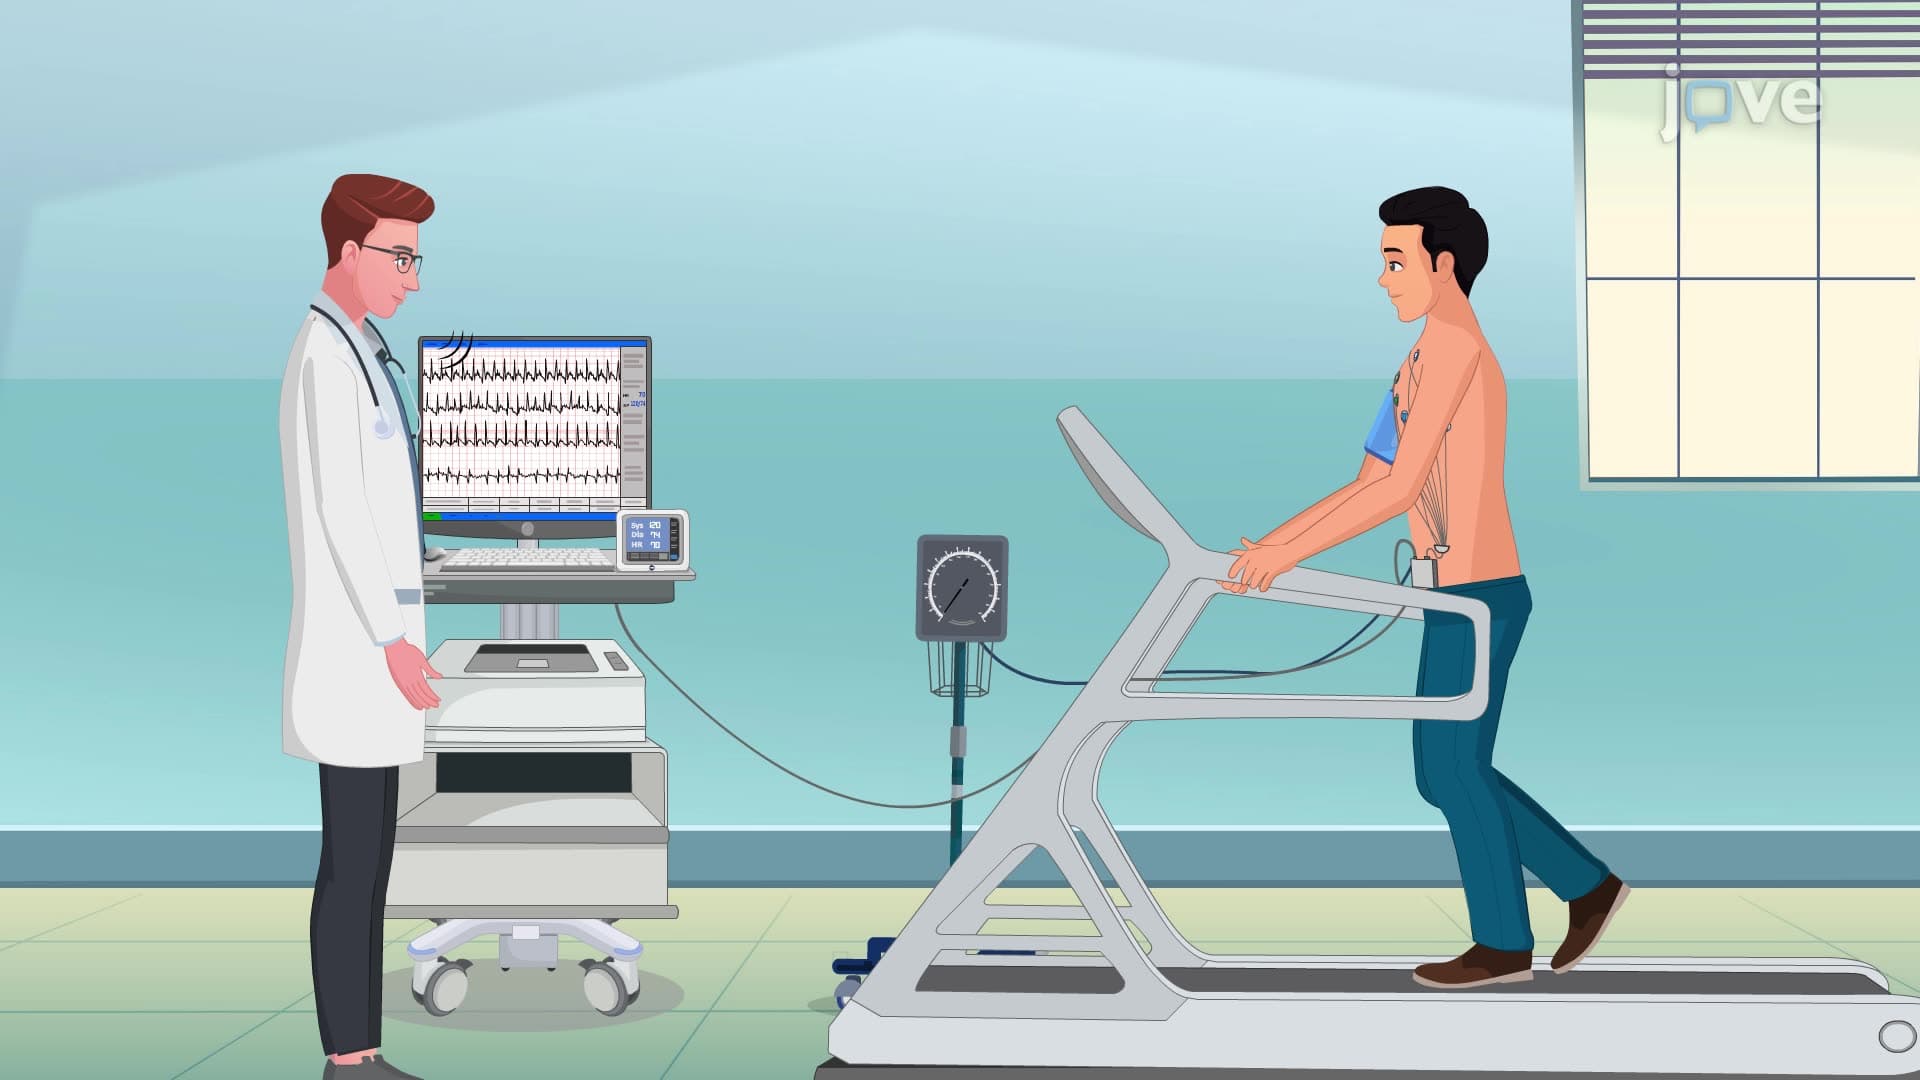
Exercise Stress Test
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes
 01:27
Physical Assessment of the Respiratory Tract II: Inspection
Chest Configuration
The chest configuration...
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:30
Hypertension III: Clinical Manifestations and Diagnostic Studies
 01:25
Hyperpnea and Hyperventilation