Related Experiment Video
Updated: Dec 23, 2025


Live Imaging and Quantification of Viral Infection in K18 hACE2 Transgenic Mice Using Reporter-Expressing Recombinant SARS-CoV-2
Published on: November 5, 2021
SARS-COV-2 infection (coronavirus disease 2019) for the gastrointestinal consultant
Kaveh Hajifathalian1, Srihari Mahadev1, Robert E Schwartz1
1Division of Gastroenterology and Hepatology, Weill Cornell Medicine, New York-Presbyterian Hospital, New York, NY 10021, United States.

Abstract:
The current pandemic due to the severe acute respiratory syndrome coronavirus 2 has caused an extreme burden for health care systems globally, and the number of cases is expected to continue to increase, at least in the immediate future. The virus is estimated to have infected more than 1.5 million individuals. The available reports suggest that gastrointestinal (GI) involvement in coronavirus disease 2019 (COVID-19) is common and in some cases the GI symptoms may precede the respiratory symptoms. In addition to direct effects of severe acute respiratory syndrome coronavirus 2, the infected patients remain at risk for the complications commonly managed by gastroenterology and hepatology consultants. The most commonly reported GI manifestation of COVID-19 is diarrhea, which is reported in a third to up to more than half of the patients. Mild to moderate elevation of the liver enzymes are also common, although no case of acute liver failure has been reported so far. Many of the medications used for treatment of COVID-19 can also be associated with GI symptoms or liver injury and can be included in the differential diagnosis in these patients. Although the diagnosis of the infection is currently based on RNA analysis in respiratory samples, the available literature on fecal shedding of this virus suggests that fecal RNA testing might prove to be a useful diagnostic test. It is reasonable to delay all non-urgent endoscopic procedures during the peak of the pandemic and use additional protective equipment such as N95 respirators during endoscopy while most patients can be considered high risk for having been exposed to the virus.
More Related Videos
 10:25
Detection of SARS-CoV-2 Neutralizing Antibodies using High-Throughput Fluorescent Imaging of Pseudovirus Infection
Published on: June 5, 2021
 07:59
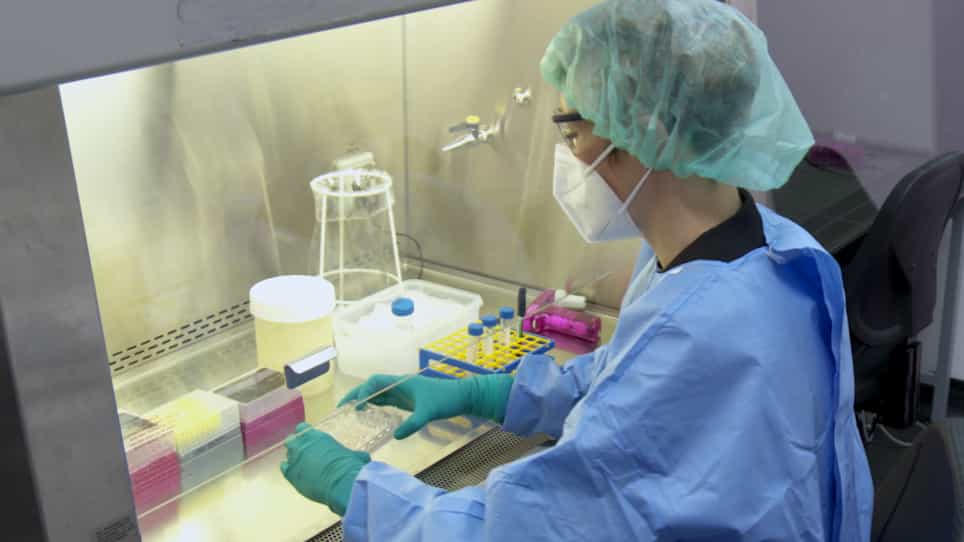
Adapting Gastrointestinal Organoids for Pathogen Infection and Single Cell Sequencing under Biosafety Level 3 BSL-3 Conditions
Published on: September 10, 2021
Related Concept Videos
 01:03
Rous Sarcoma Virus (RSV) and Cancer
RSV is a retrovirus that contains two copies of a plus-strand RNA genome. Its genome consists of four main open...
 01:30
Urinary Tract Infection III: Diagnostic Studies and Interprofessional Care
 01:23
Gastritis III: Clinical Manifestations and Management
Clinical manifestations of acute gastritis
The patient with acute gastritis may have a rapid onset of symptoms, such as epigastric pain or discomfort, dyspepsia, anorexia, hiccups, or nausea and vomiting, which can last from a few hours to a few days. Erosive or hemorrhagic gastritis may cause bleeding, which may manifest as blood in vomit or as...
 01:30
Irritable Bowel Syndrome II: Clinical Features and Diagnostic Evaluation
Irritable Bowel Syndrome (IBS) is classified into subtypes based on the predominant bowel habits as determined by the Bristol Stool Form Scale (BSFS). The subtypes are:
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
 01:30
Serum Laboratory Studies, Stool Test, Breath Test