Related Experiment Video
Updated: Dec 22, 2025
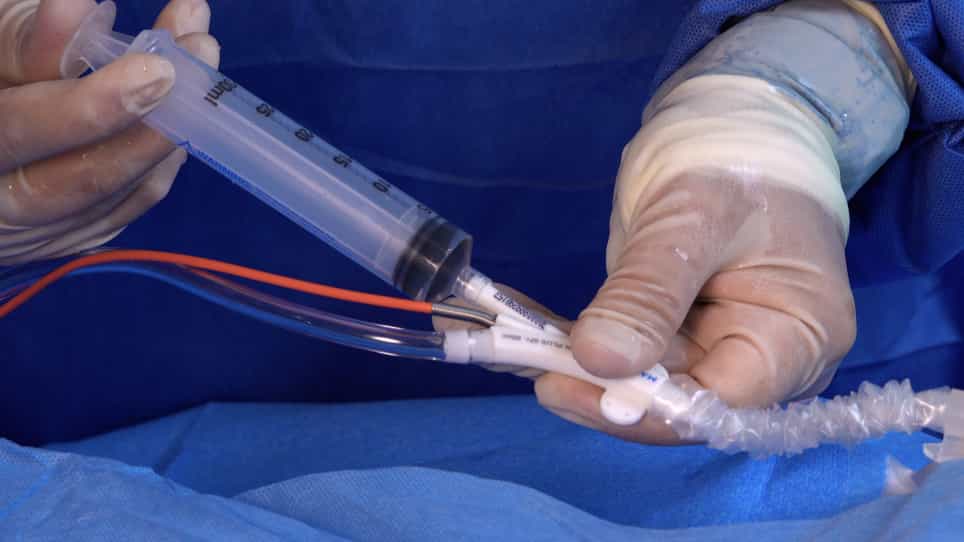

The Intra-Aortic Balloon Pump
Published on: February 5, 2021
Circulatory support with larger volume intra-aortic balloon pump vs. standard volume or no-balloon pump during
Aleksander Zeliaś1, Wojciech Zajdel2, Krzysztof Malinowski3
1Department of Cardiology and Cardiovascular Interventions, University Hospital, Krakow, Poland.

Insights
Larger volume intra-aortic balloon pumps may improve hemodynamic stability during high-risk percutaneous coronary interventions. However, this study found no significant impact on major adverse cardiac events or safety outcomes compared to standard or no support.
Area of Science:
- Cardiology
- Interventional Cardiology
- Medical Devices
Background:
- High-risk percutaneous coronary intervention (HRPCI) carries significant risks of periprocedural complications like hypotension and shock.
- Mechanical circulatory support devices are crucial for stabilizing patients during HRPCI.
Purpose of the Study:
- To evaluate the effectiveness of larger volume intra-aortic balloon pumps (MEGA) versus standard volume (STRD) or no support (CTRL) in HRPCI patients.
- To assess hemodynamic stability and clinical outcomes, including major adverse cardiac events (MACE) and safety endpoints.
Main Methods:
- A single-center, open-label, randomized controlled trial involving 36 HRPCI patients.
- Patients were randomized into MEGA, STRD, or CTRL groups (1:1:1 ratio).
- Primary endpoints included composite hemodynamic endpoint (CHEP) during the procedure and MACE/safety endpoints up to 1-year follow-up.
Main Results:
- While not statistically significant, the MEGA group showed a trend towards reduced CHEP (15.4%) compared to STRD (50.0%) and CTRL (44.4%) in the per-treatment analysis (p=0.023).
- In-hospital MACE rates were 23.1% (MEGA), 7.1% (STRD), and 33.3% (CTRL) (p=0.25).
- MACE at follow-up and major bleeding rates did not differ significantly across groups.
Conclusions:
- Larger volume intra-aortic balloon pumps may offer benefits in managing hemodynamic instability during HRPCI.
- Further research is needed to confirm the impact on safety and major adverse cardiac events.
Introduction:
Percutaneous coronary intervention in high-risk patients (HRPCI) is associated with increased risk of periprocedural complications such as hypotension and shock. Mechanical circulatory support devices may the bridge patient safely throughout the procedure and are often used in this setting.
Aim:
We assessed the outcomes of patients subjected to HRPCI and supported with intra-aortic balloon pump (IABP) of larger volume (MEGA) compared to standard volume (STRD) or no balloon support at all (CTRL).
Material And Methods:
In this single-centre, open-label, randomised, controlled trial, HRPCI patients were randomly assigned to three groups: MEGA, STRD, and CTRL in a 1 : 1 : 1 scheme. Screening failure patients were assigned to the registry (REG). Composite haemodynamic endpoint (CHEP) was assessed during the procedure and major adverse cardiac even (MACE)/safety endpoints up to 1-year follow-up (FU).
Results:
A total of 36 patients were randomised (13 MEGA, 14 STRD, and 9 CTRL). The incidence of in-hospital MACE was observed in 23.1% of MEGA, 7.1% of STRD and 33.3% of CTRL (p = 0.25) patients; MACE at FU in 50.0%, 35.7%, and 55.6% (p = 0.61); major bleeding in 46.2%, 28.6%, and 22.2%, (p = 0.45); and CHEP in 15.4%, 50.0%, and 44.4%, respectively (p = 0.13). On per-treatment (PT) analysis (16 MEGA, 10 STRD, and 21 CTRL), including 11 patients from REG, in-hospital MACE was observed in 18.8% of MEGA, 10.0% of STRD, and 23.8% of CTRL (p = 0.64) patients; MACE at FU in 53.3%, 20.0%, and 57.1% (p = 0.12); major bleeding in 37.5%, 20.0%, and 33.3% (p = 0.62); and CHEP in 15.5%, 50.0%, and 52.4%, respectively (p = 0.023).
Conclusions:
Larger volume intra-aortic balloon pump might be effective at reducing haemodynamic instability during HRPCI without a statistically significant effect on safety endpoints or MACE.

