Risk of kidney toxicity with carfilzomib in multiple myeloma: a meta-analysis of randomized controlled trials
Related Experiment Video
Updated: Dec 22, 2025

An Organotypic High Throughput System for Characterization of Drug Sensitivity of Primary Multiple Myeloma Cells
Published on: July 15, 2015
Somedeb Ball1, Tapas Ranjan Behera2, Faiz Anwer2
1Department of Internal Medicine, Texas Tech University Health Sciences Center, Lubbock, TX, USA.

Abstract:
The incidence and relative risk of kidney toxicity with carfilzomib in multiple myeloma (MM) has been incompletely characterized. We performed a systematic review and meta-analysis of randomized controlled trials (RCTs) comparing carfilzomib-based with non-carfilzomib-based regimens in MM to investigate the risk of kidney toxicity. Point estimates were pooled in the form of risk ratios (RR) with 95% confidence intervals (CI) using the random-effects model. We identified four RCTs with 2954 patients. The median duration of treatment ranged from 16.3 to 88 weeks in carfilzomib arms. The cumulative rate of kidney toxicities in the carfilzomib arms was 21.3% for all grades and 8.3% for grades 3-5 toxicities, with acute kidney injury being the predominantly reported event. Patients receiving a carfilzomib-based regimen had a significantly higher risk of total kidney toxicity compared with those in the control arms, with pooled RR of 1.79 (95% CI, 1.43-2.23, p < 0.001) and 2.29 (95% CI, 1.59-3.30; p < 0.001), for all grades and grades 3-5 toxicities, respectively. Despite adjustment for the duration of exposure in treatment arms, pooled incidence rate ratios (IRR) for kidney toxicity was significantly increased in the carfilzomib arm compared with control (pooled IRR of 1.28 for all grades and 1.66 for grades 3-5 toxicity). Subgroup analysis based on carfilzomib dose, infusion length, and treatment setting did not identify any significant subgroup effect. Kidney toxicity is an important adverse effect of carfilzomib-based regimens. Prospective studies should investigate patient-, disease-, and treatment-related risk factors for severe kidney toxicities and impact on long-term outcome.
Insights
Carfilzomib treatment for multiple myeloma significantly increases the risk of kidney toxicity, including severe events. Further research is needed to identify risk factors for kidney damage in patients receiving carfilzomib-based regimens.
Area of Science:
- Nephrology
- Hematology
- Oncology
Background:
- Carfilzomib is a proteasome inhibitor used in multiple myeloma (MM).
- The kidney toxicity associated with carfilzomib is not fully understood.
- Assessing kidney toxicity risk is crucial for patient management.
Purpose of the Study:
- To systematically evaluate the incidence and relative risk of kidney toxicity in patients with multiple myeloma treated with carfilzomib.
- To compare kidney toxicity rates between carfilzomib-based and non-carfilzomib-based regimens.
Main Methods:
- A systematic review and meta-analysis of randomized controlled trials (RCTs) was conducted.
- Four RCTs involving 2954 patients were identified and analyzed.
- Risk ratios (RR) and incidence rate ratios (IRR) were pooled using a random-effects model.
Main Results:
- Carfilzomib-based regimens were associated with a significantly higher risk of kidney toxicity (all grades RR: 1.79; grades 3-5 RR: 2.29).
- Adjusted analysis also showed increased kidney toxicity incidence with carfilzomib (all grades IRR: 1.28; grades 3-5 IRR: 1.66).
- Acute kidney injury was the predominant kidney-related adverse event.
Conclusions:
- Kidney toxicity is a significant adverse effect of carfilzomib in multiple myeloma treatment.
- Further prospective studies are warranted to identify risk factors for severe kidney toxicity.
- Understanding these factors can help optimize patient care and long-term outcomes.


Related Concept Videos
 01:28
Drug Dosing in Renal Diseases: Estimation of Glomerular Filtration Rate Based on Serum Creatinine Concentration
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
 01:25
Drug Dosing in Renal Diseases: Measurement of Serum Creatinine Concentration and Clearance
 01:02
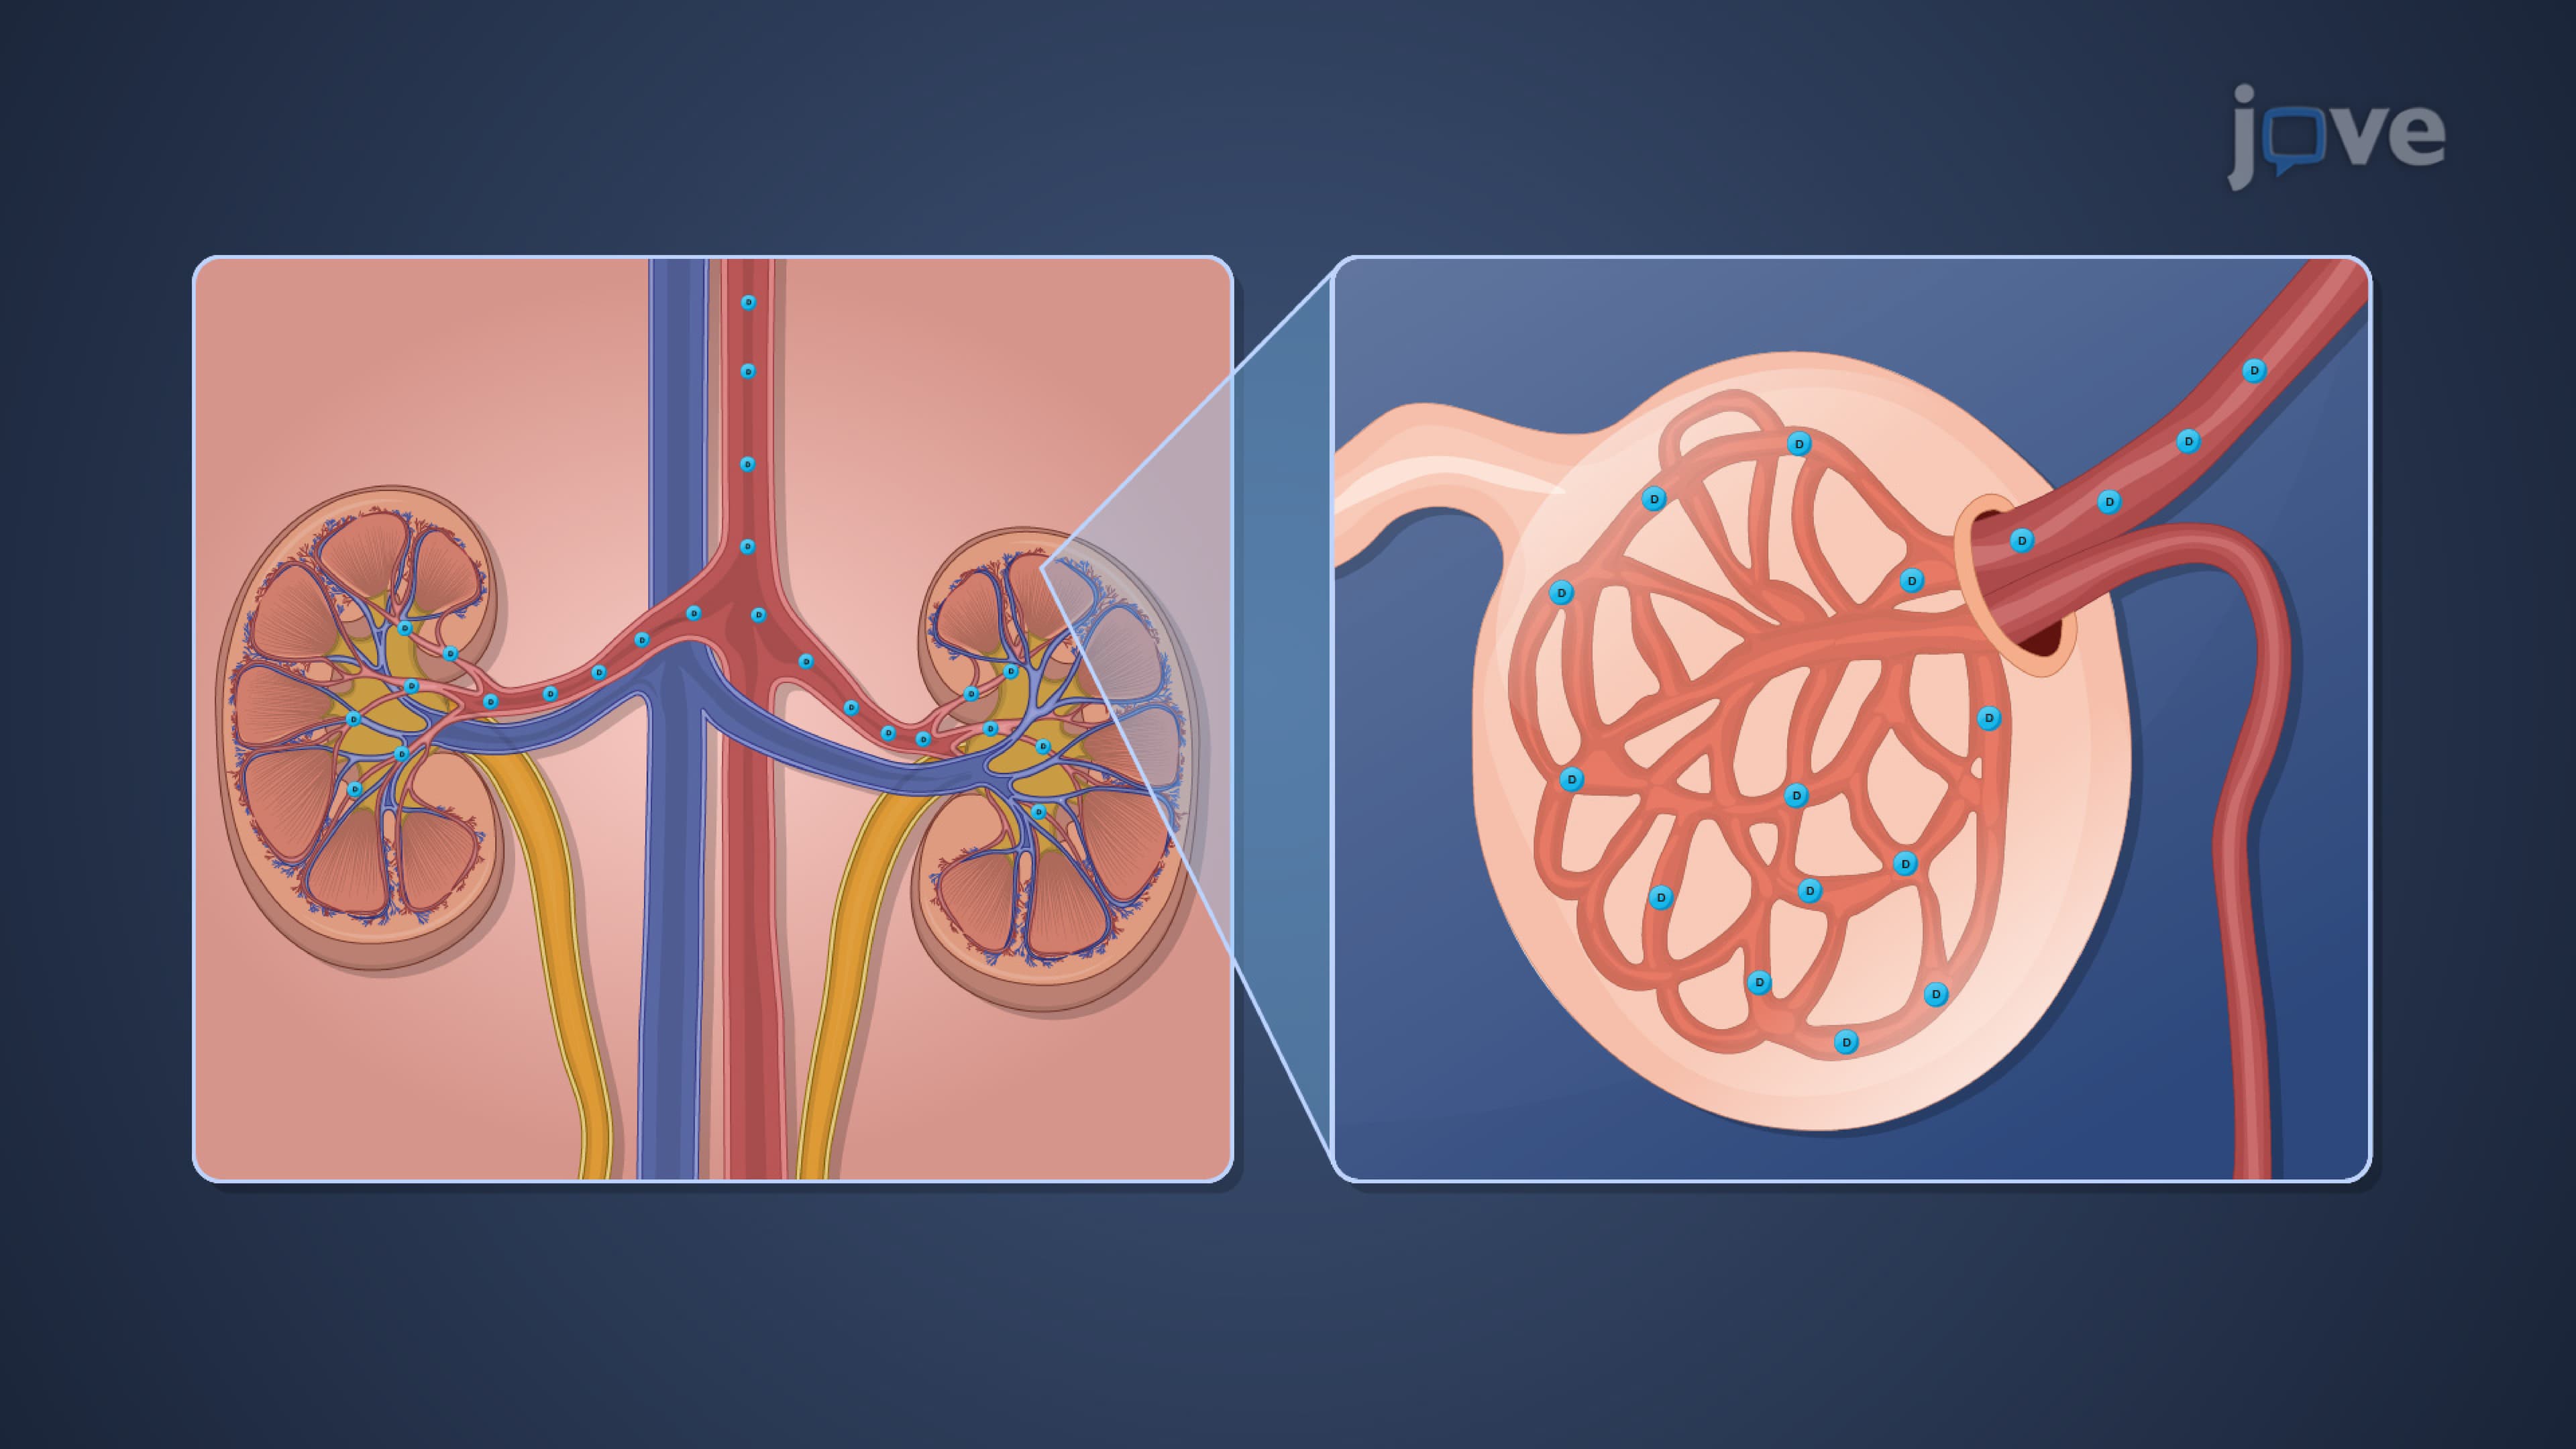
Renal Drug Excretion: Glomerular Filtration
Drugs gain access to the kidney via the renal artery, which progressively branches off into afferent arterioles....