Related Experiment Video
Updated: Sep 30, 2026
Isolation and Kv Channel Recordings in Murine Atrial and Ventricular Cardiomyocytes
Published on: March 12, 2013
Intracellular pH, Na+- and K+-activities at the onset of St. Thomas' cardioplegia: a study with ionselective
B Stinner1, E Krohn, M M Gebhard
1University Clinic of General Surgery, Marburg/FRG.

Insights
The St. Thomas
Area of Science:
- Cardiology
- Cellular Physiology
Background:
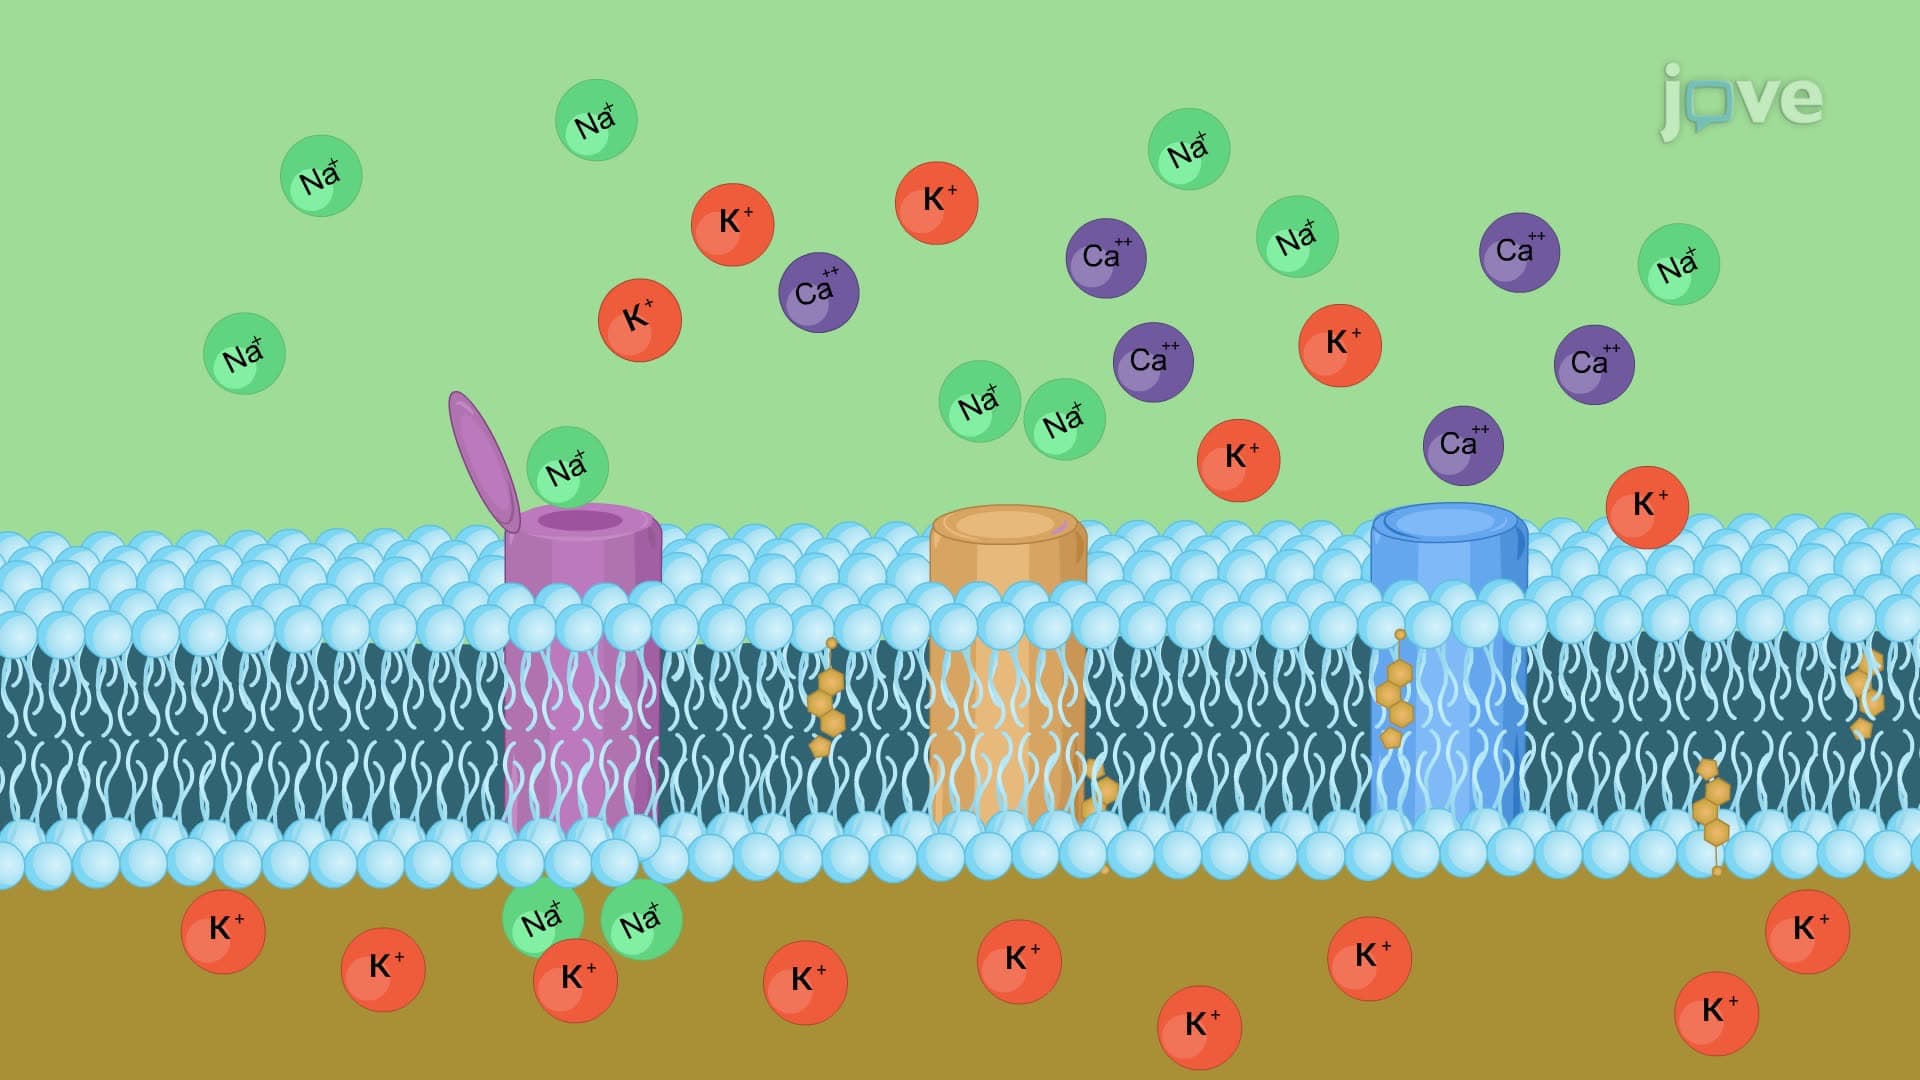
- Cellular edema and cardiac arrhythmias are linked to intracellular ionic shifts.
- These ionic alterations are a clinical concern in heart ischemia and cardioplegia.
- The St. Thomas' Hospital cardioplegic solution is widely used clinically.
Purpose of the Study:
- To investigate if the St. Thomas' Hospital cardioplegic solution may cause cellular edema and cardiac arrhythmias.
- To measure intracellular ionic changes and membrane potential in sheep heart Purkinje fibers exposed to the solution.
Main Methods:
- Direct measurement of membrane potential (EM), intracellular pH (pHi), and intracellular sodium (aiNa) and potassium (aiK) activity.
- Utilized neutral-carrier ion-selective microelectrodes in sheep heart Purkinje fibers.
- Experimental temperature maintained at 35°C.
Main Results:
- St. Thomas' solution caused depolarization (EM to -57.3 mV) and increased aiK (to 127.1 mmol/l).
- A slight decrease in aiNa (to 6.7 mmol/l) was observed without procaine.
- Inhibition of the Na/K pump with dihydroouabaine significantly increased aiNa (to 10.7 mmol/l).
Conclusions:
- The St. Thomas' Hospital cardioplegic solution can induce significant alterations in intracellular ion activity and membrane potential.
- These ionic shifts may predispose to complications like cellular edema and arrhythmias during cardiac procedures.
- Further investigation into the clinical implications of these findings is warranted.
Abstract:
Cellular edema and cardiac arrhythmias are often closely related to intracellular ionic alterations and, moreover, are an actual problem of clinical cardioplegia and ischemia of the heart. In order to investigate whether the clinically widely used cardioplegic solution of the St. Thomas' Hospital may predispose for these complications, membrane potential (EM), intracellular pH (pHi), and intracellular sodium and potassium activity (aiNa- and aiK) in sheep heart Purkinje fibres were directly measured by means of neutral-carrier ion-selective microelectrodes during equilibration of the fibres' extracellular space with the cardioplegic solution. The experimental temperature was 35 degrees C throughout. During control conditions under superfusion of a HEPES-buffered Tyrode solution EM was -74.4 +/- 5.1 mV (n = 39), pHi was 7.18 +/- 0.05 (n = 16), and aiNa and aiK were 7.6 +/- 1.4 mmol/l (n = 15) and 118.9 +/- 4.6 mmol/l (n = 15) respectively. Superfusing the Purkinje strand for 10 minutes with the cardioplegic St. Thomas' solution led to a depolarization to -57.3 +/- 4.7 mV (n = 21), a slight aiNa decrease to 6.7 +/- 1.6 mmol/l (n = 15; p less than 0.01; cardioplegic solution without procaine) and an increase of aiK to 127.1 +/- 4.4 mmol/l (n = 6; p less than 0.01). pHi needed 15 minutes to reach a steady state value of 7.25 +/- 0.05 (n = 9). The alterations on post-cardioplegic reperfusion with Tyrode solution were reversible within 15 minutes. Simulation of the clinical situation of ice-cold application of the solution by inhibiting the cellular Na/K pump via 0.1 mmol/l dihydroouabaine added to the St. Thomas' solution resulted in a marked increase of aiNa to 10.7 +/- 1.5 mmol/l (n = 6; p less than 0.01; no procaine) during cardioplegic superfusion.(ABSTRACT TRUNCATED AT 250 WORDS)