Related Experiment Video
Updated: Dec 22, 2025
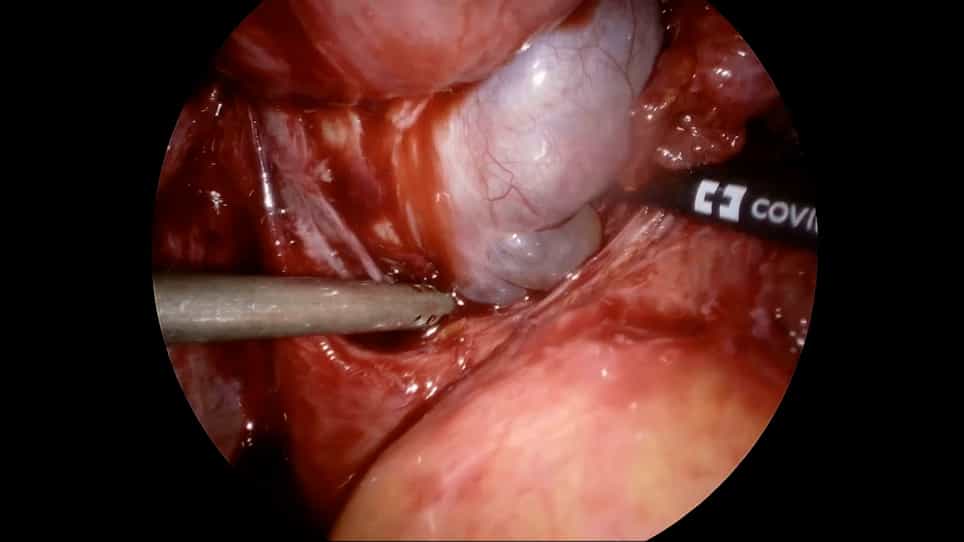

Surgical Techniques to Optimize Ovarian Reserve during Laparoscopic Cystectomy for Ovarian Endometrioma
Published on: January 22, 2022
Laparoscopic tuboplasty for mild distal tubal disease
Sarah Norris1, Charlotte Axelrod2, Mara Sobel1
1Department of Obstetrics and Gynaecology, University of Toronto, Toronto, Ontario, Canada.

Objective:
To review tuboplasty techniques for alleviating fallopian tube blockage.
Design:
A step-by-step explanation of the techniques that comprise tuboplasty-fimbrioplasty, salpingo-ovariolysis, and salpingostomy-with surgical video footage.
Setting:
Academic medical center.
Patient:
A 28-year-old G0 female patient with primary infertility and bilateral fallopian tube occlusion wanting to avoid in vitro fertilization.
Intervention(S):
Tuboplasty and its component techniques of fimbrioplasty, salpingo-ovariolysis, and salpingostomy are demonstrated in a stepwise fashion for a case of mild tubal disease. Fimbrioplasty includes identifying the agglutinated or phimosed fimbrial end and gently opening it with fine forceps and blunt microdissection. Salpingo-ovariolysis is demonstrated with video and comprises: 1) surveying the anatomy; 2) applying traction to delineate the adhesions; and 3) transecting the adhesions with microsurgical scissors or electrosurgery. Finally, the steps of a salpingostomy are demonstrated, including: 1) identifying the length of the fallopian tube; 2) performing chromotubation to delineate tubal obstruction; 3) creating a salpingostomy at the terminal end; and 4) suturing open the salpingostomy site circumferentially to evert the edges.
Main Outcome Measure(S):
Successful restoration of normal tubal anatomy and identification of the location of tubal occlusion to guide salpingostomy site placement.
Result(S):
The fallopian tubes were assessed bilaterally and noted to have mild tubal disease and therefore were appropriate for tuboplasty. Normal tubal anatomy was restored bilaterally through salpingo-ovariolysis. Subsequent identification of the area of tubal occlusion bilaterally and salpingostomy were performed to create a patent fallopian tube able to pick up an oocyte from the ovary and facilitate fertilization.
Conclusion(S):
Tubal reconstructive surgery remains an important option to offer patients who want to avoid in vitro fertilization and who have mild tubal disease.
More Related Videos
 03:55
Urethroplasty with Pedicled Tunica Vaginalis for the Treatment of Long-segment Anterior Urethral Stricture Caused by Lichen Sclerosus of Glans Penis
Published on: October 18, 2024
 03:30
Author Spotlight: Advancing Pelvic Prolapse Treatment with a Non-Mesh Approach using Laparoscopic Pectopexy
Published on: October 25, 2024