
Diabetes Status Affects Odds of Body Mass Index-dependent Adverse Outcomes After Total Hip Arthroplasty
Kareem J Kebaish1, Varun Puvanesarajah, Sandesh Rao
1From the Department of Orthopaedics and Rehabilitation, Yale School of Medicine, New Haven, CT (Mr. Kebaish, Mr. Ottesen, and Dr. Grauer), and the Department of Orthopaedic Surgery, The Johns Hopkins University, Baltimore, MD (Dr. Puvanesarajah, Dr. Rao, Dr. Zhang, and Dr. Khanuja).

Introduction:
Obesity and diabetes have independently been shown to predispose to adverse outcomes after total hip arthroplasty (THA). These may have a coupled effect on perioperative risks. The purpose of this study was to evaluate the effect of body mass index (BMI) on adverse outcomes in nondiabetic (ND), non-insulin-dependent diabetes mellitus (NIDDM), and insulin-dependent diabetes mellitus (IDDM) patients.
Methods:
Patients undergoing primary THA were selected from the National Surgical Quality Improvement Program Database from 2012 to 2016 and categorized as ND, NIDDM, and IDDM. BMI, demographics, and 30-day perioperative outcomes were assessed for each group. Multivariate logistic regressions controlling for demographics, functional status, and American Society of Anesthesiologists were used to determine the odds ratio of serious adverse event (SAE) in each diabetes group for patients with BMI ≥ 40 kg/m compared with a control group of ND patients with a normal BMI (18.5 to 24.9 kg/m).
Results:
A total of 108,177 patients were included. The results demonstrate that ND (odds ratio 1.65; P < 0.001) and NIDDM (odds ratio 1.75; P = 0.007) patients have similar risks of SAE, whereas IDDM (odds ratio 2.79; P < 0.001) patients have a greater risk of adverse events, particularly at BMIs greater than 40 kg/m.
Discussion:
Consistent with previous reports, ND (odds ratio 1.65; P < 0.001) and NIDDM (odds ratio 1.75; P = 0.007) morbidly obese patients (BMI > 40 kg/m) had an increased odds of SAEs after THA, but for IDDM (odds ratio 2.79; P < 0.001) patients this increased odds was notably higher. Although patients with IDDM have increased rates of adverse events compared with ND and NIDDM patients, these findings should not be used to establish strict BMI cutoffs in patients with IDDM. Nonetheless, the results suggest additional factors, such as patient medical history and diabetes control, should be considered when evaluating patients with IDDM for THA.
Level Of Significance:
Level III.
More Related Videos
 09:51
The Transition to an Anterior-Based Muscle Sparing Approach Improves Early Postoperative Function but is Associated with a Learning Curve
Published on: September 7, 2022
 07:43
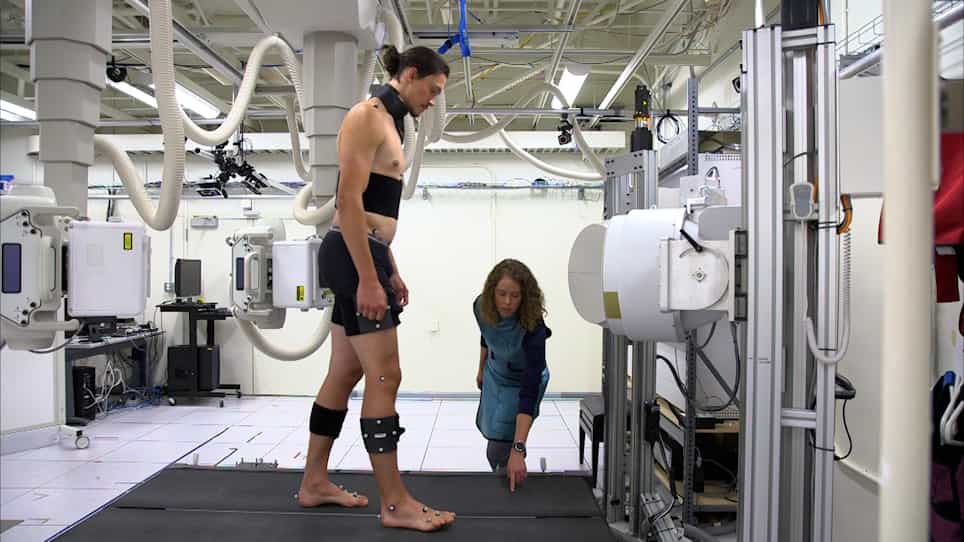
In Vivo Quantification of Hip Arthrokinematics during Dynamic Weight-bearing Activities using Dual Fluoroscopy
Published on: July 2, 2021
Related Concept Videos
 01:22
Diabetes Mellitus: Type 2 and Gestational
 01:15
Diabetes: Symptoms, Diagnosis, and Complications
 01:22
Diabetes Mellitus: Overview and Type I Subtype
Type 1 diabetes is an autoimmune disease in which the immune system mistakenly attacks and destroys the insulin-producing beta cells in the pancreas. As a result, the body is unable to produce sufficient insulin, and individuals with...
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
 01:36
Carbohydrate Metabolism
Starch accounts for approximately 60% of the carbohydrates consumed by humans. Since amylase enzymes cannot function in the stomach's acidic environment, starch can only be digested in the mouth and small intestine. Simple sugars are found naturally in milk and fruits in...
 01:26
Oral Hypoglycemic Agents: Biguanides and Glitazones