Related Experiment Video
Updated: Dec 21, 2025

Nerve Ultrasound Protocol to Detect Dysimmune Neuropathies
Published on: October 7, 2021
Acute Flaccid Myelitis With Neuroradiological Finding of Brachial Plexus Swelling
Pin Fee Chong1, Takeshi Yoshida2, Shota Yuasa3
1Department of Pediatric Neurology, Fukuoka Children's Hospital, Fukuoka, Japan.

Background:
Acute flaccid myelitis is a recently defined clinically distinct syndrome of polio-like acute flaccid paralysis. Acute flaccid myelitis cases show characteristic neuroradiological features of longitudinal spinal cord lesions with predominant gray matter involvement. Current evidence suggests injury to the anterior horn neurons as the underlying mechanism.
Methods:
We describe three patients with acute flaccid myelitis who developed flaccid upper limb weakness with diminished deep tendon reflexes after prodromal fever. Spinal magnetic resonance imaging (MRI) (axial and sagittal T1- and T2-weighted sequences) and brachial plexus MRI (coronal short tau inversion recovery sequence) at the acute stage were performed.
Results:
Spinal MRI showed extensive longitudinal lesion in the spinal cord with predominant gray matter involvement. We were able to demonstrate concurrent swelling and hyperintensity in the brachial plexus in all the three patients at the acute stage.
Conclusion:
The coexisting signal intensities suggest an extension of acute flaccid myelitis pathology to the brachial plexus, highlighting the possible peripheral nerve involvement in acute flaccid myelitis.
Insights
Acute flaccid myelitis (AFM) can affect the brachial plexus, causing upper limb weakness. This study found spinal cord lesions and concurrent brachial plexus swelling in AFM patients.
Area of Science:
- Neurology
- Radiology
- Infectious Diseases
Background:
- Acute flaccid myelitis (AFM) is a distinct neurological syndrome causing polio-like paralysis.
- AFM presents with spinal cord lesions, primarily affecting gray matter and anterior horn neurons.
- The exact mechanisms and full extent of AFM pathology remain under investigation.
Observation:
- This study details three AFM cases presenting with acute flaccid upper limb weakness following fever.
- Both spinal MRI and brachial plexus MRI were utilized to assess the extent of neurological involvement.
- Imaging was performed during the acute phase of the illness to capture early pathological changes.
Findings:
- Spinal MRI revealed extensive longitudinal lesions within the spinal cord, predominantly in the gray matter.
- Crucially, concurrent swelling and hyperintensity were observed in the brachial plexus of all three patients.
- These findings indicate significant pathology extending beyond the central nervous system.
Implications:
- The observed brachial plexus abnormalities suggest peripheral nerve involvement in AFM.
- This expands the understanding of AFM's pathological scope, potentially impacting diagnostic and therapeutic strategies.
- Further research is warranted to elucidate the precise mechanisms of peripheral nerve damage in AFM.
More Related Videos
 11:22
Three-dimensional Imaging of Nociceptive Intraepidermal Nerve Fibers in Human Skin Biopsies
Published on: April 29, 2013
 09:14
Surface Electromyographic Biofeedback as a Rehabilitation Tool for Patients with Global Brachial Plexus Injury Receiving Bionic Reconstruction
Published on: September 28, 2019
Related Concept Videos
 01:22
Spinal Nerves: Plexus I
The Cervical Plexus
The cervical plexus, formed by the anterior rami of the first four...
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:15
Myasthenia Gravis: Diagnostic Tests
The edrophonium test is a diagnostic tool for myasthenia gravis. It involves...
 01:21
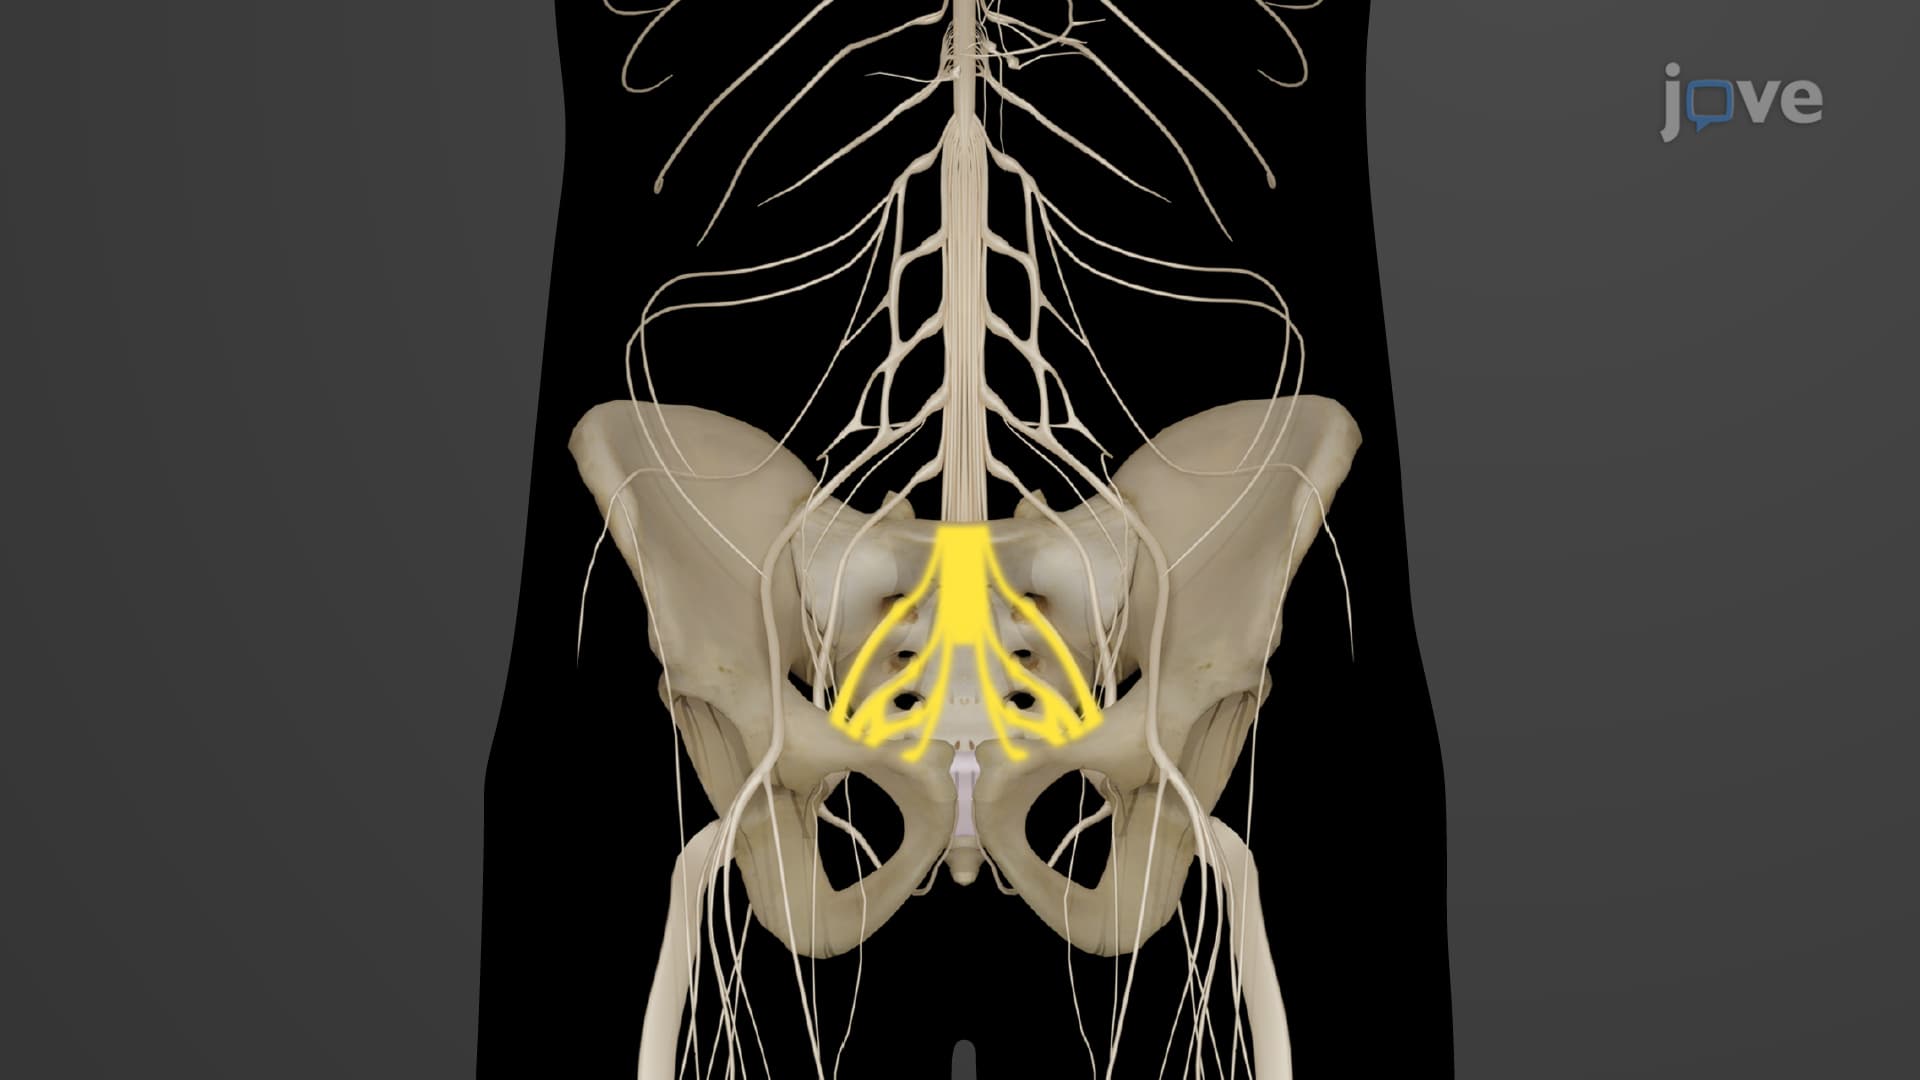
Spinal Nerves: Plexus II
The Lumbar Plexus
The lumbar plexus is situated within the lumbar region of the back and is primarily formed by the first four lumbar spinal nerves (L1 to L4). This plexus extends its branches into several nerves, including the...
 01:27
Assessment of the Cardiovascular System III: Palpation
Jugular Venous Pressure (JVP) Measurement
Position the patient at a thirty- to forty-five-degree angle or in a semi-fowler's position. Look for the highest point of pulsation in the internal jugular vein and measure the vertical distance to the angle of Loius or sternal angle. A normal JVP is 3-4 cm above...