Related Experiment Video
Updated: Dec 21, 2025
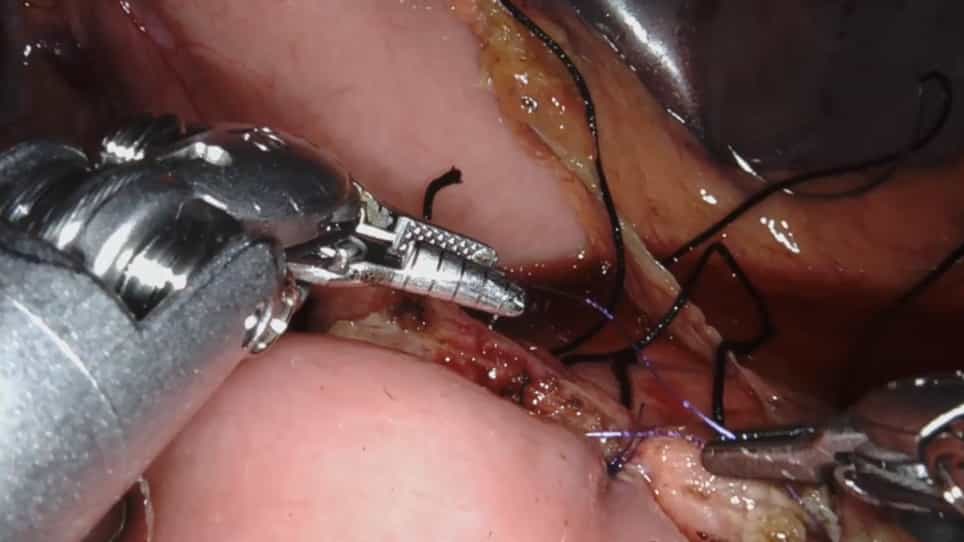

Robotic Central Pancreatectomy with Roux-en-Y Pancreaticojejunostomy
Published on: November 20, 2021
Impact of neoadjuvant therapy on post-operative pancreatic fistula: a systematic review and meta-analysis
Sivesh K Kamarajah1,2, James R Bundred3, Charles Boyle1
1Department of HPB and Transplant Surgery, The Freeman Hospital, Newcastle upon Tyne, Tyne and Wear, UK.

Introduction:
The use of neoadjuvant therapy (NAT) for pancreatic cancer is increasing, although its impact on post-operative pancreatic fistula (POPF) is variably reported. This systematic review and meta-analysis aimed to assess the impact of NAT on POPF.
Methods:
A systematic literature search until October 2019 identified studies reporting POPF following NAT (radiotherapy, chemotherapy or chemoradiotherapy) versus upfront resection. The primary outcome was overall POPF. Secondary outcomes included grade B/C POPF, delayed gastric emptying (DGE), post-operative pancreatic haemorrhage (PPH) and overall and major complications.
Results:
The search identified 24 studies: pancreatoduodenectomy (PD), 19 studies (n = 19 416) and distal pancreatectomy (DP), five studies (n = 477). Local staging was reported in 17 studies, with borderline resectable and locally advanced disease comprising 6% (0-100%) and 1% (0-33%) of the population, respectively. For PD, any NAT was significantly associated with lower rates of overall POPF (OR: 0.57, P < 0.001) and grade B/C POPF (OR: 0.55, P < 0.001). In DP, NAT was not associated with significantly lower rates of overall or grade B/C POPF.
Conclusion:
NAT is associated with significantly lower rates of POPF after PD but not after DP. Further studies are required to determine whether NAT should be added to POPF risk calculators.