Related Experiment Video
Updated: Jun 30, 2026


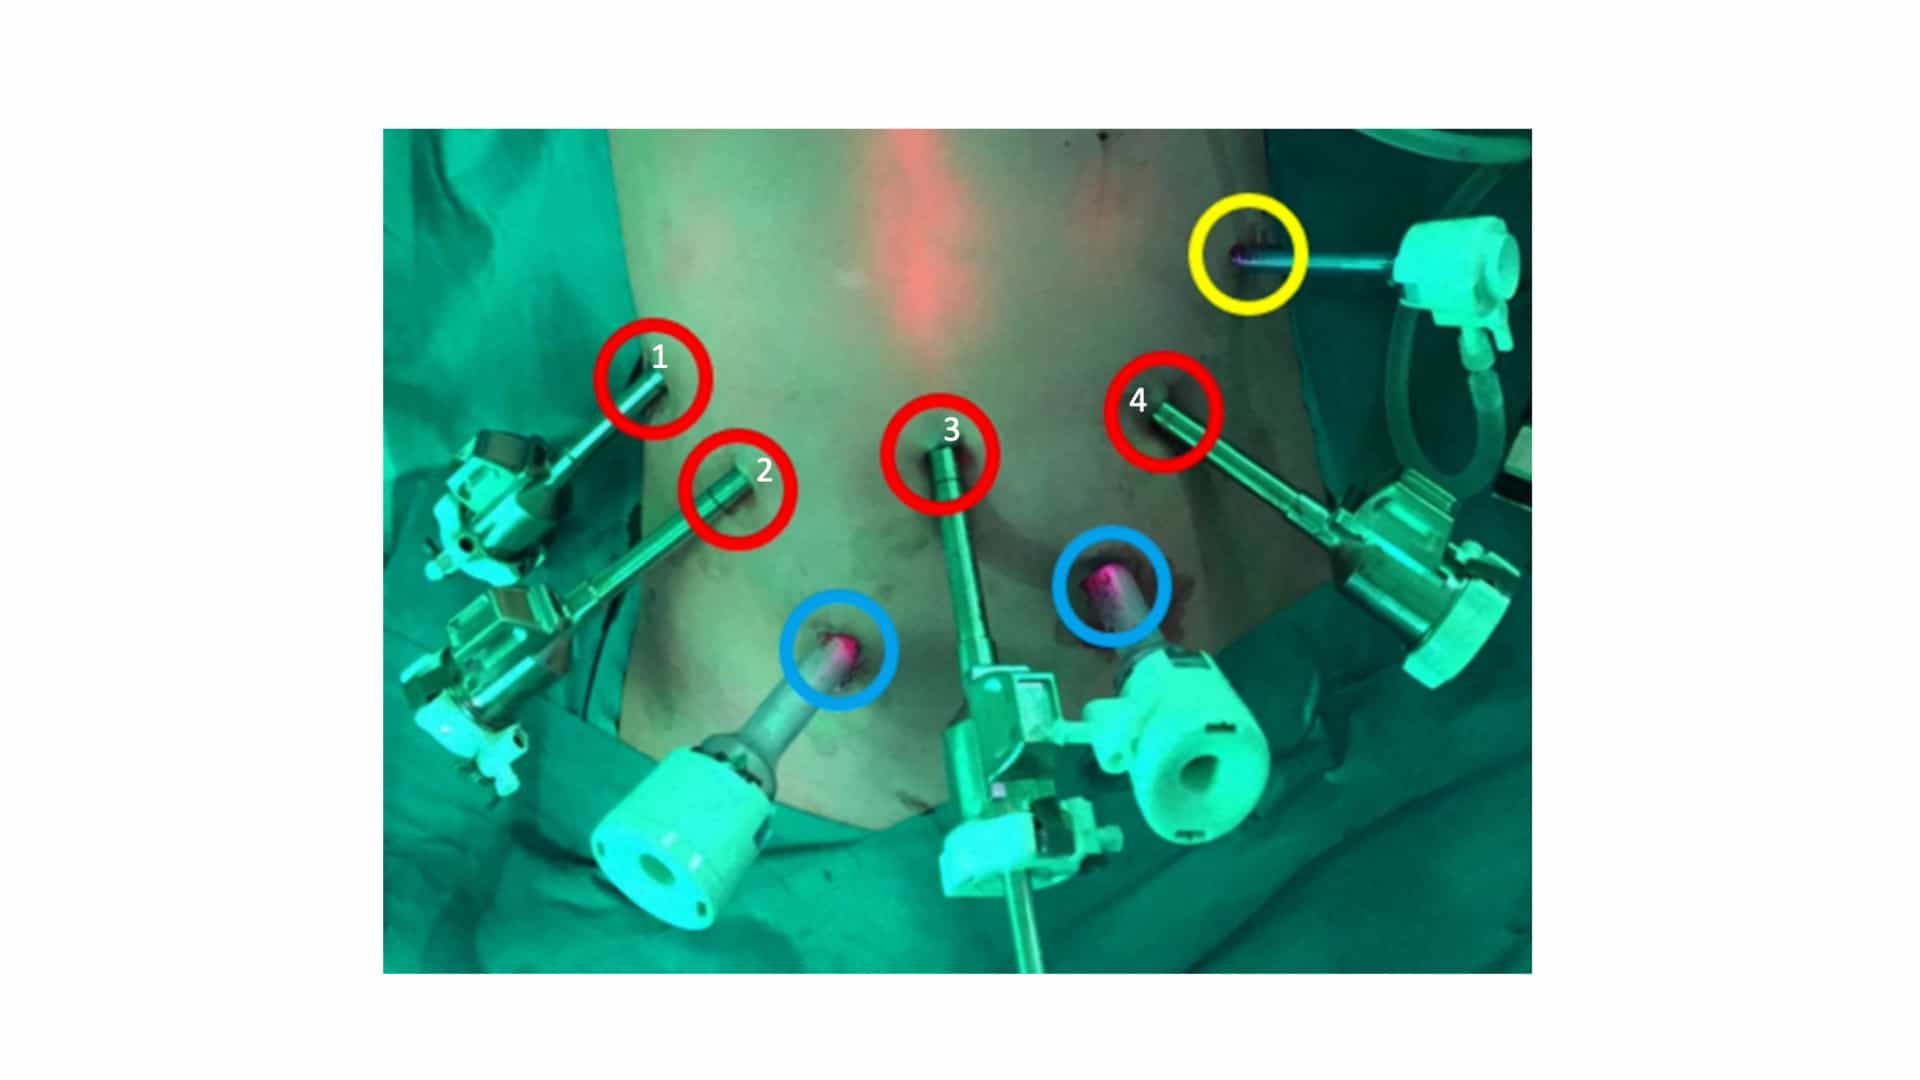
Robot-assisted Total Mesorectal Excision and Lateral Pelvic Lymph Node Dissection for Locally Advanced Middle-low Rectal Cancer
Published on: February 12, 2022
Laparoscopic diverticulectomy or laparoscopic-assisted resection of symptomatic Meckel diverticulum in children? A
E P Redman1, P R Mishra1, M D Stringer2,3
1Department of Paediatric Surgery, Level 3 CSB, Wellington Children's Hospital, Riddiford St, Newtown, Wellington, 6021, New Zealand.

Abstract:
Recent reports have recommended laparoscopic diverticulectomy for symptomatic Meckel diverticulum (MD) rather than laparoscopic-assisted extracorporeal resection. This technique may risk leaving residual ectopic mucosa leading to complications. This systematic review attempts to quantify the relative risks of both approaches. A systematic review was conducted according to PRISMA guidelines. Articles were eligible for inclusion if they reported data on the laparoscopic management of symptomatic MD in children. Eleven reports were identified, all of which were institutional retrospective studies. Pooled outcome data on 248 children showed no statistically significant difference in complications between laparoscopic diverticulectomy (n = 133) and laparoscopic-assisted segmental resection (n = 115) (3% vs. 6.1%, p = 0.39). One patient from the diverticulectomy group re-presented with recurrent bleeding necessitating segmental small bowel resection. Conclusions are limited by the number of patients and variable follow up. Short, wide MD with a height:base ratio of < 2; diverticula with thickening or ischemia at the base and those complicated by volvulus or small bowel obstruction are probably best treated by laparoscopic-assisted extracorporeal resection. For other symptomatic diverticula laparoscopic diverticulectomy is a reasonable approach with a less than 1% risk of leaving residual ectopic gastric mucosa.
Insights
Laparoscopic diverticulectomy and laparoscopic-assisted resection for symptomatic Meckel diverticulum (MD) show similar complication rates in children. Laparoscopic diverticulectomy is reasonable for most cases, while complex MD may benefit from extracorporeal resection.
Area of Science:
- Pediatric Surgery
- Gastrointestinal Surgery
- Minimally Invasive Surgery
Background:
- Symptomatic Meckel diverticulum (MD) management is evolving, with recent recommendations favoring laparoscopic diverticulectomy over laparoscopic-assisted extracorporeal resection.
- Concerns exist regarding potential residual ectopic mucosa and subsequent complications with laparoscopic diverticulectomy.
Purpose of the Study:
- To systematically review and quantify the relative risks of laparoscopic diverticulectomy versus laparoscopic-assisted extracorporeal resection for symptomatic Meckel diverticulum in children.
- To compare complication rates and identify optimal surgical approaches based on Meckel diverticulum characteristics.
Main Methods:
- A systematic review was conducted following PRISMA guidelines.
- Included studies reported on the laparoscopic management of symptomatic Meckel diverticulum in pediatric patients.
- Pooled outcome data from eleven retrospective institutional studies involving 248 children were analyzed.
Main Results:
- No statistically significant difference in overall complications was found between laparoscopic diverticulectomy (3%) and laparoscopic-assisted segmental resection (6.1%) (p=0.39).
- One patient in the diverticulectomy group experienced recurrent bleeding requiring further surgery.
- The risk of residual ectopic gastric mucosa with laparoscopic diverticulectomy was less than 1% for uncomplicated cases.
Conclusions:
- Laparoscopic diverticulectomy is a viable option for most symptomatic Meckel diverticula in children.
- Laparoscopic-assisted extracorporeal resection may be preferable for short, wide Meckel diverticula (height:base ratio <2), those with base thickening/ischemia, or complicated by volvulus/obstruction.