Related Experiment Video
Updated: Dec 20, 2025

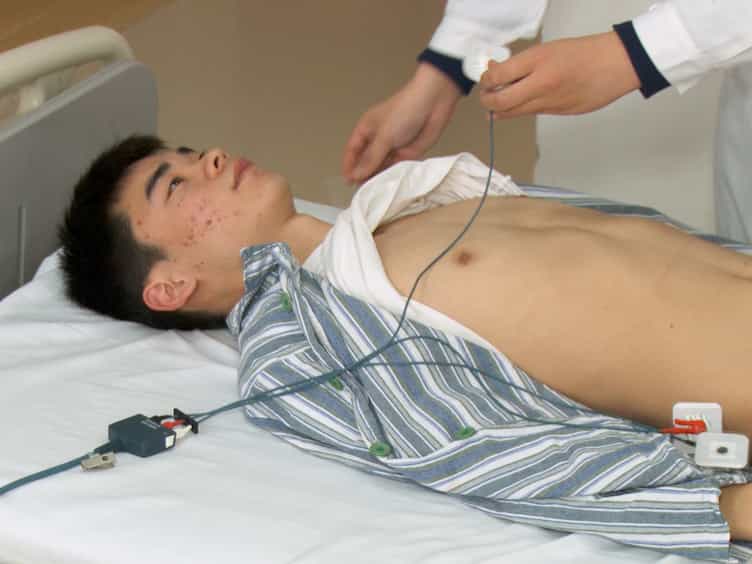
Assessment of Vascular Function in Patients With Chronic Kidney Disease
Published on: June 16, 2014
Arterial stiffness and kidney disease progression in the systolic blood pressure intervention trial

Insights
Higher baseline pulse pressure (PP) is linked to faster kidney disease progression in older adults, particularly those without chronic kidney disease (CKD). This finding highlights PP as a key indicator for monitoring kidney health in at-risk populations.
Area of Science:
- Nephrology
- Cardiovascular Medicine
- Geriatrics
Background:
- Arterial stiffness, a marker of cardiovascular and kidney health, increases with age and in chronic kidney disease (CKD).
- The relationship between arterial stiffness and kidney function decline is not fully understood, necessitating further investigation.
- Pulse pressure (PP) and carotid-femoral pulse-wave velocity (CFPWV) are key indicators of arterial stiffness.
Purpose of the Study:
- To investigate the independent association between baseline arterial stiffness (measured by PP and CFPWV) and kidney disease progression.
- To determine if arterial stiffness predicts kidney function decline in participants of the Systolic Blood Pressure Intervention Trial (SPRINT).
Main Methods:
- Analysis included 8,815 SPRINT participants for PP and 592 for CFPWV.
- Cox proportional hazards analysis assessed the association between PP and kidney disease progression endpoints.
- Mixed models examined the relationship between baseline PP/CFPWV and estimated glomerular filtration rate (eGFR) changes.
Main Results:
- Higher baseline PP (≥ median) was significantly associated with an increased hazard of kidney disease progression (HR: 1.93).
- This association was significant in individuals without baseline CKD (HR: 2.05) but not in those with baseline CKD (HR: 1.28).
- Higher baseline PP was strongly associated with eGFR decline (p < 0.0001), while baseline CFPWV was not.
Conclusions:
- Baseline pulse pressure is an independent predictor of kidney disease progression in older adults at high cardiovascular risk.
- The association between PP and kidney disease progression is more pronounced in individuals without pre-existing CKD.
- Pulse pressure may serve as a valuable clinical marker for identifying individuals at risk of kidney function decline.
Aims:
Arterial stiffness increases with both advancing age and chronic kidney disease (CKD) and may contribute to kidney function decline, but evidence is inconsistent. We hypothesized that greater baseline arterial stiffness (assessed as pulse pressure (PP) and carotid-femoral pulse-wave velocity CFPWV)) was independently associated with kidney disease progression over the follow-up period (3.8 years) in the Systolic Blood Pressure Intervention Trial (SPRINT).
Materials And Methods:
8,815 SPRINT participants were included in the analysis of PP. 592 adults who participated in a SPRINT ancillary study that measured CFPWV were included in subgroup analyses. Cox proportional hazards analysis was used to examine the association between PP and time to kidney disease progression endpoints: (A) incident estimated glomerular filtration rate (eGFR) < 60 mL/min/1.73m2 in non-CKD participants at baseline; (B) 50% decline in eGFR, initiation of dialysis, or transplant in those with baseline CKD. Mixed model analyses examined the association of baseline PP/CFPWV with follow-up eGFR.
Results And Conclusion:
Mean ± SD age was 68 ± 10 years, baseline PP was 62 ± 14 mmHg, and CFPWV was 10.8 ± 2.7 m/s. In the fully adjusted model, PP ≥ median was associated with an increased hazard of kidney disease progression endpoints (HR: 1.93 (1.43 - 2.61)). The association remained significant in individuals without (2.05 (1.47 - 2.87)) but not with baseline CKD (1.28 (0.55 - 2.65)). In fully adjusted models, higher baseline PP associated with eGFR decline (p < 0.0001 (all, CKD, non-CKD)), but baseline CFPWV did not. Among older adults at high risk for cardiovascular events, baseline PP was associated with kidney disease progression.
Related Concept Videos
 01:18
Hypertension and Regulation of Blood Pressure
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:30
Antihypertensive Drugs: Angiotensin-Converting Enzyme Inhibitors
 01:30
Hypertension III: Clinical Manifestations and Diagnostic Studies
 01:25
Antihypertensive Drugs: Direct Renin Inhibitors
 01:29
Hypertension II: Pathophysiology