Arthroscopic coronal plane syndesmotic instability has been over-diagnosed
Related Experiment Video
Updated: Dec 20, 2025

Author Spotlight: Double Posteromedial Approach for Treating Posterior Cruciate Ligament Cysts
Published on: October 20, 2023
Noortje C Hagemeijer1,2,3,4, Mohamed Abdelaziz Elghazy5,6, Gregory Waryasz5,7
1Foot and Ankle Research and Innovation Lab, Department of Orthopaedic Surgery, Massachusetts General Hospital, Harvard Medical School, Boston, USA. nchagemeijer@gmail.com.

Purpose:
Ankle arthroscopy is widely used for diagnosis of syndesmotic instability, especially in subtle cases. To date, no published article has systematically reviewed the literature in aggregate to understand which instability values should be used intraoperatively. The primary aim was to systematically review the amount of tibiofibular displacement that correlates with syndesmotic instability after a high ankle sprain. A secondary aim is to assess the quality of such research.
Methods:
Systematic searches of EMBASE (Ovid) and MEDLINE via PubMed, CINAHL, Web of Science, and Google Scholar were used.
Inclusion Criteria:
studies that arthroscopically evaluated the fibular displacement at various stages of syndesmotic ligament injury. Two reviewers independently extracted data and assessed methodological quality using the Anatomical Quality Assessment (AQUA) Tool and methodological index for non-randomized studies (MINORS).
Results:
Eight cadaveric studies and three clinical studies were included for review. All studies reported displacement in the coronal plane, four studies reported in the sagittal plane, and one reported findings in the rotational plane. Four cadaveric studies had a similar experimental set up and the weighted mean associated with instability in the coronal plane could be calculated and was 2.9 mm at the anterior portion of the distal tibiofibular joint and 3.4 mm at the posterior portion. Syndesmotic instability in the sagittal plane is less extensively studied, however available data from a cadaveric study suggests thresholds of 2.2 mm of posterior fibular translation when performing an anterior to posterior hook test and 2.6 mm of anterior fibular translation when performing a posterior to anterior hook test.
Conclusions:
The results have concluded that the commonly used 2.0 mm threshold value of distal tibiofibular diastasis may lead to overtreatment of syndesmotic instability, and that using threshold values of 2.9 mm measured at the anterior portion of the incisura and 3.4 mm at the posterior portion may represent better cut off values. Given the ready availability of 3 mm probes among standard arthroscopic instrumentation, at the very least surgeons should use 3 mm in lieu of 2 mm probes intraoperatively.
Level Of Evidence:
IV.

Related Concept Videos
 01:23
Knee Joint
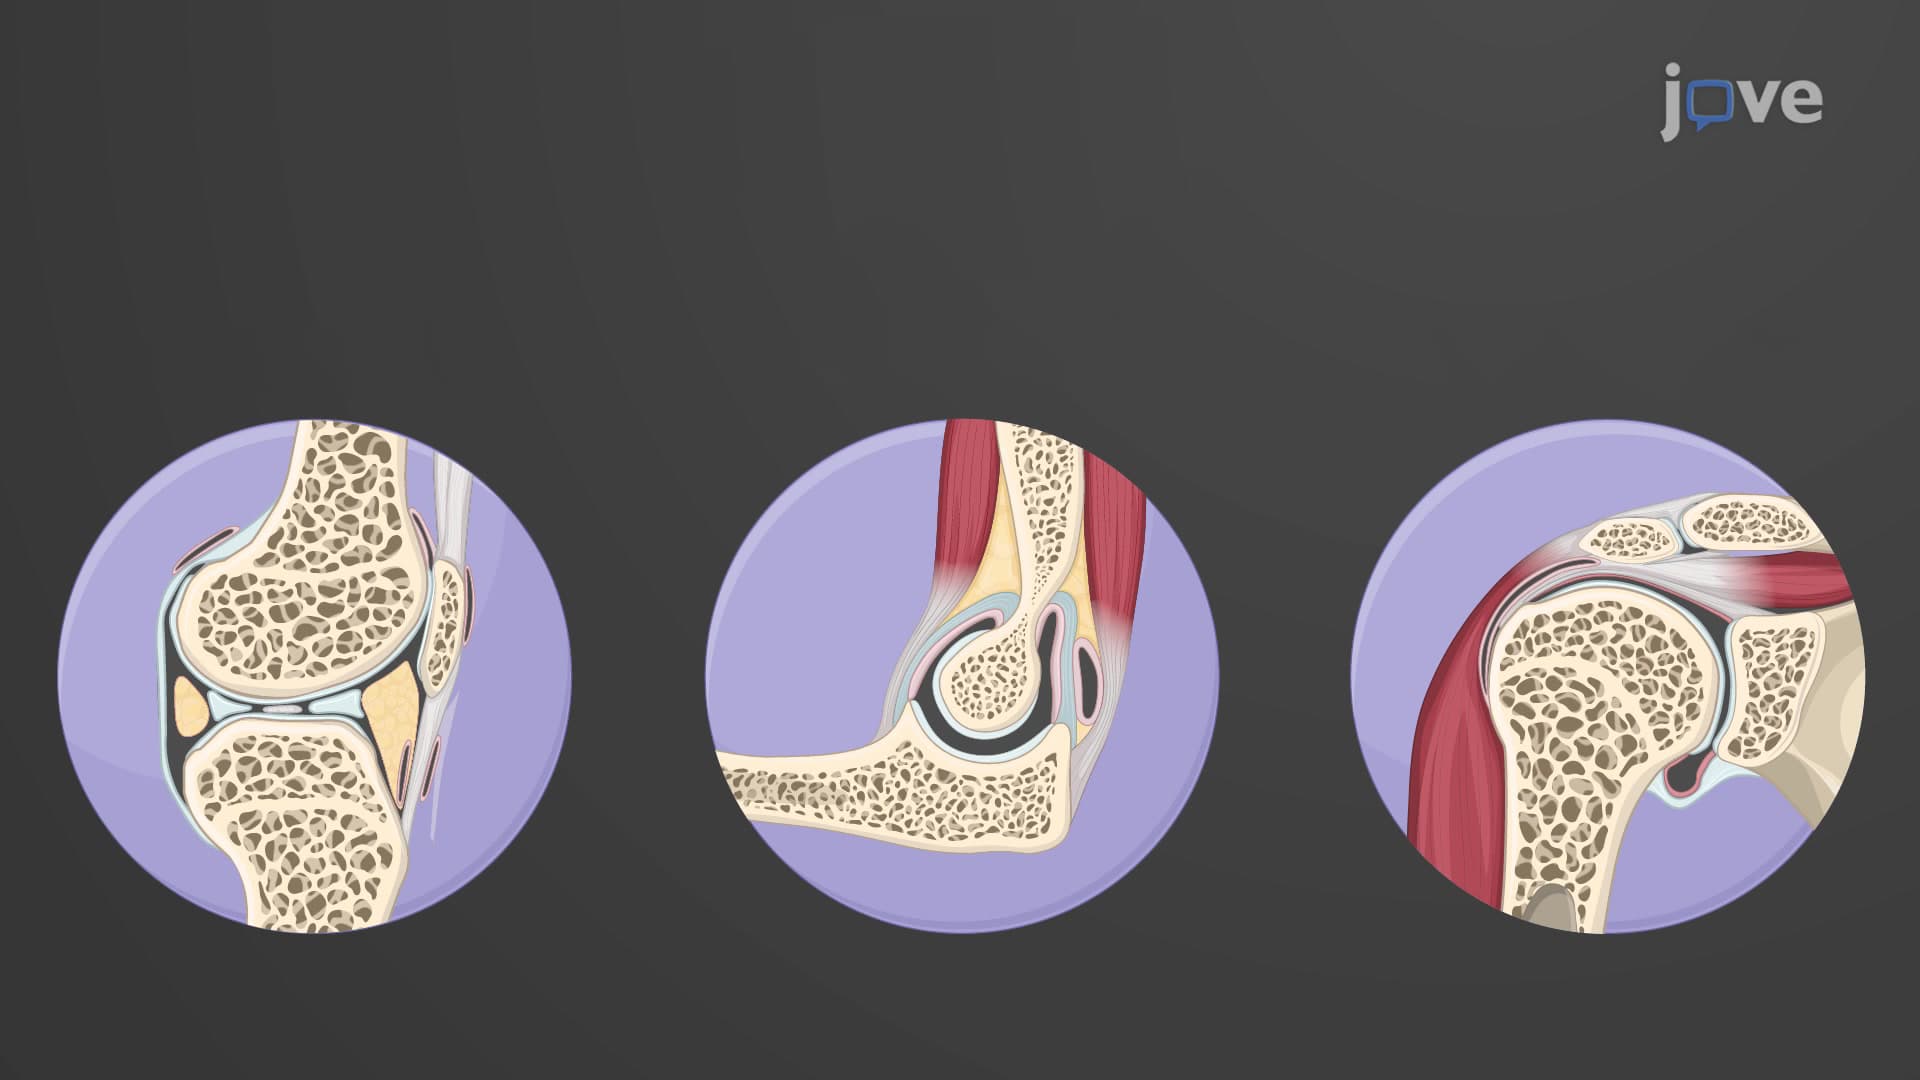
A total of seven ligaments support the knee joint. The patellar ligament, which is also attached to the quadriceps femoris...
 01:09
Functional Classification of Joints
The functional classification of joints is determined by the amount of mobility between the adjacent bones. Joints are functionally classified as a synarthrosis or immobile joint, an amphiarthrosis or slightly moveable joint, or as a diarthrosis, a freely moveable joint. Fibrous and cartilaginous joints can be functionally classified as either synarthroses or amphiarthroses, whereas all synovial joints are classified as diarthroses.
Synarthrosis
An...