Related Experiment Video
Updated: Dec 20, 2025
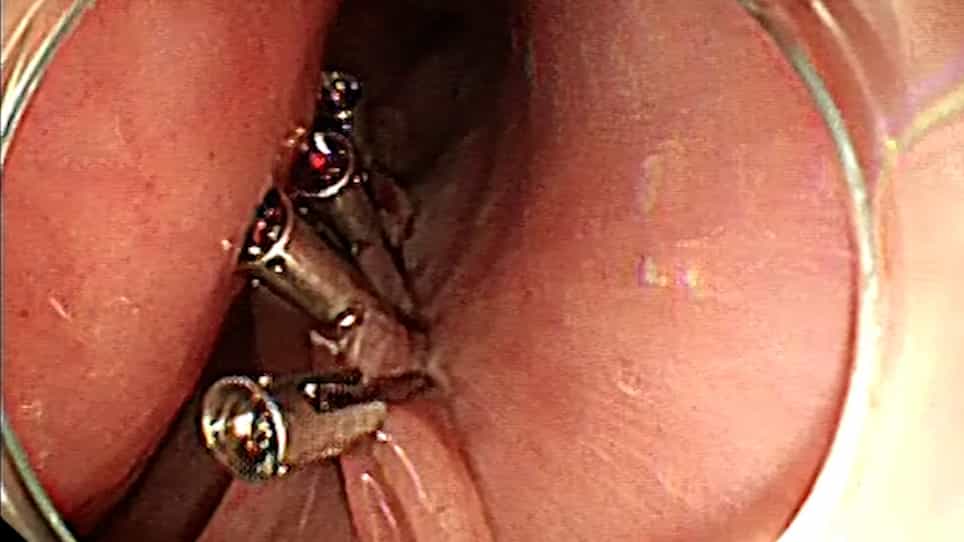

Use of the Scissor-Type Knife During the Peroral Endoscopy Myotomy Procedure for the Treatment of Achalasia
Published on: March 3, 2023
Differences in clinical characteristics between conservative-treatment-response group and refractory
Noriyuki Kawami1, Shintaro Hoshino2, Yoshimasa Hoshikawa2
1Department of Gastroenterology, Nippon Medical School, Graduate School of Medicine, 1-1-5, Sendagi, Bunkyo-ku, Tokyo, 113-8603, Japan. s5038@nms.ac.jp.

Background:
Jackhammer esophagus (JE) is a rare disease with unclear clinical features. The objective of this study was to retrospectively compare the clinical characteristics of patients with JE whose symptoms were controlled with conservative treatment, such as observation or medication, versus those who were required surgical treatment, such as surgical myotomy or per oral endoscopic myotomy.
Methods:
Eighteen patients with JE were included in this study. The patients were divided into two groups: patients who responded to conservative treatment (C group) and patients who were refractory to conservative treatment and underwent surgery (S group). Patient age, sex, disease duration before treatment, symptoms, esophagogastroduodenoscopic (EGD) findings, esophagographic findings, esophageal wall thickness on computed tomography, number of swallows with hypercontractile peristalsis in 10 water swallows, and maximum distal contractile integral (DCI) were compared between the groups.
Results:
Thirteen of 18 patients (72%) were in the C group and five of 18 (28%) were in the S group. There were no significant differences in age, sex, disease duration before treatment, symptoms, EGD findings, esophagographic findings, esophageal wall thickness, or number of swallows with hypercontractile peristalsis between the groups. On Starlet high-resolution manometry, the median maximum DCI value was significantly higher in the S group (32,651 mmHg-s-cm) than in the C group (17,926 mmHg-s-cm) (P = 0.0136).
Conclusions:
JE treatment should be carefully considered because some patients require surgery, whereas others are controlled with conservative treatment alone. A higher DCI value in patients with JE may predict resistance to conservative treatment.


Related Concept Videos
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure...
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...