Related Experiment Video
Updated: Dec 20, 2025


Manufacturing Abdominal Aorta Hydrogel Tissue-Mimicking Phantoms for Ultrasound Elastography Validation
Published on: September 19, 2018
Increased hospital volume is associated with reduced mortality after thoracoabdominal aortic aneurysm repair
Antonio R Polanco1, Alex M D'Angelo1, Nicholas J Shea1
1Columbia University Aortic Surgery Center, New York, NY.

Objective:
Contemporary data on outcomes in open thoracoabdominal aortic aneurysm (TAAA) repair are limited to reports from major aortic referral centers showing excellent outcomes. This study aimed to characterize the national experience of open TAAA repair using national outcomes data, with a primary focus on the association of hospital volume with mortality and morbidity.
Methods:
The Nationwide Inpatient Sample was queried from 1998 to 2011, and all patients with a diagnosis of TAAA who underwent open operative repair were included. These patients were further stratified into tertiles based on the operative volume of the institution that performed the operation: low volume (LV), <3 cases/y; medium volume (MV), 3 to 11 cases/y; and high volume (HV), ≥12 cases/y. Baseline demographics as well as perioperative outcomes were compared between these groups. Multivariable logistic regression was performed to determine predictors of operative mortality and morbidity. Subgroup analyses were performed for patients presenting for elective surgery and for those presenting for urgent and emergent surgery.
Results:
Overall operative mortality was 21% for the entire cohort. Operative mortality was higher at LV (26%) and MV (21%) centers compared with HV centers (15%; P < .001). This difference was similar in both elective surgery (LV, 18%; MV, 14%; HV, 12%; P < .001) and urgent and emergent surgery (LV, 34%; MV, 30%; HV, 19%; P < .001). Furthermore, rates of blood transfusion and acute renal failure were significantly lower in the HV group. Multivariable analysis revealed that compared with the HV group, patients operated on at LV centers (odds ratio [OR], 1.9, 95% confidence interval [CI], 1.7-2.1; P < .001) and MV centers (OR, 1.5; 95% CI, 1.4-1.7; P < .001) had at least 1.5 times the odds of in-hospital mortality. The HV group also had significantly lower odds of dying in the subgroup analyses of both elective surgery and urgent and emergent surgery. Increasing TAAA volume was associated with increased use of distal aortic perfusion (OR, 1.03; 95% CI, 1.02-1.03; P < .001).
Conclusions:
Patients with TAAA in the United States operated on at HV centers have significantly lower mortality and morbidity compared with patients operated on at lower volume centers. Consideration of referral to HV centers may be warranted, but further research is required to justify this conclusion.
More Related Videos
 08:50
Technique and Patient Selection Criteria of Right Anterior Mini-Thoracotomy for Minimal Access Aortic Valve Replacement
Published on: March 26, 2018
 06:50
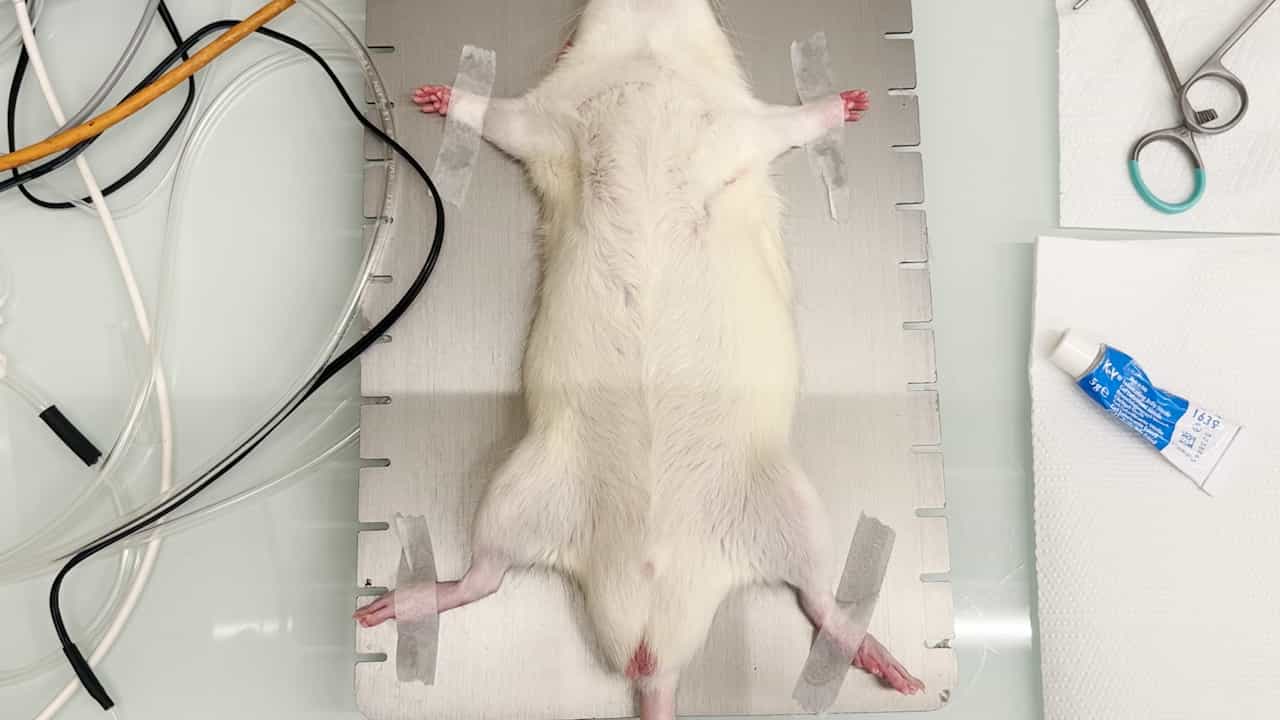
A Model of Acute Lung Injury Following Visceral Ischemia-Reperfusion by Supra-Coeliac Aortic Cross Clamping in Rats
Published on: August 15, 2025
Related Concept Videos
 01:26
Aneurysm III: Interprofessional Care
 01:22
Aneurysm IV: Nursing Management
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies
 01:25
Aortic Regurgitation III: Medical Management
 01:17
Aortic Regurgitation IV: Nursing Management
 01:15
Aortic Regurgitation I: Introduction