Related Experiment Video
Updated: Dec 20, 2025

Laparoscopic Duodenum-Preserving Pancreatic Head Resection via Inferior Infracolic Approach: A Surgical Approach for Benign Lesions
Published on: February 9, 2024
Vascular Anatomy of Mesopancreas in Pancreatoduodenectomy Using an Intestinal Derotation Procedure
Masanori Sugiyama1,2, Yutaka Suzuki3, Tetsuya Nakazato3
1Department of Surgery, Kyorin University School of Medicine, 6-20-2 Shinkawa, Mitaka, Tokyo, 181-8611, Japan. sgym@ks.kyorin-u.ac.jp.

Background:
Mesopancreas excision in pancreatoduodenectomy is technically complicated because of the anatomical complexity of the mesopancreas with the inferior peripancreatic blood vessels which is caused by intestinal rotation in fetal life. We have developed a novel artery-first approach (the intestinal derotation procedure) for facilitating mesopancreas excision. The aim of this study was to clarify the vascular anatomy of the mesopancreas after derotation.
Methods:
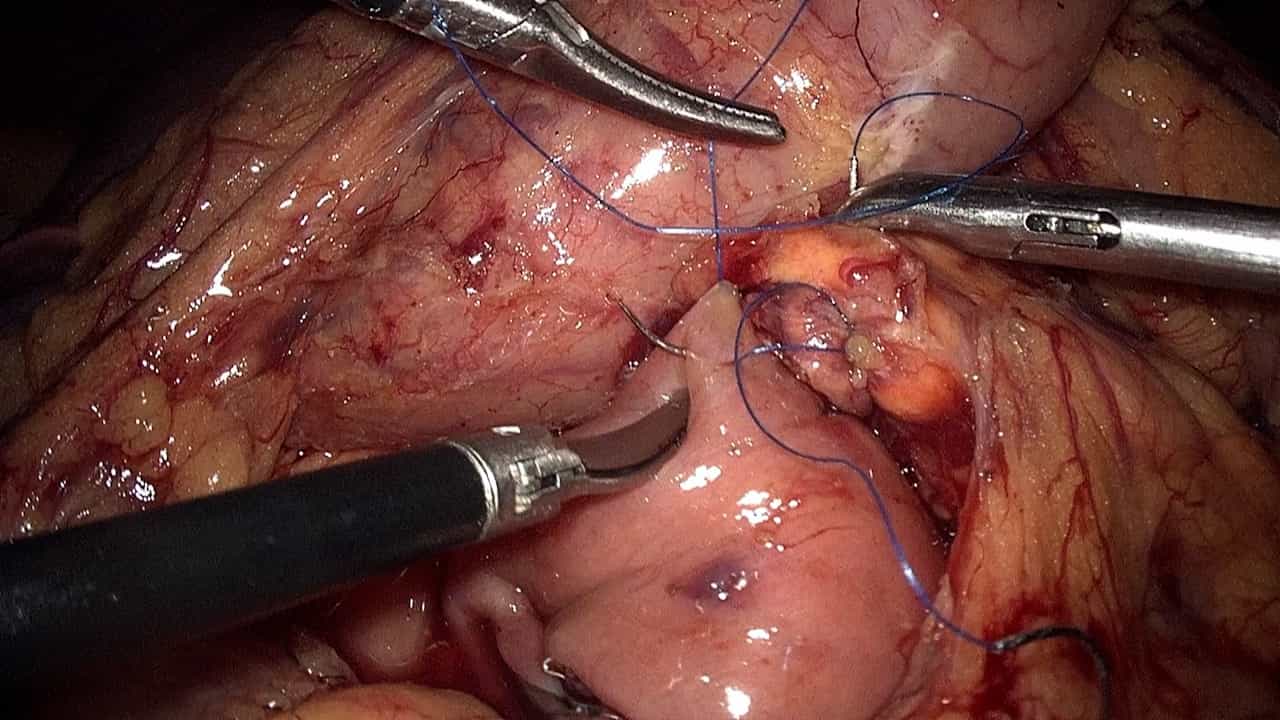
The right-sided colon and small intestine are mobilized from the retroperitoneum, and the intestinal loop is then derotated. In 136 cases of pancreatoduodenectomy employing the derotation procedure, we analyzed the vascular anatomy of the mesopancreas.
Results:
After derotation, the anatomy was simplified. The mesopancreas extended from the right aspect of the superior mesenteric artery (SMA), forming a horizontal plane. The first jejunal trunk (FJT) was situated in parallel with the second jejunal artery and was anterior (91%) or posterior (9%) to the SMA. The inferior pancreaticoduodenal vein (IPDV) entered the right side of the FJT (83%) or the superior mesenteric vein (17%). Besides the IPDV, 1-4 tributaries entered the right wall of the FJT, in 89% of cases. The inferior pancreaticoduodenal artery was observed to originate from the right wall of the SMA, sharing a common stem with the first jejunal artery (70%) or branching directly from the SMA (29%).
Conclusions:
Intestinal derotation simplifies the mesopancreas anatomy and reveals the anatomical details of the inferior peripancreatic blood vessels in pancreatoduodenectomy.
Insights
Intestinal derotation simplifies complex mesopancreas anatomy for pancreatoduodenectomy. This artery-first approach clarifies inferior peripancreatic blood vessel details, aiding surgical procedures.
Area of Science:
- Surgical Anatomy
- Vascular Surgery
- Gastrointestinal Surgery
Background:
- Mesopancreas excision during pancreatoduodenectomy is challenging due to complex anatomy and inferior peripancreatic vessels.
- Fetal intestinal rotation causes this anatomical complexity.
- A novel artery-first approach, the intestinal derotation procedure, was developed to simplify mesopancreas excision.
Purpose of the Study:
- To clarify the vascular anatomy of the mesopancreas after intestinal derotation.
- To evaluate the utility of the intestinal derotation procedure in pancreatoduodenectomy.
Main Methods:
- The study analyzed vascular anatomy in 136 pancreatoduodenectomy cases using the intestinal derotation procedure.
- The procedure involves mobilizing and derotating the right-sided colon and small intestine from the retroperitoneum.
Main Results:
- Derotation simplified mesopancreas anatomy, revealing a horizontal plane extending from the superior mesenteric artery (SMA).
- Detailed vascular relationships were identified, including the first jejunal trunk (FJT) and inferior pancreaticoduodenal vein (IPDV) positioning relative to the SMA.
- The origin of the inferior pancreaticoduodenal artery from the SMA was also characterized.
Conclusions:
- Intestinal derotation effectively simplifies mesopancreas anatomy.
- This approach enhances visualization of inferior peripancreatic blood vessels, crucial for pancreatoduodenectomy.
- The derotation procedure facilitates safer and more precise surgical interventions.