Related Experiment Video
Updated: Dec 20, 2025
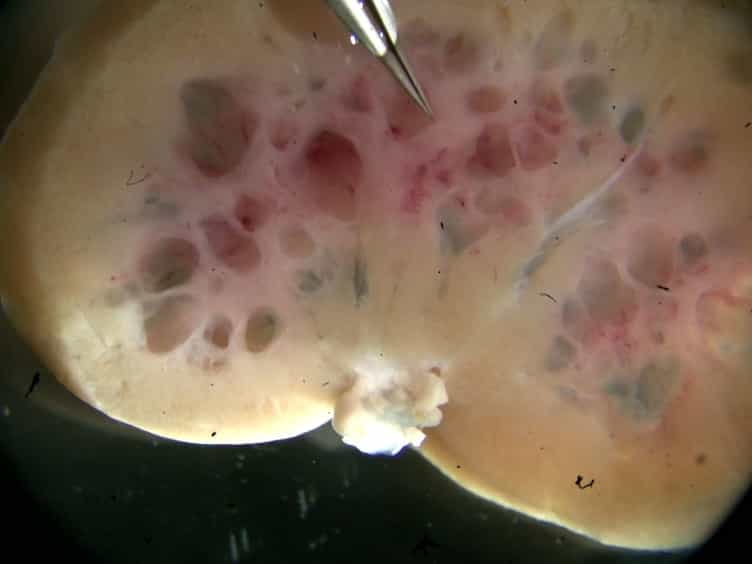

Implementing Patch Clamp and Live Fluorescence Microscopy to Monitor Functional Properties of Freshly Isolated PKD Epithelium
Published on: September 1, 2015
Cilia and polycystic kidney disease
1School of Life Sciences, Southwest University, Beibei, Chongqing, 400715, China.

Insights
Polycystic kidney disease (PKD) involves cyst formation due to genetic mutations affecting cilia. Understanding these genetic causes and cellular mechanisms is key to developing new treatments for ADPKD and ARPKD.
Area of Science:
- Genetics
- Cell Biology
- Nephrology
Background:
- Polycystic kidney disease (PKD), including ADPKD and ARPKD, is a leading genetic cause of kidney and liver disease.
- ADPKD stems from mutations in PKD1 (PC1) or PKD2 (PC2), while ARPKD is mainly caused by PKHD1 (FPC) or DZIP1L mutations.
- These proteins (PC1/2, FPC, DZIP1L) are localized to cilia and basal bodies, suggesting a role for these structures in PKD pathogenesis.
Purpose of the Study:
- To review genetic studies on polycystin (PC1/2) and cilia function in ADPKD.
- To discuss the regulation of polycystin biogenesis and cilia trafficking.
- To explore genetic interactions and tissue patterning roles of FPC and DZIP1L in ARPKD.
Main Methods:
- Genetic analysis of PKD-related genes (PKD1, PKD2, PKHD1, DZIP1L).
- Biochemical studies on protein localization and function within cilia and basal bodies.
- Comparative analysis of disease mechanisms in ADPKD and ARPKD.
Main Results:
- Genetic studies reveal PC1/2 and FPC as signaling molecules involved in cilia function and renal tubule morphology.
- DZIP1L mutations impair PC1/2 cilia expression, while FPC deficiency has distinct effects, indicating divergent ARPKD mechanisms.
- Synergistic genetic interactions between Pkd1 and Pkhd1, and unique tissue patterning by FPC, were identified.
Conclusions:
- Cilia play a critical role in preventing cyst formation in PKD.
- Divergent molecular mechanisms underlie cystogenesis in ADPKD and ARPKD.
- Further research into PKD genetics and cilia biology offers therapeutic intervention strategies.
Abstract:
Polycystic kidney disease (PKD), comprising autosomal dominant polycystic kidney disease (ADPKD) and autosomal recessive polycystic kidney disease (ARPKD), is characterized by incessant cyst formation in the kidney and liver. ADPKD and ARPKD represent the leading genetic causes of renal disease in adults and children, respectively. ADPKD is caused by mutations in PKD1 encoding polycystin1 (PC1) and PKD2 encoding polycystin 2 (PC2). PC1/2 are multi-pass transmembrane proteins that form a complex localized in the primary cilium. Predominant ARPKD cases are caused by mutations in polycystic kidney and hepatic disease 1 (PKHD1) gene that encodes the Fibrocystin/Polyductin (FPC) protein, whereas a small subset of cases are caused by mutations in DAZ interacting zinc finger protein 1 like (DZIP1L) gene. FPC is a type I transmembrane protein, localizing to the cilium and basal body, in addition to other compartments, and DZIP1L encodes a transition zone/basal body protein. Apparently, PC1/2 and FPC are signaling molecules, while the mechanism that cilia employ to govern renal tubule morphology and prevent cyst formation is unclear. Nonetheless, recent genetic and biochemical studies offer a glimpse of putative physiological malfunctions and the pathomechanisms underlying both disease entities. In this review, I summarize the results of genetic studies that deduced the function of PC1/2 on cilia and of cilia themselves in cyst formation in ADPKD, and I discuss studies regarding regulation of polycystin biogenesis and cilia trafficking. I also summarize the synergistic genetic interactions between Pkd1 and Pkhd1, and the unique tissue patterning event controlled by FPC, but not PC1. Interestingly, while DZIP1L mutations generate compromised PC1/2 cilia expression, FPC deficiency does not affect PC1/2 biogenesis and ciliary localization, indicating that divergent mechanisms could lead to cyst formation in ARPKD. I conclude by outlining promising areas for future PKD research and highlight rationales for potential therapeutic interventions for PKD treatment.


Related Concept Videos
 01:10
Nephrons
 01:20
Renal Corpuscle
Glomerulus: Structure and Function
The glomerulus is a tiny, intricate network of capillaries located at the beginning of the nephron. It's enveloped by the Bowman's capsule and receives its blood supply from an afferent arteriole, which divides into numerous...
 01:25
Chronic Kidney Disease I: Introduction
 01:22
Microtubules in Signaling
 01:23
Cystic Fibrosis: Pathogenesis
CF is primarily caused by a genetic mutation in a chromosome 7 gene coding for the cystic fibrosis transmembrane conductance regulator (CFTR) protein. The most common gene mutation leading to CF is the ΔF508 mutation,...
 01:24
Renal Tubule and Collecting Duct
Proximal Convoluted Tubule (PCT):
The PCT is the initial segment of the renal tubule, extending from the Bowman's capsule that encloses the glomerulus. Its convoluted structure and microvilli-lined cells increase the surface area for reabsorption. The PCT reabsorbs glucose, amino acids, sodium, and water from the filtrate, ensuring essential...