Related Experiment Video
Updated: Dec 19, 2025
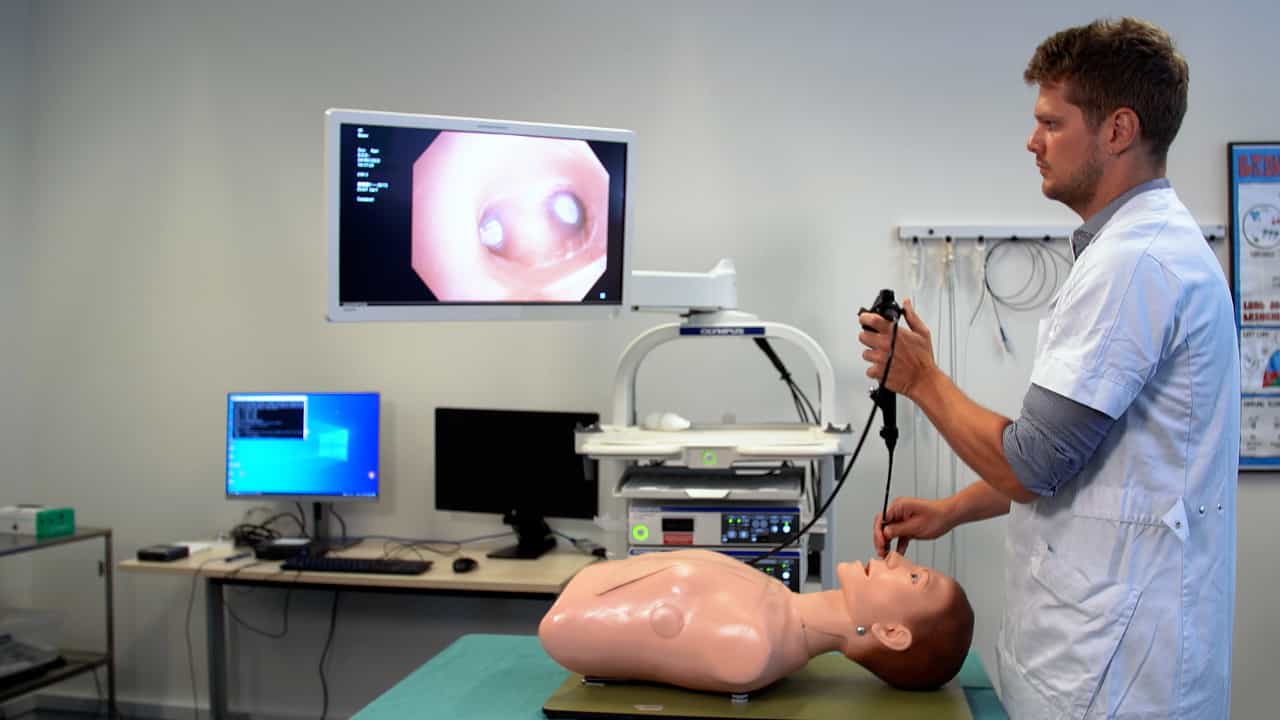

Author Spotlight: Learning Systematic Bronchoscopy in a Simulation-Base Setting
Published on: June 23, 2023
"We Just Never Have Enough Time". Clinician Views of Lung Cancer Screening Processes and Implementation
Anne C Melzer1,2, Sara E Golden3, Sarah S Ono3,4
1Center for Care Delivery and Outcomes Research, Minneapolis Veterans Affairs Health Care System, Minneapolis, Minnesota.

Abstract:
Rationale: Despite a known mortality benefit, lung cancer screening (LCS) implementation has been unexpectedly slow. New programs face barriers to implementation, which may include lack of clinician engagement or beliefs that the intervention is not beneficial.Objectives: To evaluate diverse clinician perspectives on their views of LCS and their experience with LCS implementation and processes.Methods: We performed a qualitative study of clinicians participating in LCS. Clinicians were drawn from three medical centers and represented diverse specialties and practice settings. All participants practiced at sites with formal LCS programs. We performed semistructured interviews with probes designed to elicit opinions of LCS, perceived evidence gaps, and recommendations for improvements. Transcribed interviews were iteratively reviewed and coded using directed content analysis.Results: Participants (N = 24) included LCS coordinators, pulmonologists, physician and nonphysician primary care providers (PCPs), a surgeon, and a radiologist. Most clinicians expressed their belief that the evidence supporting LCS was adequate to support clinical adoption, though most PCPs had little direct knowledge and based their decisions on local recommendations or endorsement by the U.S. Preventive Services Task Force. Many PCPs endorsed lack of knowledge of eligibility requirements and screening strategy (e.g., annual while eligible). Clinicians with more LCS knowledge, including several PCPs, identified a number of gaps in the current evidence that tempered enthusiasm, including unclear ideal screening interval, populations with high cancer risk that do not qualify under the U.S. Preventive Services Task Force guidelines, indications to stop screening, and the role of serious comorbidities. Support for centralized programs and LCS coordinators was strong but not uniform. Clinicians were frustrated by time limitations during a patient encounter, costs to the patient, and issues with insurance coverage. Many gaps in informatics support were identified. Clinicians recommended working to improve informatics support, continuing to clarify clinician responsibilities, and working on increasing public awareness of LCS.Conclusions: Despite working within programs that have adopted many recommended care processes to support LCS, clinicians identified a number of issues in providing high-quality LCS. Many of these issues are best addressed by improved support of LCS within the electronic health record and continued education of staff and patients.


Related Concept Videos
 01:30
Endoscopic Studies I: Bronchoscopy and Thoracoscopy
Bronchoscopy
Description
Bronchoscopy is a procedure that involves direct visualization of the larynx, trachea, and bronchi for diagnostic and therapeutic purposes. A flexible fiber optic or rigid bronchoscope is used to carry out the procedure. The fiber-optic bronchoscope is more frequently used due...
 01:13
Radiological Investigation III: Pulmonary Angiogram and PET Scan
Pulmonary Angiogram
A Pulmonary Angiogram is an invasive procedure involving injecting a contrast medium through a catheter threaded into the pulmonary artery or the right side of the heart to visualize the pulmonary vasculature. Computed Tomography (CT) scans have mainly replaced this...
 01:27
Nursing Ethical Principles II
Consider the following scenario, which illustrates how these principles are applied in the care of Mr. John, a fifty-year-old teacher diagnosed with metastatic liver cancer.
Initially, Mr. John's...