Related Experiment Video
Updated: Dec 18, 2025
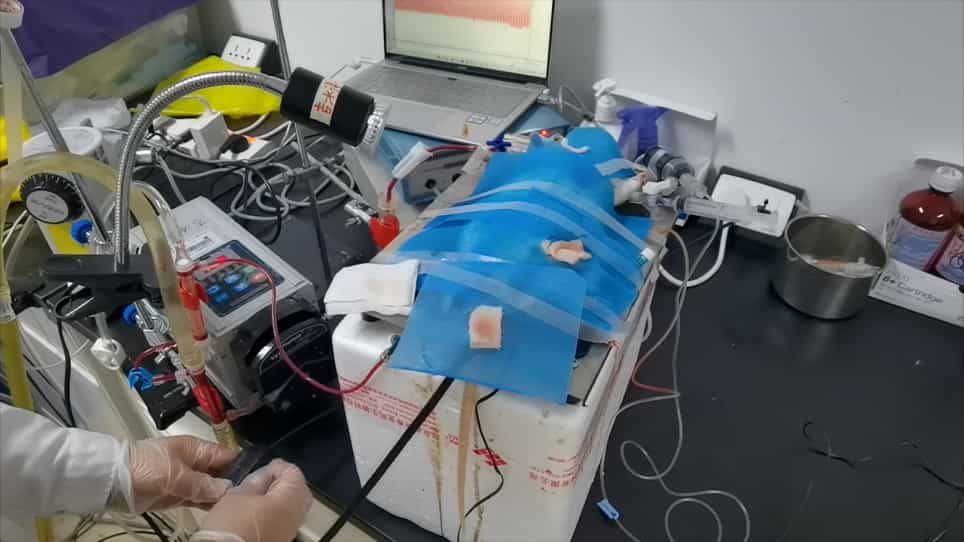
Establishment of Deep Hypothermic Circulatory Arrest in Rats
Published on: December 16, 2022
Anticoagulation management during pulmonary endarterectomy with cardiopulmonary bypass and deep hypothermic
Dennis Veerhoek1, Laurentius Jm van Barneveld1, Renard G Haumann1
1Department of Cardio-Thoracic Surgery, Amsterdam Cardiovascular Sciences, Amsterdam UMC, VU University, Amsterdam, The Netherlands.

Introduction:
Pulmonary endarterectomy requires cardiopulmonary bypass and deep hypothermic circulatory arrest, which may prolong the activated clotting time. We investigated whether activated clotting time-guided anticoagulation under these circumstances suppresses hemostatic activation.
Methods:
Individual heparin sensitivity was determined by the heparin dose-response test, and anticoagulation was monitored by the activated clotting time and heparin concentration. Perioperative hemostasis was evaluated by thromboelastometry, platelet aggregation, and several plasma coagulation markers.
Results:
Eighteen patients were included in this study. During cooling, tube-based activated clotting time increased from 719 (95% confidence interval = 566-872 seconds) to 1,273 (95% confidence interval = 1,136-1,410 seconds; p < 0.01) and the cartridge-based activated clotting time increased from 693 (95% confidence interval = 590-796 seconds) to 883 (95% confidence interval = 806-960 seconds; p < 0.01), while thrombin-antithrombin showed an eightfold increase. The heparin concentration showed a slightly declining trend during cardiopulmonary bypass. After protamine administration (protamine-to-heparin bolus ratio of 0.82 (0.71-0.90)), more than half of the patients showed an intrinsically activated coagulation test and intrinsically activated coagulation test without heparin effect clotting time >240 seconds. Platelet aggregation through activation of the P2Y12 (adenosine diphosphate test) and thrombin receptor (thrombin receptor activating peptide-6 test) decreased (both -33%) and PF4 levels almost doubled (from 48 (95% confidence interval = 42-53 ng/mL) to 77 (95% confidence interval = 71-82 ng/mL); p < 0.01) between weaning from cardiopulmonary bypass and 3 minutes after protamine administration.
Conclusion:
This study shows a wide variation in individual heparin sensitivity in patients undergoing pulmonary endarterectomy with deep hypothermic circulatory arrest. Although activated clotting time-guided anticoagulation management may underestimate the level of anticoagulation and consequently result in a less profound inhibition of hemostatic activation, this study lacked power to detect adverse outcomes.


Related Concept Videos
 01:28
Cardiomyopathy VII: Pre and Post Operative Nursing Management
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:27
Pulmonary Embolism III: Nursing Management
 01:29
Venous Thrombosis III: Interprofessional Care
 01:22
Aneurysm IV: Nursing Management
 01:30
Anticoagulant Drugs: Low-Molecular-Weight Heparins