The potential risk factors of nephrotoxicity during vancomycin therapy in Chinese adult patients
Related Experiment Video
Updated: Dec 18, 2025
Treatment with Vancomycin Loaded Calcium Sulphate and Autogenous Bone in an Improved Rabbit Model of Bone Infection
Published on: March 14, 2019
Yulin Wang1,2, Jian Yang3, Haiyan Zhan1,2
1Department of Pharmacy, Renmin Hospital of Wuhan University, Wuhan, Hubei, China.

Objective:
To evaluate potential risk factors that may make patients susceptible to nephrotoxicity in those concomitantly receiving vancomycin in the hospital.
Methods:
This was a single-centre retrospective analysis of patients treated with vancomycin for gram-positive or mixed infections in the Renmin Hospital of Wuhan University from January 2017 to May 2018. All of them were treated for ≥48 hours and had no kidney disease. Nephrotoxicity refers to acute kidney diseases and disorders after the use of vancomycin, and includes acute kidney injury. Univariate analysis and binary logistic regression analysis with the forward stepwise method were used to assess the risk factors associated with nephrotoxicity.
Results:
Of the 790 patients treated with vancomycin, only 257 patients met the inclusion criteria, and 40 (15.6%) subjects developed nephrotoxicity. Significant differences (p<0.05) were seen in the number of combined antimicrobials (p=0.012), dose adjustment (p<0.001), more than three antimicrobials (p=0.015), monitoring trough concentrations (p=0.001), furosemide (p<0.001), torasemide (p<0.001), cefoperazone sodium tazobactam sodium (p=0.039), voriconazole (p=0.012) and ganciclovir (p=0.008). Regression analysis further indicated that furosemide (OR 7.983, p<0.001) and torasemide (OR 3.496, p<0.001) were risk factors for vancomycin nephrotoxicity. Diabetes mellitus (OR 3.062, p=0.035), voriconazole (OR 3.515, p=0.020) and fluconazole (OR 3.326, p=0.018) might be also risk factors.
Conclusion:
Fluconazole and voriconazole might be potential risk factors for vancomycin nephrotoxicity, besides furosemide and torasemide. It is not recommended to use imipenem cilastatin sodium and vancomycin at the same time. If necessary, meropenem may be safer. Appropriate combination drugs, cautious initial dose or timely dose adjustment might reduce the occurrence of nephrotoxicity when using vancomycin.

Related Concept Videos
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
 01:18
Pharmacokinetics in Geriatric Patients: Effect of Age on Drug Excretion
 01:16
Kidney Transplant III: Nursing Management
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:20
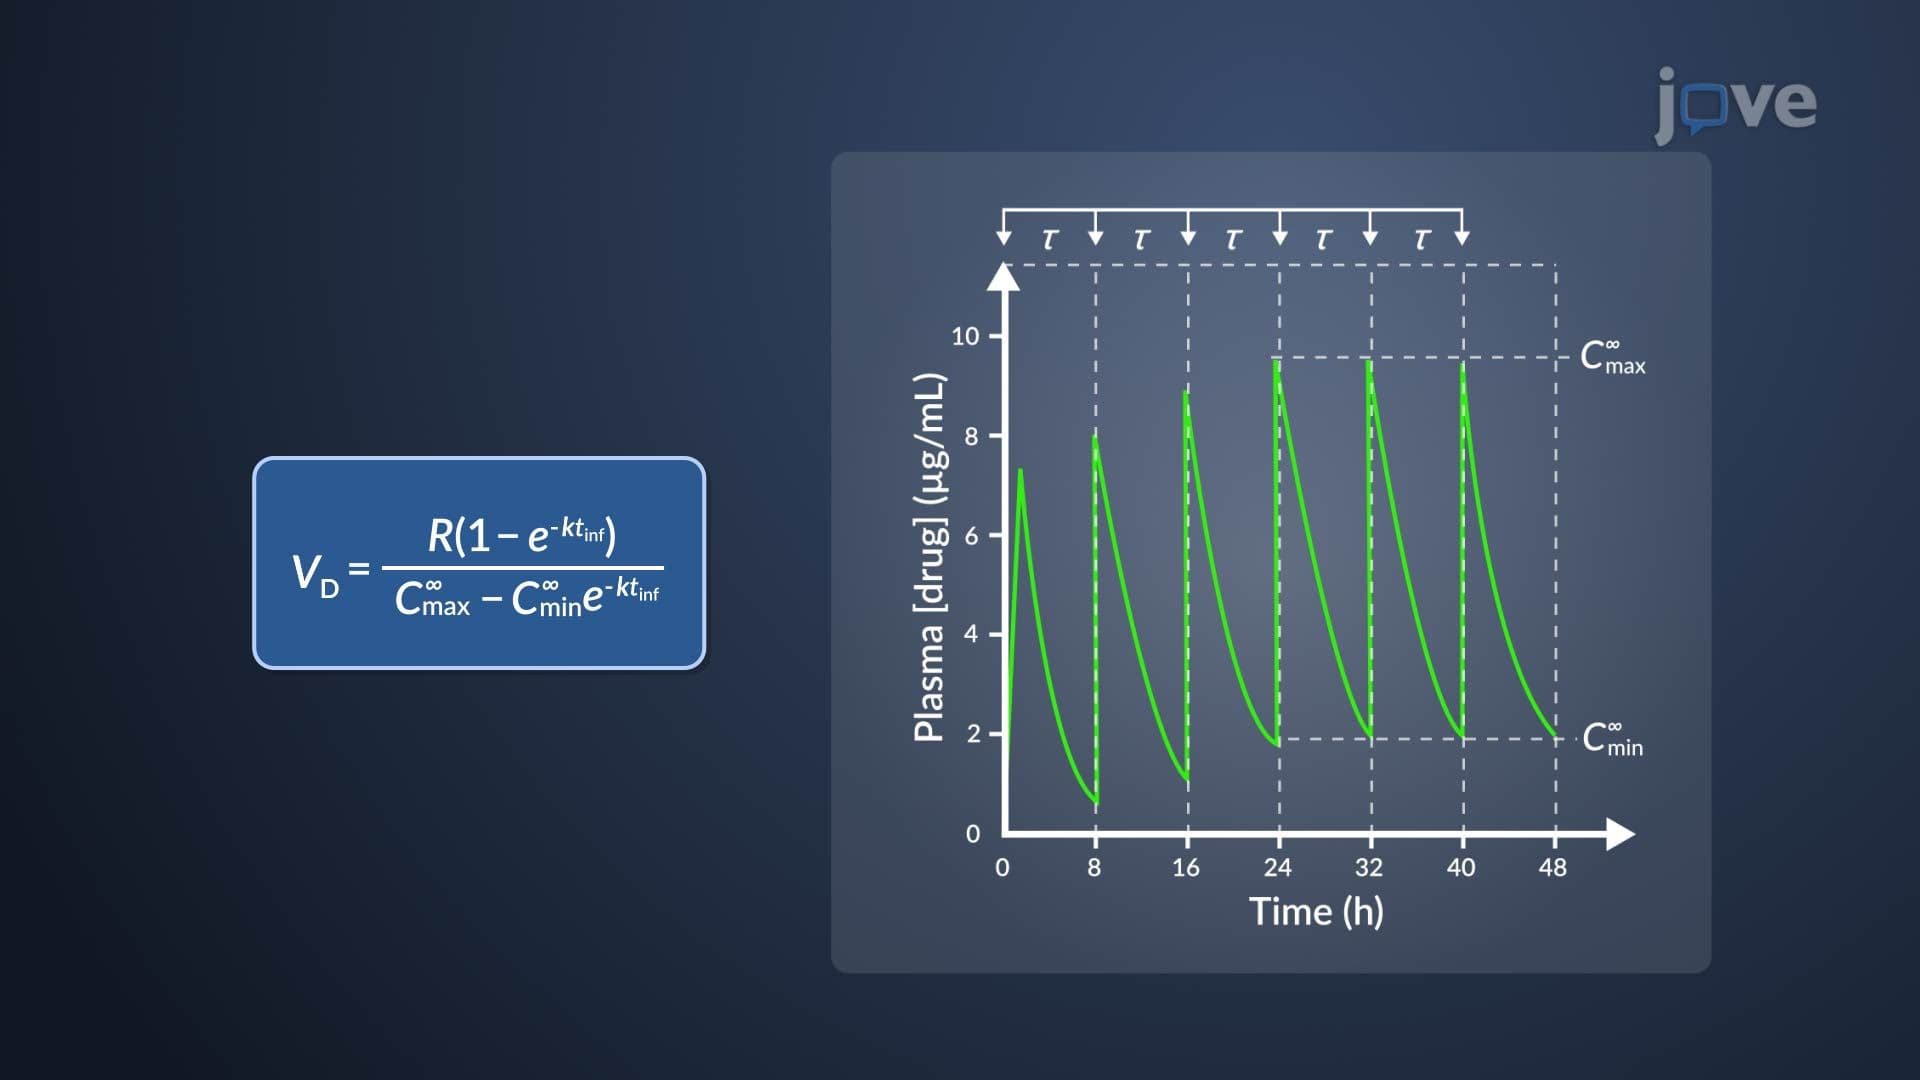
Estimation of k and VD of Aminoglycosides
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...