Related Experiment Video
Updated: Dec 18, 2025
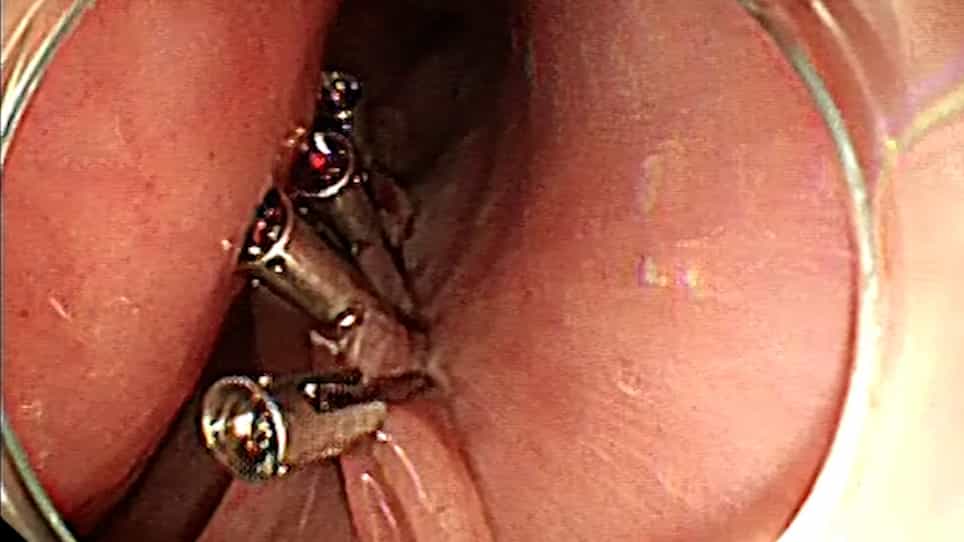
Use of the Scissor-Type Knife During the Peroral Endoscopy Myotomy Procedure for the Treatment of Achalasia
Published on: March 3, 2023
Clinical utility of cricopharyngeal distensibility measurements during endoscopic myotomy for Zenker's diverticulum
Linda Yun Zhang1, Peter Iung-Chiang Wu2, Michal Szczesniak2
1Department of Gastroenterology & Hepatology, St George Hospital, Sydney, New South Wales, Australia.

Background And Aims:
Flexible endoscopic cricopharyngeal myotomy (FECM) allows minimally invasive treatment of patients with Zenker's diverticulum (ZD); however, retreatment rates are substantial. We hypothesized that the functional lumen imaging probe (FLIP) may provide insight into ZD pathophysiology and serve as an intraprocedural guide to adequacy of myotomy.
Methods:
We prospectively evaluated 11 ZD patients undergoing FECM and compared the baseline cricopharyngeal (CP) distensibility with 16 control subjects. Intraprocedural CP distensibility was measured immediately pre- and postmyotomy. The CP distensibility index (CP-DI) was defined as a ratio of the narrowest cross-sectional area (nCSA) and the corresponding intrabag pressure at 40 mL distension. Same-procedure myotomy extension was undertaken in a subgroup if threshold distensibility changes were not met.
Results:
ZD patients had reduced baseline nCSA and CP-DI compared with control subjects, (169.6 vs 227.5 mm2 [P < .001] and 3.8 vs 7.6 mm2/mm Hg [P < .001], respectively). After CP myotomy, both nCSA and CP-DI increased significantly by an average of 74.2 mm2 (95% confidence interval [CI], 35.1-113.3; P = .002) and 2.2 mm2/mm Hg (95% CI, .6-3.8; P = .01), respectively. In the subgroup with no significant change in CP distensibility after initial myotomy (n = 6), myotomy extension resulted in significant increases in both mean nCSA and CP-DI of 66.6 mm2 (95% CI, 16.4-116.8; P = .03) and 1.9 mm2/mm Hg (95% CI, .4-3.3; P = .015), respectively. There were no adverse events.
Conclusions:
CP distensibility is reduced in ZD patients and is partially reversible by FECM. An intraprocedural FLIP CP distensibility measurement is safe and sensitive in detecting myotomy-induced changes. These findings support using FLIP to optimize FECM outcome. Further studies are required to derive precise metrics predictive of clinical response.


Related Concept Videos
 01:26
Endoscopic Procedures V: ERCP
Patient...
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...