Related Experiment Video
Updated: Dec 18, 2025
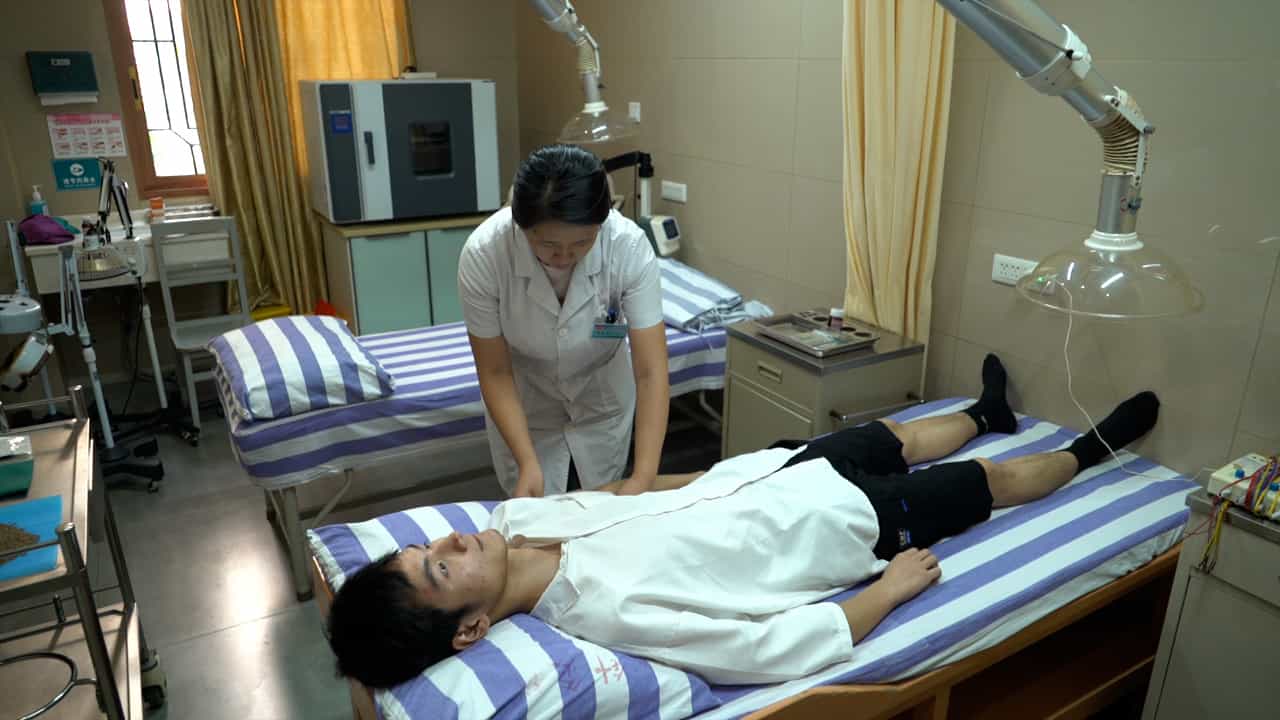

Electroacupuncture Combined with Chinese Medicine Ironing Therapy for Functional Constipation
Published on: July 5, 2024
Manual Physical Therapy in the Treatment of Functional Constipation in Children: A Pilot Randomized Controlled Trial
María Blanco Díaz1, Carlos Bousoño García2, Diana Katherine Segura Ramírez2
1Surgery and Medical Surgical Specialities Department, Faculty of Medicine and Health Sciences, University of Oviedo, Oviedo, Asturias, Spain.

Insights
Manual physical therapy (MPT) showed no significant difference compared to conventional pharmacologic treatment (CPT) for chronic pediatric functional constipation (CPC). However, MPT demonstrated advantages in improving children's quality of life.
Area of Science:
- Pediatric Gastroenterology
- Physical Therapy
- Clinical Trials
Background:
- Chronic pediatric functional constipation (CPC) affects children's quality of life and treatment efficacy.
- Conventional pharmacologic treatment (CPT) is a common approach, but its long-term effectiveness and side effects are concerns.
- Manual physical therapy (MPT) is an emerging therapeutic option for pediatric constipation.
Purpose of the Study:
- To conduct a preliminary assessment of manual physical therapy (MPT) efficacy versus conventional pharmacologic treatment (CPT) in children with chronic pediatric functional constipation (CPC).
- To compare outcomes including symptom severity, quality of life, stool form, and defecation frequency between MPT and CPT groups.
- To evaluate the long-term efficacy of both treatments up to five years post-intervention.
Main Methods:
- A pilot randomized controlled trial involving 47 children (2-14 years) with CPC.
- Participants were randomized to either CPT (control group) or MPT (intervention group).
- MPT involved nine sessions over three months; outcomes were assessed at baseline, 1, 3 months, and 5 years using Symptom Severity Score (SSS), Pediatric Quality of Life Inventory Scale, Bristol Stool Form Scale (BSFS), and defecation frequency (DF).
Main Results:
- No statistically significant differences were found between MPT and CPT for SSS, BSFS, and DF at any follow-up point.
- Both groups showed significant improvements over time in SSS, BSFS, and DF.
- The MPT group demonstrated significantly higher quality of life scores at 3 months and 5 years compared to the CPT group.
Conclusions:
- Preliminary evidence suggests MPT is not significantly different from CPT in improving objective measures of CPC.
- MPT may offer advantages in enhancing the quality of life for children suffering from chronic functional constipation.
- Further large-scale efficacy and noninferiority trials are warranted to confirm these findings and compare MPT directly with CPT.
Abstract:
Make a preliminary assessment of the efficacy of manual physical therapy (MPT) compared to conventional pharmacologic treatment (CPT) in chronic pediatric functional constipation (CPC). A pilot randomized and controlled trial was conducted. Subjects were recruited in a tertiary university hospital in the north of Spain. Forty-seven children (2-14 years) were included. Participants were assessed by Pediatric Gastroenterologist. They were recruited in a tertiary university hospital. Subjects were randomly allocated. MPT was performed in a private clinic. Control group (CG) received CPT and intervention group (IG) received MPT, consisting in nine sessions of MPT with a 45-min initial session and 30 min for the rest of sessions distributed weekly during the first and second months and biweekly in the third month. At times 0-1-3 months and 5 years, results obtained were checked and compared, according to the defecatory pattern ("Symptom Severity Score" SSS), quality of life (Pediatric Quality of Life Inventory Scale), Bristol Stool Form Scale (BSFS), and the defecation frequency (DF). Results from SSS, BSFS, and DF revealed no statistically significant differences between groups in median values at any follow-up. However, there were significant changes over time. The full sample median for SSS was reduced from baseline 24 (interquartile range 20-27) to 11 (6-13) at month 1, 7 (3-13) at month 3, (8 CG; 5 IG), and 5 (1-12) at year 5. The BSFS scale increased from 2 (1-3) at baseline to 4 (3-4) at month 1 and year 5. DF increases progressively from 1 per week to 5 in the fifth year. Higher rates of quality of life were observed at month 3 in IG for the total, physical, and emotional functioning scores and at fifth year for total, emotional, social, and school functioning scores. This study gives preliminary evidence of no difference between MPT and CPT for improvement in measures of CPC, although there was some advantage for MPT in quality of life. Study results justify the conduct of a full-scale efficacy trial of MPT, as well as a noninferiority trial comparing MPT and CPT.
More Related Videos


Related Concept Videos
 01:21
Drugs for Treatment of Constipation-Predominant IBS
 01:17
Drugs for Treatment of Diarrhea-Predominant IBS
Two specific drugs used in the treatment are alosetron (Lotronex) and eluxadoline (Viberzi). Alosetron, a 5-HT3 antagonist, works by slowing the movement of stools in the gut, reducing bowel...
 01:22
Drugs Affecting GI Tract Motility: Bulk-Forming and Stimulant Laxatives
Bulk-forming laxatives, such as psyllium, methylcellulose, and polycarbophil, absorb water in the intestine, increasing stool bulk and promoting bowel movement. This...
 01:30
Irritable Bowel Syndrome III: Medical and Nursing Management
 01:20
Drugs Affecting GI Tract Motility: Other Laxatives
Osmotic or saline laxatives, like magnesium hydroxide or milk of...
 01:30
Irritable Bowel Syndrome II: Clinical Features and Diagnostic Evaluation
Irritable Bowel Syndrome (IBS) is classified into subtypes based on the predominant bowel habits as determined by the Bristol Stool Form Scale (BSFS). The subtypes are: